


Introduction
High-consequence infectious diseases (HCIDs) are easily transmitted between people, have limited or no medical countermeasures, and can cause high morbidity and mortality. Reference Chan, Levine and Herstein1,2 Outbreaks of HCIDs have occurred on a regular basis over the past decade, with a large outbreak of Bundibugyo virus disease currently unfolding in the Democratic Republic of the Congo and Uganda. 3 The Fédération Internationale de Football Association World Cup 2026 in the United States, Mexico and Canada involving large scale international travel heightens the need for healthcare facilities to prepare for outbreaks of endemic and non-endemic infectious diseases. Reference Mehrotra, Mathew and Trulik4
The Joint Commission (TJC) outlines standards for HCID preparedness required at every hospital including prompt identification and isolation of patients with suspected HCIDs and infection control procedures to support continued and safe provision of care. 5 Routine laboratory testing is an important aspect of the initial care for patients with suspected HCID to aid in assessment for other non-HCID conditions, and to assess for electrolyte derangements or anemia that require prompt management. Some HCIDs, particularly viral hemorrhagic fevers (VHFs), generate Category A infectious substances, and therefore require enhanced laboratory safety practices when handling patient specimens. 6
Few published guidelines describe specific solutions to safely perform routine laboratory tests on patients with suspected VHFs. One published toolkit recommends transport of collected specimens to the core laboratory to analyze using point-of-care testing (POCT) machines contained in a biosafety cabinet in the core laboratory. Reference Turbett, Lazarus and Nardini7 It includes solutions for performing a basic metabolic panel and a malaria rapid diagnostic test (RDT). Because of challenges in laboratory biosafety, many frontline acute care hospitals cannot safely perform routine laboratory tests on patients with suspected VHFs. Reference DiLorenzo, Lo Piccolo and Bosk8 Of fifty hospitals that responded to a survey study, only 68% could perform a hemoglobin/hematocrit test, 64% could perform a chemistry panel, and 48% could perform a malaria RDT when assessing an VHF patient. Due to unresolved infection control challenges, one academic medical center group described how it is unfeasible currently to use core laboratory automated instruments for a patient with suspected Ebola disease. Reference Heger, Fritschel and Nussbaum9 These gaps in laboratory capabilities could delay optimal initial management of a febrile returning traveler where malaria is the most common specific etiologic diagnosis. Reference Wilson, Weld and Boggild10
We propose a solution to enable frontline acute care hospitals to safely perform a minimal set of routine laboratory tests for a patient with a suspected VHF. Our solution allows basic testing required to evaluate and care for a patient, and adheres to World Health Organization (WHO) recommendations to use POCT solutions as close as possible to patient care areas. 11 It also aligns with United States (US) national guidelines developed by National Special Pathogens System (NSPS) for minimum laboratory capabilities for frontline (Level 4) facilities 12 without requiring specimen transport to the core laboratory or the use of a biosafety cabinet. We review relevant guidelines and standards and describe elements of laboratory risk assessment, equipment requirements, space, staffing, and management of waste and contaminated equipment. Finally we review costs associated with these solutions. In this paper, we refer to “VHF patients,” but these laboratory testing principles apply to any HCID that generates category A waste and to patients with suspected or confirmed infection with such pathogens.
Review of national and state guidelines and regulations
Laboratory preparedness for HCIDs draws on multiple sources of guidance and regulations that inform clinical care and infection prevention and control, including federal guidance, state regulatory frameworks, and national preparedness programs. The Centers for Disease Control and Prevention (CDC) emphasizes a risk-informed approach that supports continuation of routine diagnostic testing for more likely conditions during evaluation for VHFs when it can be performed safely, with transfer to a facility with appropriate capability when it cannot be done safely. 13
State health departments may define more explicit operational expectations. In New York for example, Department of Health guidance for VHFs outlines expectations for maintaining laboratory testing capability to support clinical management while transfer decisions are made, including the ability to manage patients and sustain necessary laboratory services for at least 24 hours during evaluation. It also requires the use of facility-specific risk assessments to determine the scope and conditions under which laboratory testing may be performed safely. 14 Facilities must also comply with applicable state requirements. For example, New York State regulations require hospitals to provide emergency medical care as indicated by patient condition and to ensure laboratory services meet patient needs (NYCRR §§ 405.7[b][4], 405.16). 15
Beyond state regulations, the NSPS is supported by the US Department of Health and Human Services (HHS) through the Administration for Strategic Preparedness and Response (ASPR) and serves to strengthen the nation’s healthcare readiness for HCIDs. Its guidance is grounded in multidisciplinary expertise and shaped by the direct operational experience of specialized treatment centers and frontline public health response. 12 Importantly, NSPS translates CDC risk-based guidance into a focused and operationally feasible set of expectations tailored to a range of frontline settings, including those with limited laboratory testing capacity. The NSPS categorizes healthcare facilities into four levels (Levels 1–4). Levels 1 and 2 facilities have the highest laboratory capabilities and clinical capacity to provide care for HCID patients for the duration of their illness. Levels 3 and 4 focus on identification, stabilization, limited basic laboratory testing, and transfer to higher level facilities. The NSPS recommends these Level 3 and 4 facilities have plans to safely perform limited POCT diagnostics such as electrolytes, hemoglobin/hematocrit, and malaria testing (RDT or other), with a laboratory risk assessment conducted prior to specimen collection. Some states have started to refer to NSPS guidelines. For example, if Ebola is suspected, the California Department of Health recommends hospitals within their state be able to serve as NSPS Level 4 facilities while coordinating an appropriate transfer with the local health department. 16
Approach to laboratory risk assessment
Clinical laboratory staff may not always be aware they are working with a pathogen that is hazardous to laboratory staff as laboratory specimens are sometimes collected before clinical recognition of a pathogen of concern. Reference Ackelsberg, Liddicoat and Burke17 Laboratory risk assessment is a structured approach to identifying hazards, evaluating risks, and implementing controls to protect staff and work quality. Risk assessment follows a cycle: hazard identification, risk evaluation, prioritization, mitigation, and surveillance. A risk assessment starts with identifying all hazards associated with an infectious agent or material and activities that might lead to exposure to these agents. This is followed by evaluating and prioritizing the risks and severity of the consequences of exposure, and developing, implementing and evaluating controls to minimize the exposure risk.
The first step is to identify activities that might lead to exposures through inhalation, mucous membrane contact, or percutaneous contact. Sample processing activities should be considered, such as whether the specimen tube needs to be opened, whether the specimen must be centrifuged or manipulated in a way that generates aerosols, and whether the specimen can be handled entirely within a biosafety cabinet. The second step is to evaluate, develop, and implement controls to minimize exposure. Engineering controls include biological safety cabinets, sharps containers, centrifuge safety cups, splash guards, pipette aids, puncture and leak resistant transport containers. Building design features can provide directional airflow, improved ventilation, air filtration, and negative pressure to contain the spread of airborne pathogens. The third step is to perform a job safety analysis which outlines the potential hazards and corresponding engineering controls, administrative/work practices, and personal protective equipment (PPE) required to safely perform each task for a given laboratory test. Once the job safety analysis is completed, staff must be trained and undergo competency assessments. Finally, it is vital to audit to ensure effectiveness of the control plan, including reviewing the risk assessment at least annually and whenever faced with a new pathogen or a new diagnostic test. An example Infectious Agent Risk Assessment created by one institution is outlined in Appendix A.
Elements required for operation of NSPS minimum laboratory menu
An example protocol created by one institution is outlined in Appendix B. The following sections describe elements required for protocol implementation.
Diagnostic devices and consumables
POCT in the patient’s isolation room is one available approach to contain potentially infectious waste inside the isolation room and ensure devices used on suspected VHF patients are sequestered until results are available and next steps coordinated with public health authorities. Malaria testing may be performed using the BinaxNOW malaria test, the only Food and Drug Administration-approved malaria RDT available in the US. It is a single-use device with an integrated test strip that assays capillary or EDTA-anticoagulated venous whole blood. Testing must be performed in compliance with applicable Clinical Laboratory Improvement Amendments requirements and state laboratory regulations. Malaria results should be confirmed by microscopy, with specimens submitted to an appropriately certified laboratory for parasitology. In New York State, laboratories performing rapid malaria testing are required to hold a parasitology permit, 18 which may present a logistical barrier to implementation and should be considered during preparedness planning.
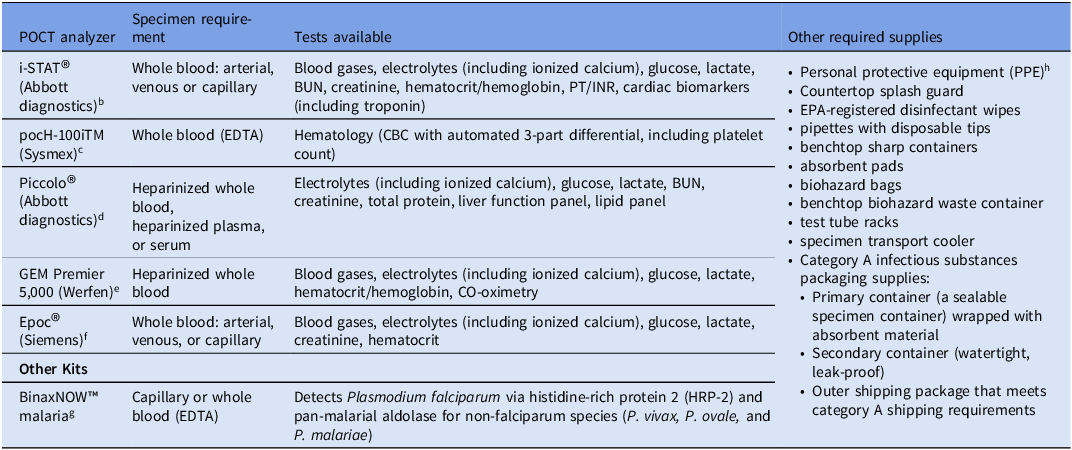
For analysis of electrolytes, hemoglobin and hematocrit within the patient room, a portable, handheld analyzer is needed (Table 1). These devices typically operate using single-use, cartridge-based assays. Planning should also address cartridge storage needs, including refrigeration where applicable, environmental operating conditions (temperature and humidity), and maintenance and quality control requirements, which may be resource-intensive, particularly when devices are used infrequently. Additionally, a preconfigured portable kit should contain essential supplies (Table 1) to minimize room re-entry with contamination risk and to enable efficient workflow.
Options for point-of-care testing (POCT) products a that can enable the minimum routine lab tests for initial management of a suspected high consequence infectious disease (HCID) patient that generates category A waste

Table 1. Long description
A table comparing various point-of-care testing analyzers, their specimen requirements, tests available, and other required supplies. The table has four columns: POCT analyzer, Specimen requirement, Tests available, and Other required supplies. It includes six rows of data for different analyzers and kits. Row 1: i-STAT (Abbott diagnostics), Whole blood: arterial, venous or capillary, Blood gases, electrolytes (including ionized calcium), glucose, lactate, BUN, creatinine, creatinine, hematocrit/hemoglobin, PT/INR, cardiac biomarkers (including troponin), Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements. Row 2: pocH-100iTM (Sysmex), Whole blood (EDTA), Hematology (CBC with automated 3-part differential, including platelet count), Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements. Row 3: Piccolo (Abbott diagnostics), Heparinized whole blood, heparinized plasma, or serum, Electrolytes (including ionized calcium), glucose, lactate, BUN, creatinine, total protein, liver function panel, lipid panel, Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements. Row 4: GEM Premier 5,000 (Werfen), Heparinized whole blood, Blood gases, electrolytes (including ionized calcium), glucose, lactate, hematocrit/hemoglobin, CO-oximetry, Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements. Row 5: Epoc (Siemens), Whole blood: arterial, venous, or capillary, Blood gases, electrolytes (including ionized calcium), glucose, lactate, creatinine, hematocrit, Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements. Row 6: BinaxNOW malaria, Capillary or whole blood (EDTA), Detects Plasmodium falciparum via histidine-rich protein 2 (HRP-2) and pan-malarial aldolase for non-falciparum species (P. vivax, P. ovale, and P. malariae), Personal protective equipment (PPE), Countertop splash guard, EPA-registered disinfectant wipes, pipettes with disposable tips, benchtop sharp containers, absorbent pads, biohazard bags, benchtop biohazard waste container, test tube racks, specimen transport cooler, Category A infectious substances packaging supplies: Primary container (a sealable specimen container) wrapped with absorbent material, Secondary container (watertight, leak-proof), Outer shipping package that meets Category A shipping requirements.
a These instruments and testing kits listed are offered solely as options and are presented exclusively for illustrative purposes. This is not meant to be an exhaustive list and authors are not endorsing any particular product.
b i-STAT G Cartridge, Abbott https://www.globalpointofcare.abbott/content/dam/ardx/globalpointofcare/apoc/support/i-stat-1/cti-ifu/english-us/ifu/788335-00A.pdf.
e Werfen https://www.werfen.com/na/en/point-care-testing-devices/gem-premier-5,000-blood-gas-analyzer.
f Epoc https://www.siemens-healthineers.com/en-us/blood-gas/blood-gas-systems/epoc-blood-analysis-system.
g BinaxNOW™ Malaria https://www.globalpointofcare.abbott/us/en/product-details/binaxnow-malaria.html.
h Specific PPE ensemble required is based on the pathogen of concern.
BUN, blood urea nitrogen; CBC, complete blood count; EDTA, ethylenediaminetetraacetic acid; EPA, Environmental Protection Agency; INR, international normalized ratio; PT, prothrombin time.
Any medical equipment used on a suspected VHF patient must be sequestered and not used on other patients prior to confirming the diagnosis. The medical equipment may remain inside the isolation room if space permits or moved to a designated and secure holding area if space inside the isolation room is limited. Before sequestering, equipment must be cleaned and disinfected following manufacturer’s instructions for use by staff donned in appropriate PPE. If outside the patient room, the method and route to a designated location and securement of the equipment must be considered. For example, during transport, the contaminated equipment should be contained in an impermeable container. The separate room used to sequester equipment should be locked and secured. Additional disinfection, desiccation, and quarantine steps for used medical equipment may be required based on final diagnosis of the VHF. Guidance for these additional steps may be provided by the equipment manufacturer, local public health authorities, or Regional Emerging Special Pathogens Treatment Centers (RESPTC). Based on a local risk assessment, if the diagnosis of a VHF is confirmed, a facility may opt to dispose of the contaminated equipment as category A waste. 19
Spatial considerations for in-room point-of-care testing
The isolation room for a patient with a suspected VHF is designed to support safe clinical care, infection prevention, and efficient workflow by maintaining clear spatial separation between patient care, diagnostic testing, and waste handling zones. A full description of engineering and space recommendations to enable appropriate HCID patient isolation and PPE donning and doffing at acute care facilities has been described separately. Reference Chan, Searl and Khodyakov20,21 The ideal isolation room should have a minimum clear floor area of 140 square feet 22 with a minimum clear dimension of 10 feet and minimum clearance of 4 feet at each side and at the foot of the gurney or bed for clinical care (Figure 1). This enables full clinical access, equipment positioning, and staff movement. Institutions must balance achievement of this ideal spatial arrangement with other considerations for safe care of HCID patients, such as location of the isolation room in proximity to the area where HCID screening occurs and the ability to provide separate and safe areas for PPE donning and doffing.
Recommended isolation room dimensions and setup to facilitate routine laboratory point-of-care testing (POCT) for a patient with suspected viral hemorrhagic fever (VHF) and other high-consequence infectious diseases (HCIDs) that generate category A waste. The room should ideally be an airborne infection isolation room (AIIR) with a private bathroom and at least 4 feet of clearance on each side and at the foot of the bed. The patient care area includes a wall-mounted sharps container and disinfectant wipes within reach. A point-of-care laboratory station with a countertop splash guard is situated away from the bedside with a buffer from the waste area, which is positioned near the room exit along with an alcohol-based hand rub dispenser. This figure was generated by ChatGPT (OpenAI, GPT-5.5), accessed June 2026 (https://chatopenai.com), using prompts derived from the manuscript narrative. All content was reviewed and edited by the authors.

A wall-mounted sharps container should be positioned within immediate reach to enable safe disposal during procedures without requiring additional movement. 23 For a VHF patient, a dedicated POCT area should be positioned within a defined section of the room, separate from both the bedside patient care zone and the waste disposal area to support infection prevention and workflow separation. The testing area includes a stable, non-porous, and cleanable work surface, with sufficient space to accommodate a compact handheld analyzer, essential supplies, and a small, dedicated sharps container to enable immediate disposal during testing activities without requiring movement across zones.
A bedside workspace (eg, over-bed table or Mayo stand) supports clinical activities while allowing bedside tasks to be completed without entering the POCT area, preserving separation between higher- and lower-risk activities. All work surfaces should be nonporous. Environmental disinfection should be supported throughout the room, with ready access to disinfectant supplies in both patient care and POCT areas. 24
A waste management zone is strategically located adjacent to the exit door. This placement minimizes the movement of contaminated materials across the care environment and aligns with recommended unidirectional workflow principles.
Staffing considerations
Hospitals require a staffing model that supports capability for moderately complex POCT for a VHF patient at any time of day. The staff who will perform the POCT must train and maintain competency under the supervision of a laboratory point of care supervisor.
One approach is to train all staff who might encounter a patient with a suspected VHF for the necessary POCT. This approach guarantees that on-duty staff can promptly perform the POCTs at any given time. However, all staff would require periodic refresher training, requiring significant oversight and training resources.
Another approach is to train a specialized group of staff to perform POCT. At least some members of this specialized group will need to be available at all times. Staff who encounter a VHF patient would request the POCT-trained staff member on call to perform POCT. This approach requires fewer training resources to maintain competency of a smaller number of staff. One drawback is greater delay in completing the POCT if none of the on-call trained staff are on site when a suspected VHF patient is identified.
A third approach is to plan just-in-time training at the time the hospital encounters a suspected VHF. This approach minimizes the cost of training because training is provided only in the limited circumstance of evaluating a suspected case. However, just-in-time training requires an on-call schedule for a trainer and could result in lower quality of training due to time constraints, potentially higher exposure risk and less reliable test results due to lack of practice, and delays to completion of the testing.
Each staffing model has strengths and drawbacks, with the ultimate approach determined by individual hospitals and available resources.
Safe handling and storage of waste
The safe handling, storage, treatment, transportation, and disposal of waste suspected or confirmed to be contaminated with a category A pathogen such as Ebola virus, must begin at the point of generation and continue through final disposal. 19 Waste may be generated during a variety of activities, including:
-
• Use of medical supplies and equipment during patient care
-
• Collection, processing, and testing of clinical laboratory specimens
-
• Cleaning and disinfection of patient rooms, treatment areas, and equipment
-
• Removal and disposal of used PPE
-
• Spill response and cleanup
Pending definitive diagnosis, waste and contaminated equipment must be sequestered and securely stored within the patient’s room or transported to a designated preapproved area until appropriate classification and disposal pathways are established. Waste volume and capacity should be planned by accounting for estimated daily waste and identifying the room’s maximum storage capacity. Waste storage areas must meet all applicable fire codes and maintain a clutter-free, safe environment. Personnel responsible for handling, packaging, and transporting waste must be trained and demonstrate competency in appropriate procedures, including safe bag closure techniques. The handling and disposition of category A waste must be in accordance with applicable federal, state, and local regulations.
Cost estimates for this solution
Estimating and planning for the financial cost is another key aspect of preparing for safely performing routine laboratory tests on confirmed or suspected VHF patients. One cost is from purchasing POCT machines that can perform the minimum required laboratory tests. If a facility already uses POCT machines in other contexts, it would likely be easiest to utilize the same machine for VHF laboratory testing. Even in this situation, it may be prudent to purchase at least one additional set of machines since one set will need to be dedicated to the VHF patient, and the device may need to be quarantined after the patient is discharged or transferred. Direct financial cost estimates need to account for purchasing reagents, including extra reagents needed for training and quality control. Exact costs will depend on laboratory contracts. One New York City facility in 2023 estimated the price of the POCT machine $6,000–15,000 and between $5–2,000 per test cartridge. Some device manufacturers also charge for annual service, which can be an additional $500–1,000. Rapid malaria RDT test cards can cost $50 per test.
There are also indirect financial costs including time to train the frontline providers on the POCT protocols, performing proficiency testing, and running quality control. Initial training usually takes at least 1 hour, with 20-minute competency assessments done every 6 months. The information technology team will also need to connect data from these POCT machines to the electronic health record. Finally, the machine and reagents will need space for storage, which has indirect costs.
Conclusions
Outbreaks of HCIDs have been more frequently detected and reported since the late 1990s. Reference Chan, Levine and Herstein1 Optimal preparedness includes the ability to perform a minimum set of routine laboratory tests that can guide management of electrolyte disturbances and diagnose malaria. Suspected and confirmed cases of VHFs require the same infection prevention and control precautions. We describe a solution for frontline acute care hospitals to be able to perform point-of-care electrolytes, hemoglobin/hematocrit, and malaria RDT, guided by a laboratory risk assessment in the patient isolation room. Our solution locates the testing in the patient isolation room which obviates the need for a biosafety cabinet. Key recommendations are summarized in Figure 2.
Recommendations for frontline acute care hospitals to safely perform routine laboratory testing for patients with suspected viral hemorrhagic fevers (VHFs).

Our solution has limitations. Firstly, any solution requires a financial investment to ensure appropriate equipment, space, and trained staff are available. While there was recent funding available through National Emerging Special Pathogens Training & Education Center to support seventy-five new Level 2 facilities across the US, with additional funding rounds anticipated, 25 there has been no dedicated funding available to support capabilities at Level 3 and 4 facilities, which comprise most healthcare facilities. In addition, the solution described in this manuscript only makes a limited laboratory menu available, which may not be sufficient for a critically ill patient. However, the aim is to provide initial stabilizing care pending transfer to a Level 1 or 2 facility. Finally, space limitations may be difficult to modify. The standards we describe adhere to Facility Guidelines Institute standards and allow for ideal patient care and POCT to be done in the same room. However, our review of several local emergency departments found that not all facilities can provide a designated isolation room for VHF patients that meets these spatial standards.
While acknowledging these limitations, we have described a pragmatic solution for frontline acute care hospitals to safely provide a minimum set of routine laboratory tests for a patient with a suspected or confirmed VHF, in accordance with NSPS national guidelines. Further work should be done to develop alternative approaches including models of mobile laboratory testing services that may support smaller hospitals unable to implement in-house solutions.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/ash.2026.10817.
Acknowledgments
The authors thank Jon Agramonte, Neldis Sanchez, and Casandra Spallino for their contributions to developing the Example VHF Laboratory Point-of-Care Testing (POCT) Protocol.
Author contribution
JC led conceptualization, project administration, and supervision. JC, FD, MD, PD, JF, MH, JLJ, DM, JP, ALS, and GW contributed to literature review and synthesis. ALS, JF, and JP developed the visualizations. JC, ALS, JLJ, DM, and GW drafted the original manuscript. All authors contributed to reviewing and editing subsequent versions of the manuscript.
Financial support
MD and JC are members of their region’s Regional Emerging Special Pathogen Treatment Center (RESPTC) and receive funding from Health and Human Services’ (HHS) Administration for Strategic Preparedness and Response (ASPR).
Competing interests
The authors have no conflicts of interest to disclose.


 Open access

