


Mental health outcomes differ significantly across different patient populations. Numerous studies have reported disparities influenced by socioeconomic status, ethnicity, gender and age, among other things. 1–Reference Marmot, Smith, Stansfeld, Patel, North and Head3
Although there has been growing interest in patient-reported outcome measures (PROMs) and patient-reported experience measures (PREMs), there is a dearth of published research in these fields. Reference Reininghaus and Priebe4 This is in part due to the challenges around effective implementation of PROMs and PREMs data collection. Reference Bull, Teede, Watson and Callander5–Reference Bull and Callander7 Research using PROMs has often looked into specific populations or utilised specific symptom-based PROMs, such as for women with breast cancer Reference Champion, Krebsbach, Stallion and Dookeran8 or early inflammatory arthritis. Reference Yates, Bechman, Adas, Wright, Russell and Nagra9 Although some studies have used quality-of-life measures in the community looking at health inequity, these were cross-sectional and could not measure change. Reference Schelleman-Offermans and Massar10 Moreover, not all PROMs have shown sensitivity to change. Reference Blenkiron and Goldsmith11
Published health inequity research has traditionally emphasised access, experience and adverse outcomes. 12–Reference Jonassaint, Belnap, Huang, Karp, Abebe and Rollman16 We found limited research that examined inequities using PROMs and PREMs data in those receiving specialist mental healthcare for serious mental illness (SMI). Our study aims to add to health inequity research by focusing on differences in quality of life and treatment experience through the treatment journey in adults accessing specialist mental healthcare.
We conducted a quantitative evaluation of routinely collected DIALOG data within mental health services in either a medium-sized mental health provider or National Health Service (NHS) trust. We aimed to analyse whether there is a differential impact on patient outcome and experience measures captured between different demographic groups. Further information on our rationale, and on our findings related to overall treatment journey and community mental health (CMH) transformation, has been reported in a previous paper. Reference Spicer, Bhattacharya, Smalley, Shetty, Sharpe and Byng17
Method
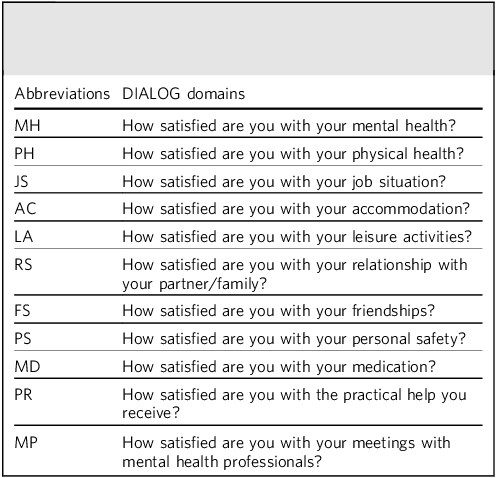
DIALOG is an 11-item scale used for measuring subjective quality of life and treatment satisfaction (Table 1), encompassing both PROMs (first 8 items) and PREMs (final 3 items) components. Reference Priebe, Golden, McCabe and Reininghaus18,Reference Mosler, Priebe and Bird19
DIALOG scale. The following items are scored on a Likert scale of 1–7 (1 is totally dissatisfied and 7 is totally satisfied)

Table 1 Long description
A table with two columns and eleven rows. The first column is labeled Abbreviations and the second column is labeled DIALOG domains. The table lists abbreviations and their corresponding questions about satisfaction in various aspects of life. Row 1: MH, How satisfied are you with your mental health? Row 2: PH, How satisfied are you with your physical health? Row 3: JS, How satisfied are you with your job situation? Row 4: AC, How satisfied are you with your accommodation? Row 5: LA, How satisfied are you with your leisure activities? Row 6: RS, How satisfied are you with your relationship with your partner/family? Row 7: FS, How satisfied are you with your friendships? Row 8: PS, How satisfied are you with your personal safety? Row 9: MD, How satisfied are you with your medication? Row 10: PR, How satisfied are you with the practical help you receive? Row 11: MP, How satisfied are you with your meetings with mental health professionals?
East London NHS Foundation Trust (ELFT) is an organisation that offers specialist mental healthcare as part of the UK NHS. ELFT was an early adopter of DIALOG and started to implement its routine use in 2017. Reference Mosler, Priebe and Bird19 In 2023, NHS England identified DIALOG as one of the three recommended outcome measures for CMH. 20
In England, a broad national strategy, published in 2019, was called the NHS Long Term Plan. 21,22 Related to this was a national initiative by NHS England called the Community Mental Health Framework for Adults and Older Adults, or CMH Framework. 23 As part of this initiative there was a focus on integrating specialist secondary care community mental health teams (CMHTs) and their corresponding primary care networks (PCNs). The purpose of this was to ensure that care and support are available for those who do not meet existing thresholds for secondary care, and following discharge from a CMHT. This led to reconfiguration of CMHTs, promoting closer partnerships with PCNs or general practitioners aimed at a more integrated mental healthcare service, bridging any previous gaps between primary and secondary care. In ELFT, this led to integration of the primary care liaison (mental health) teams with CMHTs to create the neighbourhood mental health team.
ELFT commissioned the University of Plymouth to evaluate the impact of the CMH transformation, a national strategy aiming at service reconfiguration. Reference Spicer, Bhattacharya, Smalley, Shetty, Sharpe and Byng17 As part of the service evaluation, routinely collected DIALOG scores from CMH teams or services were anonymised, pooled and subsequently analysed. The two time periods were chosen as pre- and post-transformation, implemented in autumn 2019. ELFT’s business analysis team searched electronic patient records (RiO) for DIALOG scores recorded for patients in scope. DIALOG scores from CMHTs and primary care liaison teams for 2018–2019 and the ‘transformed’ community or neighbourhood mental health team in 2021–2022 were in scope. These teams provided the core CMH treatment offer for working-age adults (18+ years). The data were collected from three London boroughs serviced by ELFT: City and Hackney, Tower Hamlets and Newham. The effect of treatment stage and the comparison of these pre- and post-transformation are reported in a separate, linked paper. Reference Spicer, Bhattacharya, Smalley, Shetty, Sharpe and Byng17 This second paper assesses the effect of treatment stage (patient journey) and the comparison between these pre- and post-service transformations.
We identified 11 198 DIALOG assessments from 5007 unique patients over the 2 periods. In this paper we interrogate and analyse the data-set through an equity lens. We disaggregated data linked to the personal characteristics of age, gender, ethnicity and deprivation. Where data on age, gender and ethnicity were directly available, we used the index of multiple deprivation (IMD) scores generated from linked postcodes as a proxy for deprivation. IMD scores are available through government data. 24 Similar to our previous paper, when comparing stages of treatment, we defined these as ‘assessment’ for new referrals, ‘review’ for ongoing treatment and ‘discharge’ for end of treatment.
The DIALOG scale for each domain has a ratings scale of 1 to 7; however, because each of the quality-of-life domains is an independent construct, all domains or questions are analysed separately. Statistical differences between means were compared for descriptive comparison for each domain. On the scale of 1–7, scores of 1–3 represent varying degree of dissatisfaction. To carry out regression analysis controlling for other variables, we therefore also converted the score to a binomial of ‘satisfied’ (4–7) versus ‘dissatisfied’ (1–3). Both these approaches to analysis of DIALOG scores are recognised in the analytic framework of DIALOG for pooled scores. Reference Bhattacharya, Priebe and Bird25
The following analyses were conducted using R 2024 version for Windows and Ubunti (R Core Team, R Foundation, Vienna, Austria; https://www.r-project.org/).
-
(a) We compared differences between mean scores for each group; we used descriptive statistics to compare statistical significance between mean scores in comparisons between subgroups.
-
(b) For each DIALOG domain we estimated a multivariable logistic regression, with odds of reporting ‘satisfied’ in the DIALOG domain in one subgroup compared with another controlling for all other variables.
Results
Because age and deprivation are numerical rather than categorical variables, we carried out regression analysis without any corresponding bar plots. In regard to DIALOG scores, because a given time point of data gathering is dependent on the patient’s choice in responding to the DIALOG question domain, not all 11 DIALOG domains were always filled in; therefore, there is variation in the number of scores available for analysis for each domain of DIALOG. Values for the different domains for subcategories are available as Supplementary material 2.
Deprivation
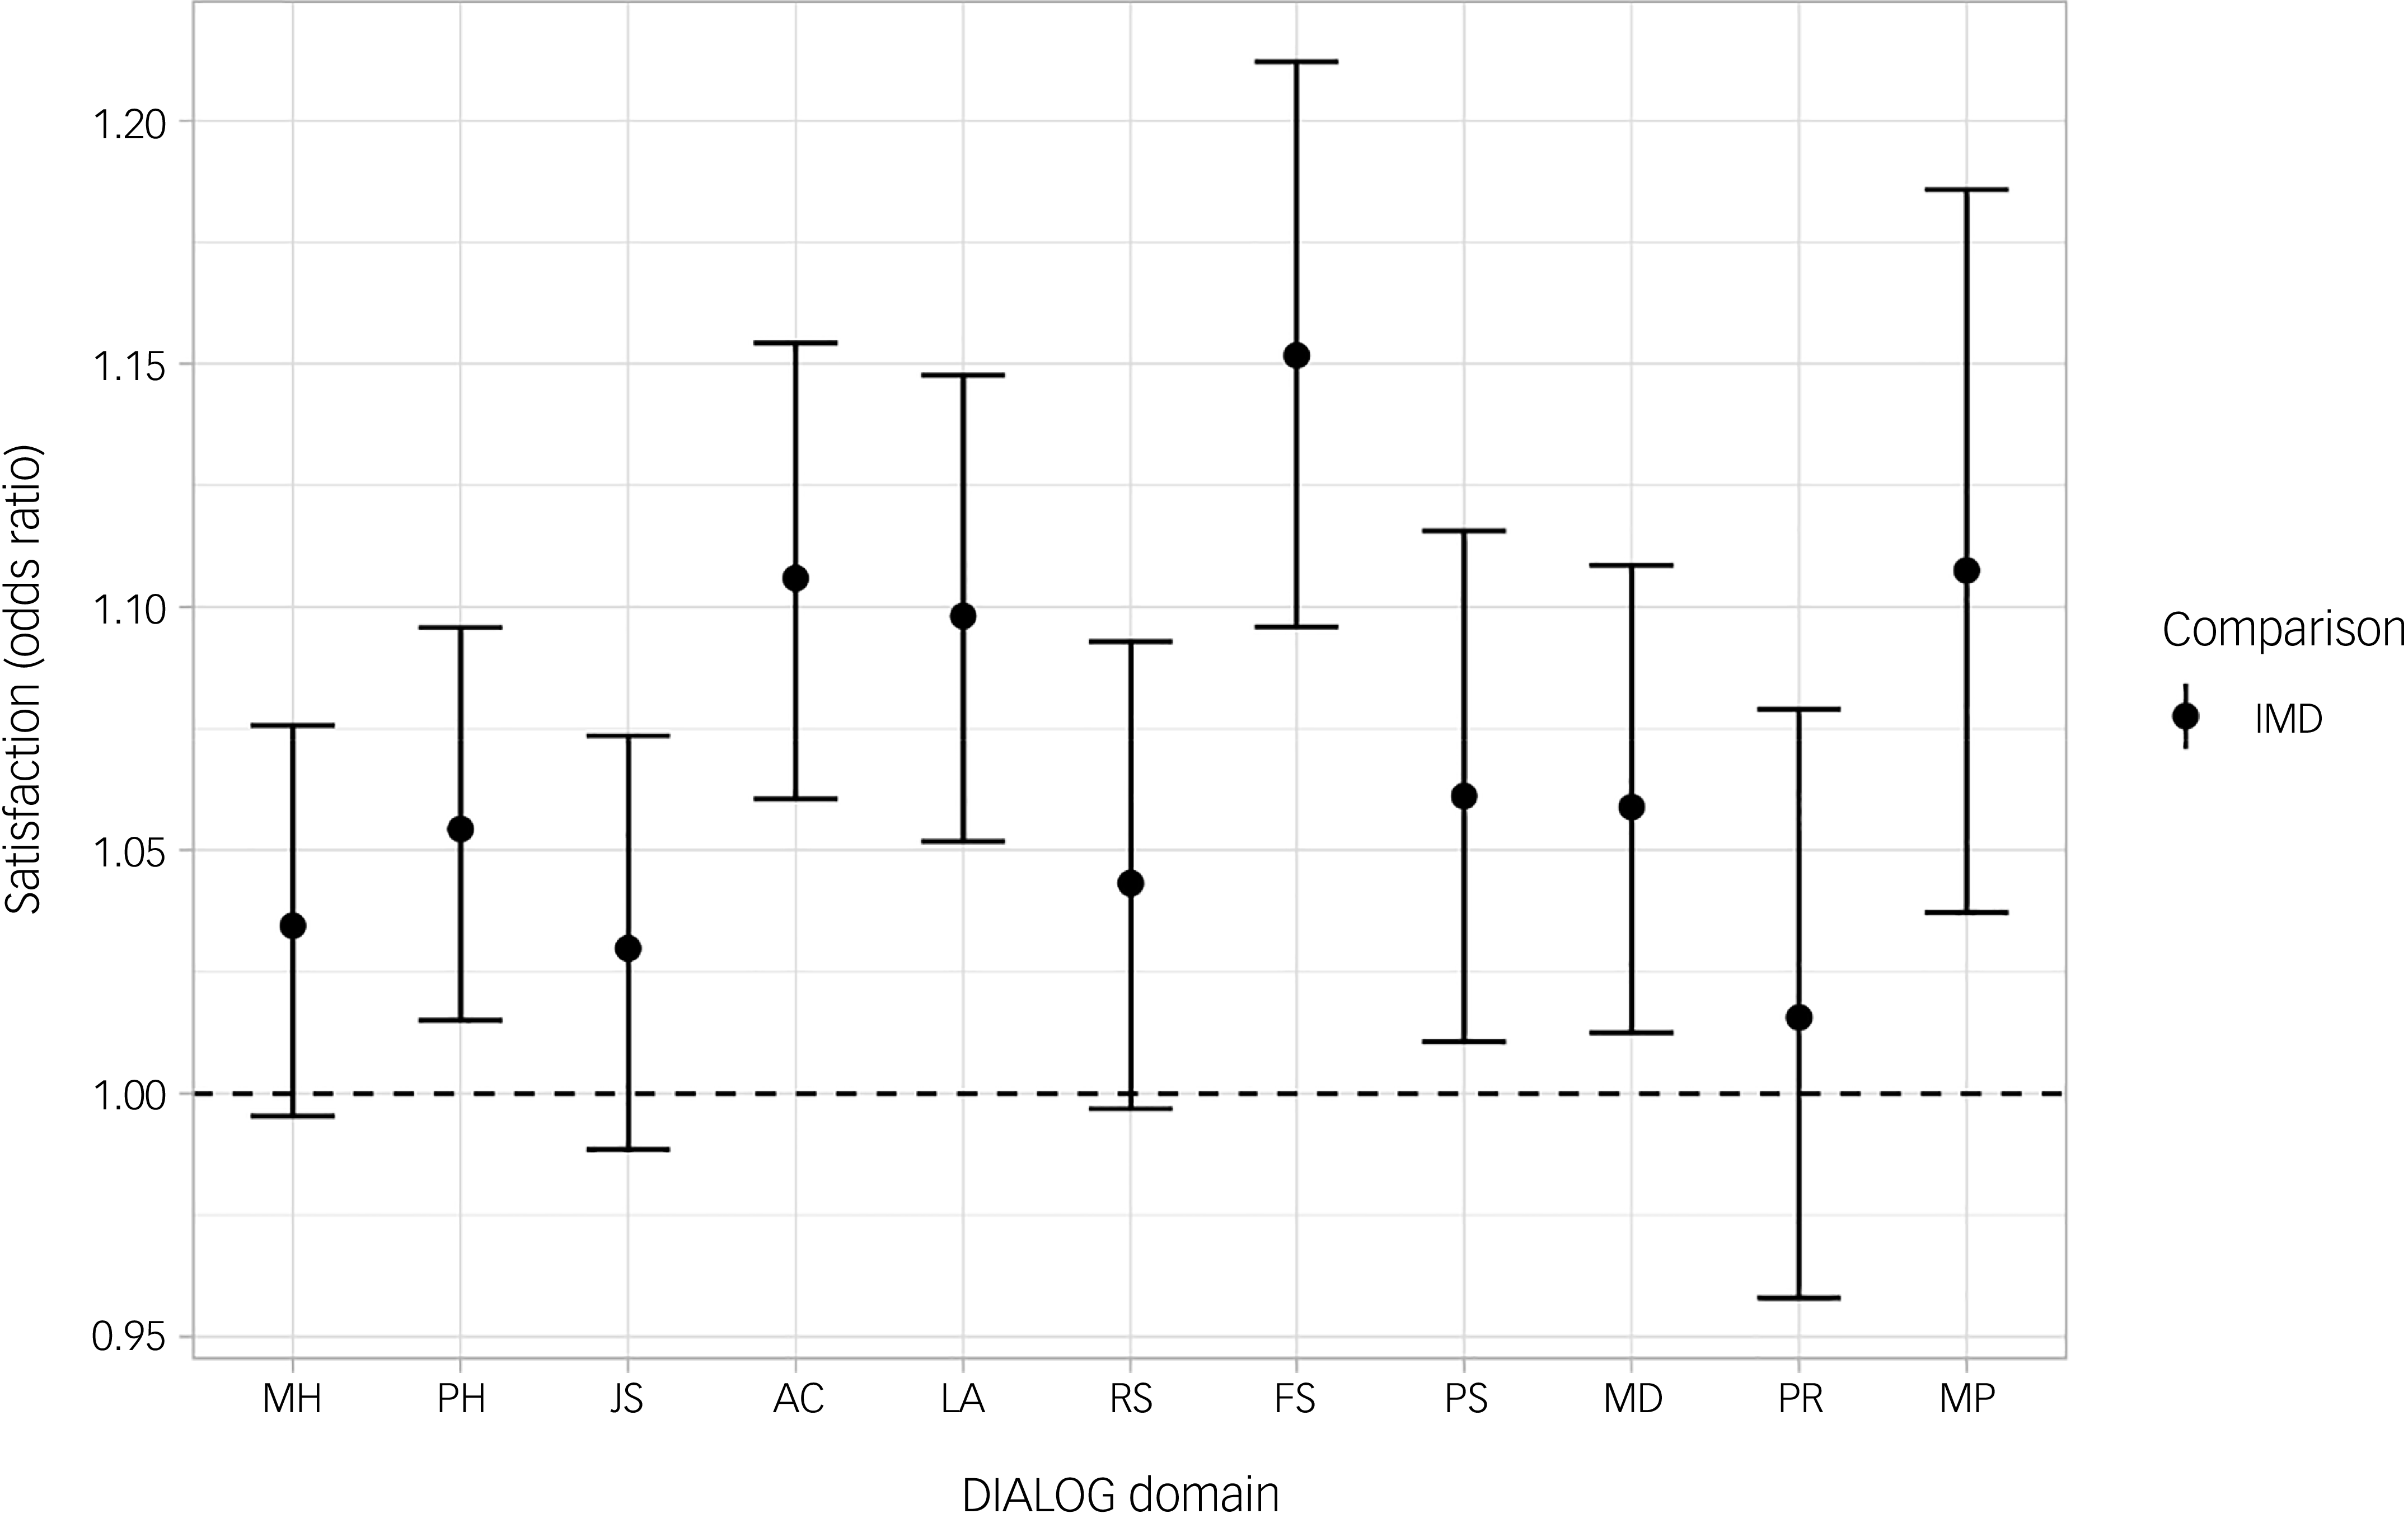
We report the regression analyses of the effect of deprivation on satisfaction scores in DIALOG, which was studied using IMD, with higher scores indicating less deprivation.
We found that patients from more socioeconomically deprived areas had lower satisfaction in regard to physical health, accommodation, leisure activities, friendships and personal safety, as well as in regard to experiences with medication and interactions with mental health professionals (Fig. 1).
Results of multiple regressions evaluating the influence of the index of multiple deprivation (IMD) on DIALOG scores. Higher values indicate higher odds of satisfaction in each DIALOG domain. Whiskers denote 95% confidence intervals; when the whiskers are >1, this variable is significantly associated with greater odds of being satisfied; and when <1, it is associated with lower odds of being satisfied. Intermediate values are not significant. This also applies to subsequent multiple-regression analysis plots in this paper. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Ethnicity
We studied the differences in satisfaction based on ethnicity, comparing Black and Asian patients with White British.
First, we report descriptive analyses of the differences in satisfaction reported by Black patients when compared with White patients at the assessment stages of 2018–2019 and 2021–2022 (Fig. 2).
Mean DIALOG scores for each domain of patients at assessment stage, split by ethnicity (Black versus White) separately for the periods 2018–2019 and 2021–2022. Error bars are 95% confidence intervals; bars with non-overlapping confidence intervals can be interpreted as significantly different. There were N = 4193 sets of DIALOG assessment scores. Please refer to Table 1 for abbreviations denoting DIALOG domains.

We found that patients of Black ethnicity had statistically higher levels of satisfaction with their mental and physical health in both years. In 2021–22, these patients also reported higher satisfaction in regard to leisure, friendships, experience of medication (PREMs) and professional meetings (PREMs). Black patients were less satisfied with their job situation in 2018–2019 when compared with White patients.
The category of discharge included very few submitted scores for Black patients (29 in 2018 and 28 in 2021) and there were no significant statistical differences, potentially due to large confidence intervals (see Supplementary material 1 for discharge plots).
Regression analysis comparing patients of Black and White ethnicity revealed that the former had higher odds of satisfaction for mental and physical health, leisure activities, relationships, friendships and medication compared with the latter (Fig. 3). This analysis is independent of stage of treatment.
Results of multiple regressions evaluating the influence of ethnicity (Black versus White) on DIALOG scores. Higher values indicate higher odds of satisfaction in each DIALOG domain. Whiskers are 95% confidence intervals; when whiskers are >1, this variable is significantly associated with greater odds of being satisfied; and if <1, it is associated with lower odds of being satisfied. Intermediate values are not significant. All predictor variables are labelled to show what they are being compared against: e.g. ‘Ethnicity: Black versus White’ means that Black ethnicity is the predictor variable and White ethnicity is what it is being compared against. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Second, we report on the comparison of Asian and White British patients. Descriptive analysis found that, at assessment stage, the former reported statistically higher satisfaction for mental health and accommodation in 2021–2022. Additionally, White patients had lower satisfaction with their experience with mental health professionals and medication in 2021–2022 compared with 2018–2019 (Fig. 4).
Mean DIALOG scores for each domain of patients at the assessment stage, split by ethnicity (Black versus White) separately in 2018–2019 and 2021–2022. Error bars are 95% confidence intervals; bars with non-overlapping confidence intervals can be interpreted as significantly different. There were N = 4193 sets of DIALOG assessment scores. Please refer to Table 1 for abbreviations denoting DIALOG domains.

At discharge, Asian patients were less satisfied with their physical health in 2021–2022 compared with 2018–2019 (see Supplementary material 1). However, because the total number of DIALOG scores collected at discharge for Asian patients was very low (30 in 2018 and 14 in 2021), we suggest that the results are interpreted with caution.
Next, we report the regression analysis results comparing Asian with White patients; we found that the former had higher odds of satisfaction for mental and physical health, leisure, friendships and experience of medication (PREMs) (Fig. 5).
Results of multiple regressions evaluating the influence of ethnicity (Asian versus White) on DIALOG scores. Higher values indicate higher odds of satisfaction in each DIALOG domain. Whiskers are 95% confidence intervals; when whiskers are >1, this variable is significantly associated with greater odds of being satisfied; and if <1, it is associated with lower odds of being satisfied. Intermediate values are not significant. All predictor variables are all labelled to show what they are being compared against: e.g. ‘Ethnicity: Asian versus White’ means that Asian ethnicity is the predictor variable and White ethnicity is what we are comparing it against. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Gender
Descriptive analysis of DIALOG scores at the assessment stage are reported in Fig. 6. Men reported lower mental and physical health satisfaction in 2021–2022 versus 2018–2019 (reduction over time), with women showing no changes that were statistically significant over the same period.
Mean DIALOG scores for each domain of patients at the assessment stage, split by gender (male and female) separately in 2018–2019 and 2021–2022. Error bars are 95% confidence intervals; bars with non-overlapping confidence intervals can be interpreted as significantly different. There were N = 4193 sets of DIALOG assessment scores. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Fig. 6 Long description
Panel A: A bar graph comparing mean DIALOG scores across different domains for male and female patients in 2018-2019 and 2021-2022. The horizontal axis represents the DIALOG domains: MH, PH, JS, AC, LA, RS, FS, PS, MD, PR, and MP. The vertical axis represents the mean DIALOG score ranging from 3 to 6. The graph includes four sets of bars for each domain, representing Female 2018-2019, Male 2018-2019, Female 2021-2022, and Male 2021-2022. Each set of bars is color-coded: purple for Female 2018-2019, green for Male 2018-2019, blue for Female 2021-2022, and pink for Male 2021-2022. Error bars indicate 95% confidence intervals. Notable trends include higher scores in the PR and MP domains across all groups and lower scores in the MH and PH domains. Specific mean scores for each domain and group are visible on the bars.
In 2021–2022, women reported increased satisfaction with their job situation compared with men. In other domains, no significant differences were noted.
At discharge, men had lower levels of satisfaction in 2021–2022 when compared with 2018–2019, which reached statistical significance for the PREMs domains of medication and (contact with) mental health professionals (figure included in Supplementary material 1).
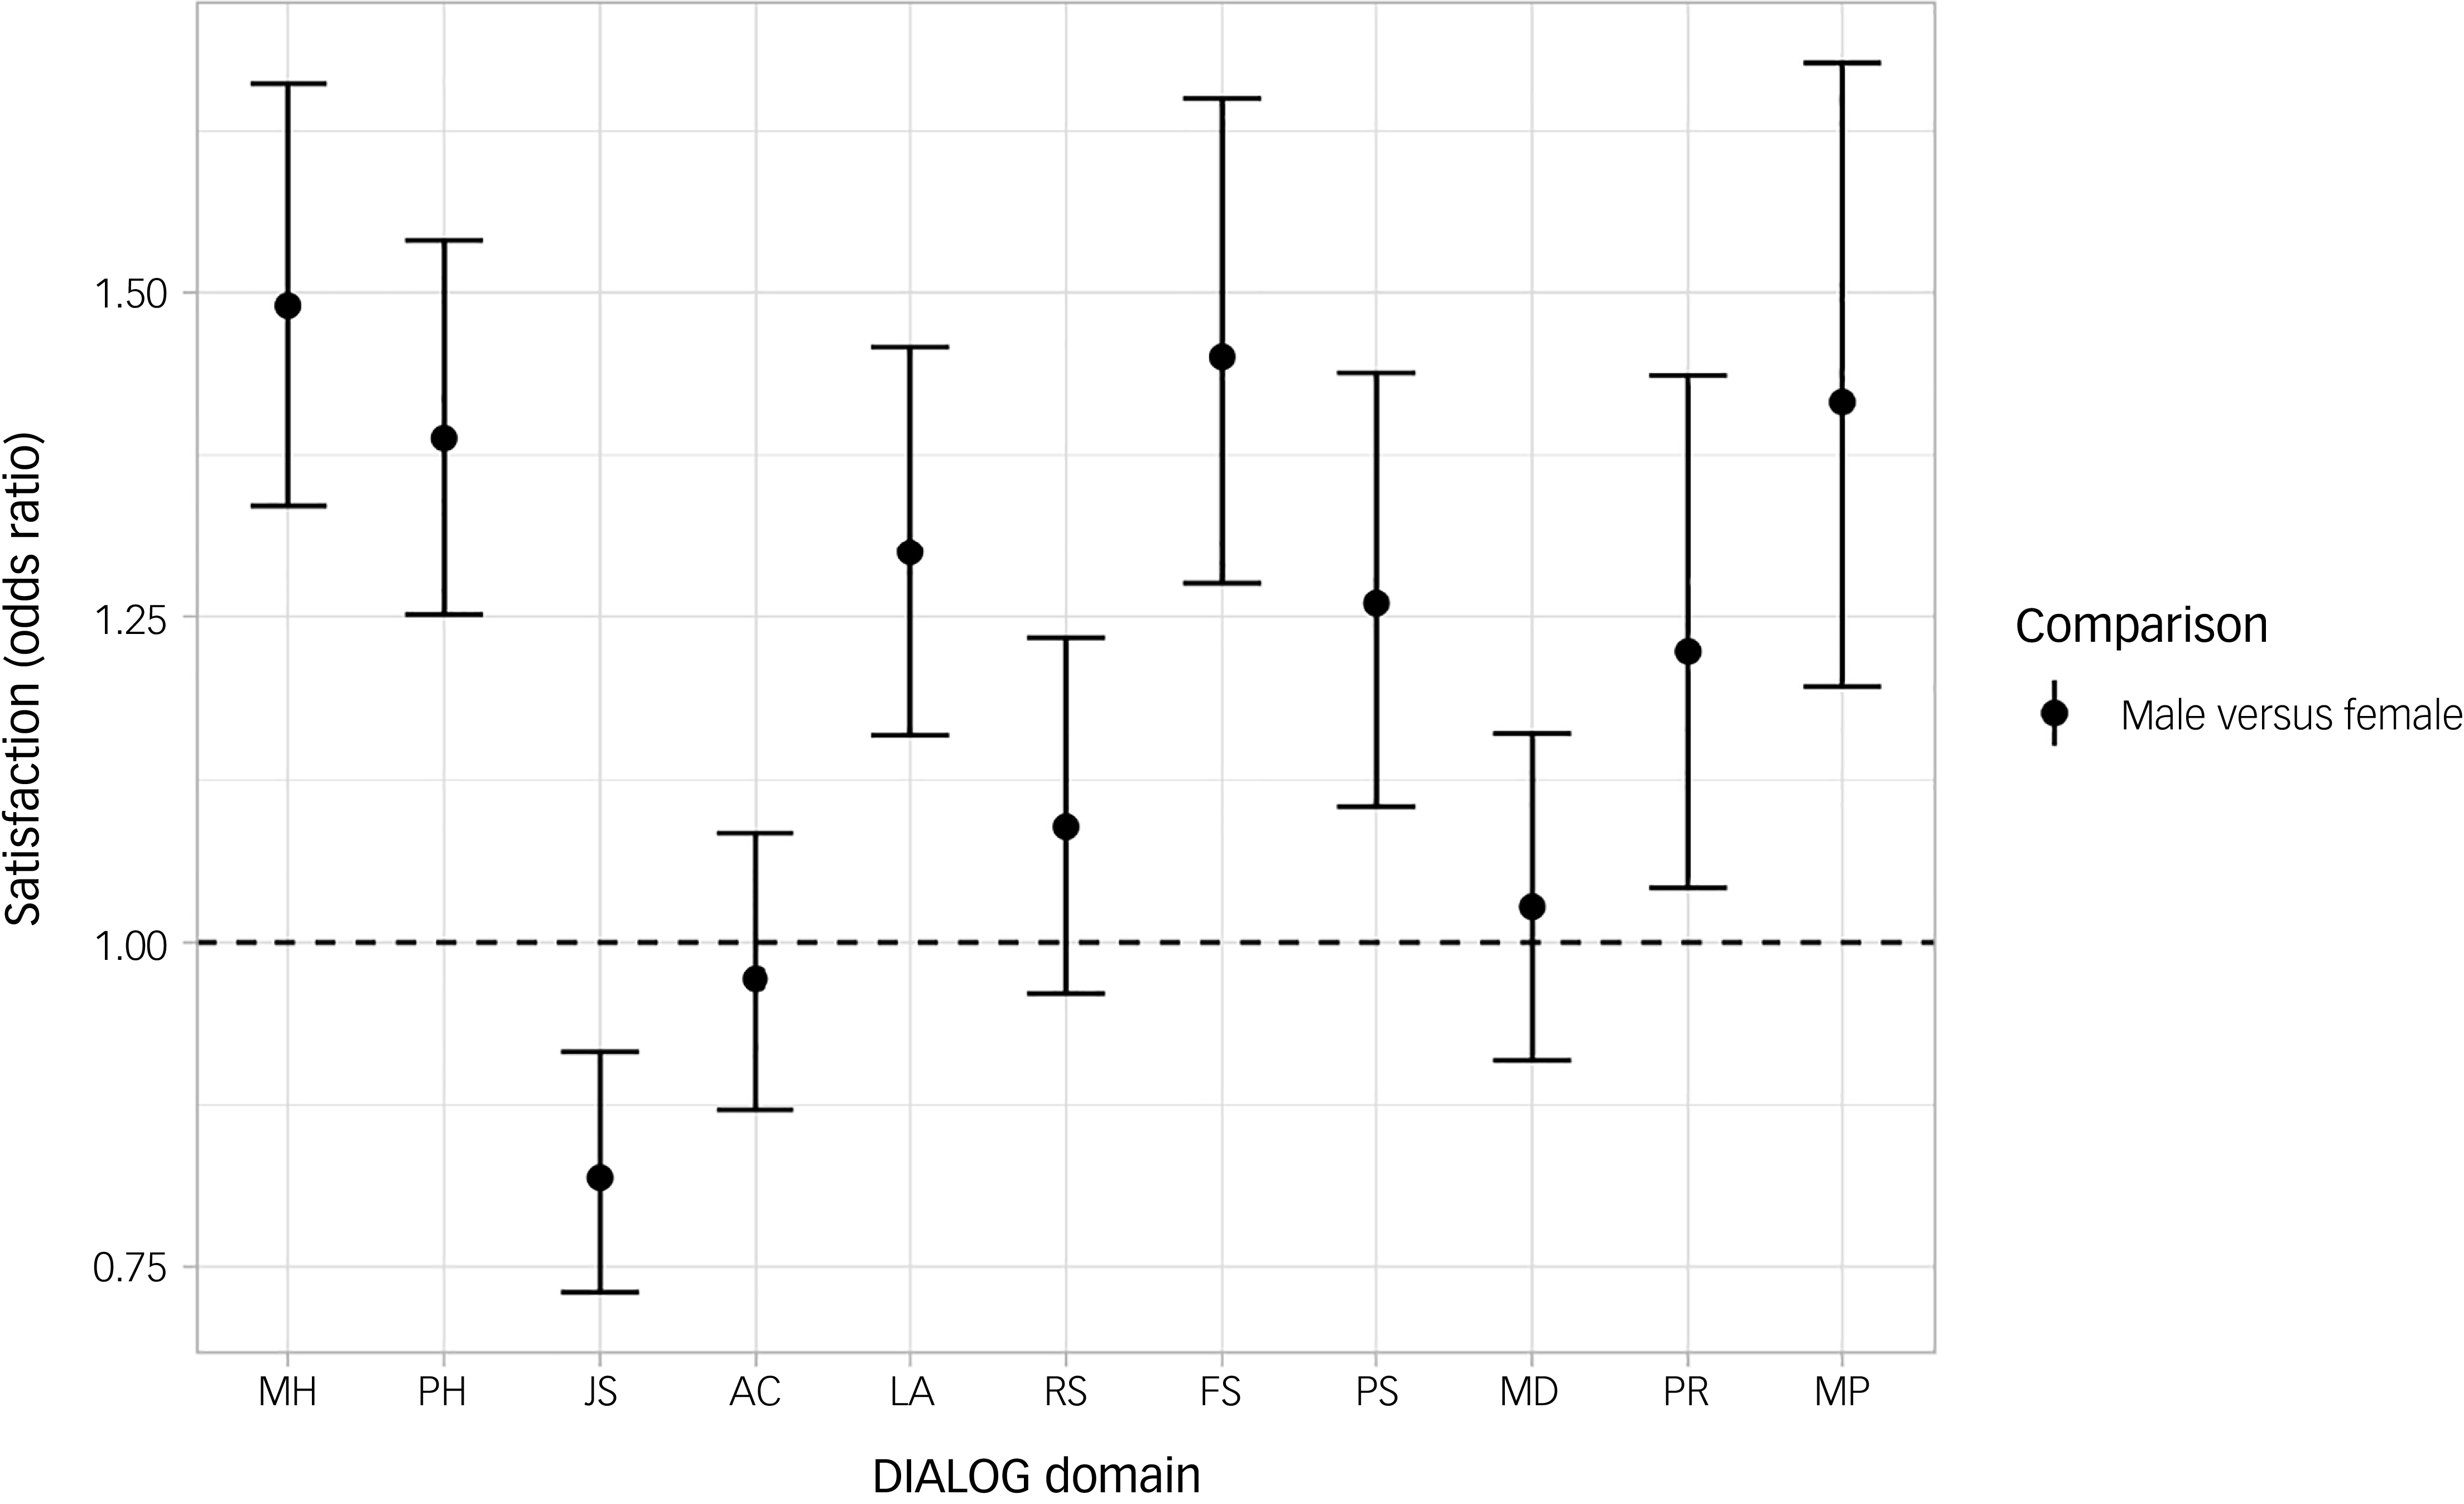
For regression analysis, we compared scores from men and women across the time periods and stages of treatment. We found that men had higher odds of being satisfied with their mental and physical health, leisure, friendships and personal safety, and with their experience of practical help and meetings with professionals (these differences reached statistical significance); women were more satisfied only with their job situation (Fig. 7).
Results of multiple regressions evaluating the influence of gender on DIALOG scores. Higher values indicate higher odds of satisfaction in each DIALOG domain. Whiskers are 95% confidence intervals; when whiskers are >1, this variable is significantly associated with greater odds of being satisfied; and if <1, it is associated with lower odds of being satisfied. Intermediate values are not significant. All predictor variables are all labelled to show what they are being compared against: e.g. ‘male versus female’ means that male is the predictor variable and female is what we are comparing it against. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Age
Regression analysis of the effect of age on the various domains of the DIALOG scale is shown in Fig. 8. Our analysis showed statistically significant odds of increased satisfaction with increased age (i.e. with 1-year increase in age holding all other variables constant) across multiple domains, including mental health, job situation, accommodation status and friendships, as well as the PREMs domains of experience of medication and experience of interaction with professionals. Older age was linked to lower satisfaction with physical health.
Results of multiple regressions evaluating the influence of age on DIALOG scores. Higher values indicate higher odds of satisfaction in each DIALOG domain. Whiskers are 95% confidence intervals; when whiskers are >1, this variable is significantly associated with greater odds of being satisfied; and if <1, it is associated with lower odds of being satisfied. Intermediate values are not significant. Please refer to Table 1 for abbreviations denoting DIALOG domains.

Discussion
DIALOG is a patient-reported measure for quality-of-life domains and treatment experiences. Within the quality-of-life domains, physical and mental health relate to the respective aspects of our perceived health and well-being, with the remaining six domains closely aligned with the social determinants of health; and, finally, there are three questions rating the experience of care and support received. We compared differences in these between patient groups when separated by ethnicity, gender, age and deprivation. Whereas the two periods of data gathering (2018–2019 and 2021–2022) were pre- and post-service reconfiguration, respectively, these also preceded and succeeded (or in the later period) the COVID-19 pandemic.
Ethnicity
We found that Black and Asian patients reported higher satisfaction across several quality-of-life and treatment-experience domains compared with White patients. However, Asian patients reported lower physical health satisfaction in 2021–2022. This is consistent with reports of increased morbidity resulting from the COVID-19 pandemic reported among Asian people. Reference Sapey, Gallier, Mainey, Nightingale, McNulty and Crothers26
At discharge, no significant differences were observed between ethnic groups. This may be due to small sample sizes (only 240 discharge records across both years, of which 97 were White, 44 Asian and 57 Black). Alternatively, the effect of treatment may have mitigated earlier disparities.
Research consistently shows health inequalities among minoritised ethnic groups. However, most research focuses on poor public health outcomes, Reference Raleigh27 physical health outcomes Reference Shah and Kanaya28 and barriers to accessing care, Reference Kapadia, Zhang, Salway, Nazroo and Booth29 alongside experience of primary care. Reference Hayanga, Stafford and Bécares30,Reference O’Dowd31 NHS Digital data have shown a greater likelihood of Black ethnic groups receiving treatment following detention under the Mental Health Act. 32 On the other hand, data from primary care patient experience statistics (GP services) show that Black ethnic groups (both Black African and Black Caribbean) reported a positive overall experience (often similar to, or slightly below, the level of White British patients). For example, in the 2020–2021 UK GP Patient Survey, Black African patients had the highest reporting level of a positive overall GP service experience (at 86.2%), whereas Pakistani and Bangladeshi ethnicities reported the lowest rates of satisfaction. 33
In other published research, worse outcomes for ethnic minorities are partly explained by associations between ethnicity and socioeconomic status: minoritised communities are more likely to suffer from socioeconomic deprivation which, in turn, is associated with poor health outcomes. Nevertheless, ethnicity-based health inequalities persist even after adjusting for deprivation. Reference Evandrou, Falkingham, Feng and Vlachantoni34
Challenges to accessing care for minority ethnic groups are due to a range of reasons (perceived and institutional), including health beliefs within the community, stigma and service configuration. Reference Winsper, Bhattacharya, Bhui, Currie, Edge and Ellard35 When researching SMI populations, most research focuses on patient experiences in in-patient units (alongside coercion). Reference Bennewith, Amos, Lewis, Katsakou, Wykes and Morriss36 Delay in help-seeking for mental health might further contribute to increased acuity and perpetuate coercion. Perceived lack of trust and poor experience have been identified in qualitative studies. Reference Bhui, Mooney, Joseph, McCabe, Newbigging and McCrone37
However, there is little research with the community on mental health patients with SMI. The Patient and Carer Race Equality Framework highlights the need to examine inequities in access, experience and outcomes. 38 Unfortunately previous large-scale PROM data analyses did not explore differences between groups. Reference Bull, Teede, Watson and Callander5–Reference Bull and Callander7,Reference Mosler, Priebe and Bird19,Reference Amat-Fernandez, Pardo, Ferrer, Bosch, Lizano-Barrantes and Briseño-Diaz39–Reference Coelho, de Bienassis, Klazinga, Santo, Frade and Costa41 We did not find any published research on variation in PROMs and PREMs scales in a community SMI cohort.
Minoritised ethnic groups are diverse, and the way in which a particular minority group interacts with the wider society is often unique; interpretation of findings is therefore complex. Our findings contrast with those from the USA of Kaur et al, who reported that, compared with White non-Hispanic patients, ethnoracial minorities had worse outcomes in regard to mental health after adjusting for age, gender, education, employment, marital status, comorbidities and insurance type. Reference Kaur, Zeng, Malapati, McCleary, Meyers and Bryant42 There is a risk of oversight or misunderstanding if we group all minority ethnic groups’ data in one box. We need to be mindful that there are variations across countries and systems, and that these may not be generalisable across countries. For instance, the New Zealand Attitudes and Values Study (2019) found higher satisfaction among Māori and Pasifika patients after adjusting for cultural respect and ethnic concordance compared with the European-descended majority. Reference Lee and Sibley43
People struggling with SMI often face severe social disadvantages. There is some evidence that poor, marginalised White people, especially young men, face significant adversities. Health inequity is complex. Our findings do not disprove the health inequities faced by minoritised communities, especially in regard to accessing treatment, facing discrimination or having disproportionate experience of coercive treatment. Our findings, however, offer the perspective of minoritised communities’ experience of quality of life and its change through treatment and treatment experience. DIALOG scales are more likely to have been collected from those who engaged in overcoming the barriers to access. We found that, when patients with SMI engaged with care and treatment, those from minoritised communities had good outcome and experience. This offers hope that, when engaged, there is no reason to aspire and expect positive outcomes in patients with SMI from minoritised communities. Possible explanations of our findings may be related to local improvement in service provisions in east London, with several decades of research and work focusing on cultural sensitivity Reference Bhui, Owiti, Palinski, Ascoli, De Jongh and Archer44 and co-production. We believe that mental health services should continuously monitor and analyse outcomes to investigate how those facing the most adversities are being served.
Gender
Men reported lower mental and physical health satisfaction in 2021–2022 versus 2018–2019, but were more satisfied than women in multiple domains including health, social, safety and experience; women were more satisfied than men in one domain, job situation. Our findings of women reporting higher levels of dissatisfaction with their care is not consistent with primary care surveys. 45
At discharge, men were less satisfied in 2021–2022 compared with 2018–2019, especially in regard to medication and their experiences with mental health professionals.
Socioeconomic deprivation
Patients from more deprived socioeconomic areas had lower satisfaction across several domains of quality of life; however, the impact on the mental health domain was not statistically significant.
We used IMD as a proxy measure of deprivation. IMD does not offer the most sensitive measure at the individual level, and is known to be a relatively insensitive and blunt tool in capturing true deprivation. Reference McCartney, Hoggett, Walsh and Lee46 Future research should investigate improved measures to capture socioeconomic deprivation more accurately. The Patient and Carer Race Equality Framework highlights the need to examine inequities in access, experience and outcomes. 38
Age
Our finding of older population reporting greater satisfaction is consistent with previous studies, e.g. in primary care where younger age is associated with lower levels of satisfaction. Reference Kontopantelis, Roland and Reeves47
Broader findings
DIALOG, as a self-reported outcome and experience measure collected from a subgroup of patients with SMI, may not be able to capture the full set of nuances and interacting factors that influence health inequalities. We are aware that one of the major barriers to healthcare resulting in health inequality is access. Reference Winsper, Bhattacharya, Bhui, Currie, Edge and Ellard35 Routinely, DIALOG may have some limitations in detecting changes in satisfaction level if initial levels of satisfaction in a domain are high. Intersectionality and added disadvantages resulting from socioeconomic deprivation, immigration, language barriers and poor physical health outcome may not be completely adjusted through the logistic regression carried out.
Limitations
Although we recognise that differences between groups in a domain could represent a variation caused by a range of potential factors including perceived need and dissatisfaction, which can be a proxy for health inequity, we also recognise that the findings can be influenced by a range of factors and confounders. The proportion of patients for whom we had access to their DIALOG scores was low (15–16%).
It is also likely that those who were more satisfied with treatment and engaged with services introduced a positive bias into the pooled results. However, this is likely to hold true for all subgroups and therefore should not particularly bias the analysis between subgroups.
About the authors
Rahul Bhattacharya is a consultant psychiatrist with East London NHS Foundation Trust, London, UK, Honorary Associate Clinical Professor at Warwick Medical School, University of Warwick, Coventry, UK and Specialist Advisor on MH Payments and Incentives for RCPsych. Stuart G. Spicer is a senior research fellow in applied healthcare at the University of Plymouth Community & Primary Care Research Centre, Plymouth, UK and PenARC, Plymouth, UK. Akshith Shetty is a consultant psychiatrist at North East London NHS Foundation Trust, London, UK. Katelyn Smalley is a data analyst in healthcare and was a researcher at the University of Plymouth, Plymouth, UK at the time of this study. Paul Sharpe was a researcher in psychology and applied healthcare at the University of Plymouth, Plymouth, UK at the time of this study. Richard Byng is Professor in Primary Care Research at the University of Plymouth, Plymouth, UK, Head of the University of Plymouth Community & Primary Care Research Centre, Plymouth, UK and Deputy Director, PenARC, Plymouth, UK.
Supplementary material
The supplementary material is available online at https://doi.org/10.1192/bjb.2026.10268
Data availability
Additional data have been added as Supplementary material. Further data are available from S.S., on reasonable request.
Acknowledgements
The authors thank Professor Stefan Priebe for his advice on this paper; Professor Frank Rohricht, Medical Director for Research and Innovation at the East London NHS Foundation Trust (ELFT), who commissioned the initial analysis and agreed on further analysis; and Thomas Nicholas, Associate Director for Business Intelligence and Analytics, ELFT, for help with the data search.
Author contributions
R. Bhattacharya contributed substantially to the conception, literature review, data acquisition and interpretation of the study. S.S. led the statistical analysis and contributed substantially to the review of paper. A.S. carried out the literature review and the review of the document. K.S. and P.S. supported statistical analysis. R. Byng was involved in the initial idea for the paper, and offered advice and supervision. All authors give permission for the final version to be published.
Funding
The ELFT commissioned the University of Plymouth to conduct this evaluation. S.S., R. Byng, K.S. and P.S. were additionally funded and supported by the National Institute for Health & Care Research Applied Research Collaboration South West Peninsula.
Declaration of interest
R. Bhattacharya is a member of the BJPsych Bulletin editorial board, but did not take part in the review or decision-making process of this paper. R. Bhattacharya and A.S. are employed by the ELFT and participated in the evaluation without additional payment.
Ethical standards
ELFT commissioned the University of Plymouth to evaluate routinely collected community mental health team data, to assess the impact of community mental health transformation as recommended by NHS England. Because these routinely collected data were part of a commissioned local evaluation rather than research (i.e. classed as service evaluation rather than research under the UK Policy Framework for Health and Social Care Research), ethical approval was not required (as per Health Research Authority standards and agreed by the ELFT Ethics Committee). Data-sharing agreement on the evaluation was detailed within the terms of the contract.




 Open access


eLetters
No eLetters have been published for this article.