


Kindness, empathy and compassion are widely recognised as essential qualities in mental healthcare, because they shape therapeutic relationships and improve patient outcomes. Reference Elliott, Bohart, Watson and Murphy1–Reference Goetz, Keltner and Simon-Thomas3 Empathy is similarly associated with improved recovery outcomes and therapeutic alliance. Reference Elliott, Bohart, Watson and Murphy1 For clinicians themselves, these qualities are linked to reduced emotional strain and greater professional reward, offering some protection against burnout. Reference Maslach2
Empathy, compassion and kindness are related but distinct constructs. Empathy involves the ability to perceive and understand another person’s emotional state and is directly linked to alliance and communication. Compassion extends beyond understanding to include a motivational component and is often examined alongside self-compassion, which involves directing the same attitudes inwards. Reference Goetz, Keltner and Simon-Thomas3–Reference Strauss, Lever Taylor, Gu, Kuyken, Baer and Jones5 Kindness is broader still, referring to deliberate prosocial actions that demonstrate care and respect for others, and in healthcare it is increasingly conceptualised in action-oriented terms, sometimes described as ‘intelligent kindness’. Reference Curry, Rowland, Van Lissa, Zlotowitz, McAlaney and Whitehouse6 Intelligent kindness emphasises not only empathic understanding but also the deliberate, action-oriented application of kindness within healthcare. Reference Ballatt and Campling7
Despite their importance, mental health professionals face significant challenges in maintaining empathy and compassion due to high levels of stress and burnout. Reference Maslach2 Evidence shows that compassion-based programmes can foster resilience, enhance positive affect and improve overall well-being. Reference Kirby, Tellegen and Steindl8,Reference Klimecki, Leiberg, Lamm and Singer9 However, most existing interventions have not fully addressed cultural adaptation, despite its importance in ensuring that mental healthcare is relevant and inclusive for diverse populations.
The aim of this rapid review was to explore the available evidence on culturally informed interventions designed to enhance kindness, empathy and compassion among mental health professionals.
Methods
Study design
We conducted a rapid review to synthesise evidence on culturally informed interventions intended to enhance kindness, empathy or compassion among mental health professionals. Reference Stevens, Hersi, Garritty, Hartling, Shea and Stewart10 The review followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 statement and was further informed by Cochrane Rapid Review Guidance, which provides practical recommendations for maintaining transparency, methodological rigour and efficiency in rapid evidence syntheses. Interventions were defined as either initiatives, projects, structured programmes, tools or validated frameworks in this domain. The review focused on mental health professionals across psychiatrists, psychologists, nurses and allied health workers in the mental health field.
Protocol and registration
This rapid review was prospectively registered on OSF (DOI: https://doi.org/10.17605/OSF.IO/U6H32) on 14 August 2025. Reference Nawaz, Usman, Usman, Bokhari, Ahmed and Ahmed11
Eligibility criteria
Eligible studies were either original quantitative, qualitative or mixed-methods investigations (including cohort, case–control, cross-sectional, randomised controlled trials and non-randomised designs) published in English between January 2014 and August 2025. Populations were mental health professionals (psychiatrists, psychologists, therapists, psychiatric nurses and allied health staff). Interventions were culturally informed initiatives, programmes, tools or validated frameworks aiming to enhance kindness, empathy or compassion towards colleagues and/or patients. Eligibility outcomes included measures of kindness, empathy, compassion, therapeutic alliance, job satisfaction (professional well-being), patient satisfaction, cultural safety, team cohesion and collegial trust. We excluded studies of non-mental health populations, review articles, editorials and non-English publications.
Search strategy
A systematic search was conducted in PubMed/MEDLINE and PsycINFO in August 2025. Search terms included ‘mental health professionals’, ‘psychiatrists’, ‘psychologists’, ‘therapists’, ‘psychiatric nurses’ and ‘allied health professionals’, combined with terms related to ‘empathy’, ‘compassion’ and ‘kindness’. This comprehensive strategy enabled the identification of both explicitly cultural and implicitly humanistic interventions aimed at enhancing culturally responsive mental healthcare.
Study selection and data extraction
Screening followed the 2020 PRISMA statement. Reference Page, McKenzie, Bossuyt, Boutron, Hoffmann and Mulrow12,Reference Page, Moher, Bossuyt, Boutron, Hoffmann and Mulrow13 One reviewer screened titles, abstracts and full texts against eligibility criteria; a second member verified data extraction for included records. Screening and record management were undertaken using the Rayyan systematic review web application (Rayyan Systems Inc., Cambridge, Massachusetts; https://www.rayyan.ai/). Reference Ouzzani, Hammady, Fedorowicz and Elmagarmid14 Data were extracted into a Microsoft Excel template (version 16.112 (26070718), macOS; Microsoft Corporation, Redmond, Washington, USA; https://www.microsoft.com/microsoft-365/excel) by one reviewer and cross-checked by a second. Any discrepancies between reviewers were resolved through discussion and, where consensus could not be reached, a third reviewer was consulted. Screening and subsequent data extraction commenced on 15 August 2025.
Data items
Extracted data included study characteristics (country, setting, design, sample size, demographics), intervention description (materials, procedures, providers, mode, location, tailoring), implementation information (structure or dose, frequency, session length, fidelity where reported), outcomes and instruments and details of cultural adaptation features.
Intervention description and cultural adaptation frameworks
Data extraction was conducted using Microsoft Excel and tailored based on two validated frameworks: the Template for Intervention Description and Replication (TIDieR) checklist was utilised to improve the completeness of intervention reporting in research. Reference Hoffmann, Glasziou, Boutron, Milne, Perera and Moher15 This incorporates variables related to the intervention applied, including the materials used, dissemination format, provider and participant characteristics and strategies used to measure adherence to the process. The Bernal and Sáez-Santiago Ecological Validity Model (EVM) was also integrated due to its emphasis on cultural adaptation of interventions in research. Although originally developed for adapting psychological interventions for patients, its eight dimensions were modified to suit this review’s professional training context. Modified EVM domains included culturally appropriate language, diversity among professionals, cultural knowledge, context and methodology. Outcomes related to kindness, compassion, empathy, job satisfaction, cultural safety, collegial trust and team dynamics were also extracted. Demographic data included sample size, mean age, gender distribution and study design.
Outcomes and measures
Primary domains were kindness (other-directed), empathy and compassion (other-directed). Secondary outcomes included therapeutic alliance, job satisfaction (professional well-being), patient satisfaction, cultural safety, team cohesion and collegial trust. Instruments were catalogued and classified by respondent type (self-report, observer-rated or patient-reported). Qualitative findings, including focus group data, were summarised thematically. Risk of bias assessment was not incorporated, consistent with the rapid review format.
Data analysis
A narrative synthesis was undertaken in accordance with Synthesis Without Meta-analysis (SWiM) guidance. Reference Campbell, McKenzie, Sowden, Katikireddi, Brennan and Ellis16 Meta-analysis was not attempted due to the heterogeneity of designs/measures and incomplete dispersion reporting. For each prespecified outcome, inferential statistical results were prioritised where available; otherwise, descriptive changes in means, proportions or qualitative themes were reported. Where multiple measures existed within the same outcome domain, findings were summarised narratively rather than pooled. Qualitative insights were used to contextualise quantitative results. Implementation features were summarised via TIDieR, and cultural adaptation assessed using EVM. No data transformation or imputation was performed.
EVM coding rules
Each EVM item was coded as either ‘Yes’, ‘Partially’, ‘No’ or ‘Not Applicable (N/A)’ using pre-specified thresholds. ‘Yes’ indicated sufficient detail, demonstrating that the element was fully addressed (e.g. translated or bilingual materials, simultaneous interpretation or culturally specific content such as a Ukraine war-context course using local idioms). ‘Partially’ was applied when the element was acknowledged but superficially described (e.g. language translation without deeper adaptation or facilitator matching). ‘No’ indicated that the element was unaddressed. ‘N/A’ was reserved only when the element did not apply to the intervention format and was not used for missing data.
Results
Study selection
The initial database search yielded 556 records in PubMed and 134 in PsycINFO, resulting in 690 records. Following the removal of duplicates (n = 80), a total of 610 unique records were screened for eligible title and abstracts. Of these, 544 articles were excluded on the basis of either wrong study design, incorrect study outcomes or non-English studies. The final screening stage yielded 66 articles for full-text assessment. Following further screening and exclusion of irrelevant studies, four studies met all prespecified inclusion criteria and were included in the final rapid review (Fig. 1).
Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 flow diagram, including searches of databases.

Fig. 1 Long description
The flowchart illustrates the process of identifying studies via databases and registers for a systematic review. Panel A: Identification. Records identified from PubMed: 556 records, PsycINFO: 134 records, Total: 690. Records removed before screening: Duplicate records removed: 80. Panel B: Screening. Records screened by title and abstract: 610. Records excluded: 544. Panel C: Eligibility. Reports assessed for eligibility: Full-text articles assessed: 66. Reports excluded: Full-text articles excluded, with reasons: 62. Wrong intervention (54), Wrong outcome (6), Wrong population (1), Non-English (1). Panel D: Included. Studies included in review: 4.
Study characteristics and intervention structure
The 4 studies collectively involved 715 mental health professionals (Table 1). Two studies reported participant demographics. Lewis et al (US agency staff; n = 166) reported a mean age of 42.26 years (s.d. 12.82), with 28 men and 125 women. Reference Lewis, Myhra, Hartwell and Smith17 Rodríguez-González et al (Spanish-speaking emotionally focused therapy (EFT) cohort; baseline n = 207) reported a mean age of 42.32 years (s.d. 11.14), with 33 men and 174 women. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Characteristics of included studies, participants and providers

Table 1 Long description
The table has 4 rows and 10 columns. The columns are labeled: Title, First author, Study design, Country, Age of participants (mean), SD, Total participants, Number of male participants, Number of female participants, Ethnicity of participants, Occupation of participants, Number of male providers, Number of female providers. Row 1: Title, Effects of a decolonizing training on mental health professionals’ indigenous knowledge and beliefs and ethnocultural empathy; First author, Lewis et al (2023); Study design, Single arm pre- post-intervention; Country, USA; Age of participants (mean), 42.26; SD, 12.82; Total participants, 166; Number of male participants, 28; Number of female participants, 125; Ethnicity of participants, White/Caucasian, Mixed, Other, East Asian: Chinese, Japanese, Korean, Mongolian; Occupation of participants, 49.4 percent reporting a clinical position in mental health, 19.3 percent reporting an administrative/clerical position, and the rest distributed among human resources, information technology, maintenance, and other positions; Number of male providers, 0; Number of female providers, 3. Row 2: Title, Cross-cultural training program on mental health care for refugees - a mixed method evaluation; First author, McDonald et al (2021); Study design, Mixed method; Country, Sweden; Age of participants (mean), N/A; SD, N/A; Total participants, 248; Number of male participants, N/A; Number of female participants, N/A; Ethnicity of participants, N/A; Occupation of participants, Medical doctors/med. Students (6.0 percent), Social worker (15.7 percent), Psychologist/psychotherapist (30.6 percent), Nurses (21.3 percent), Auxiliary/psychiatric nurse aide (8.5 percent), Occupational therapist (2.0 percent), Physiotherapist (1.6 percent), Midwife (1.6 percent), Management (2.8 percent), Administrative staff (2.8 percent), Missing (5.6 percent); Number of male providers, N/A; Number of female providers, N/A. Row 3: Title, Engaging Ukrainian TF-CBT therapists in a PRACTICE skills course to support their wellbeing; First author, Pollio et al (2025); Study design, mixed method; Country, Ukraine; Age of participants (mean), N/A; SD, N/A; Total participants, 52; Number of male participants, N/A; Number of female participants, N/A; Ethnicity of participants, N/A; Occupation of participants, Therapists; Number of male providers, N/A; Number of female providers, N/A. Row 4: Title, Short-term and long-term effects of training in EFT: a multinational study in Spanish speaking countries; First author, Rodriguez-Gonzalez et al (2019); Study design, Longitudinal study; Country, Argentina, Costa Rica, Guatemala, Mexico, Panama, Spain; Age of participants (mean), 42.32; SD, 11.14; Total participants, 249, but 207 participated in the pre-intervention survey; Number of male participants, 33; Number of female participants, 174; Ethnicity of participants, White/Caucasian, Hispanic/Latino/Latin American; Occupation of participants, Psychotherapists and clinicians; Number of male providers, N/A; Number of female providers, N/A.
Country for Rodríguez-González et al refers to six Spanish-speaking sites (Argentina, Costa Rica, Guatemala, Mexico, Panama, Spain). EFT, Emotionally Focused Therapy; TF-CBT, Trauma-Focused Cognitive Behavioral Therapy; PRACTICE, Psychoeducation and Parenting skills, Relaxation, Affect expression and modulation, Cognitive coping, Trauma narration and processing, In vivo mastery, Conjoint parent–child sessions, and Enhancing safety and future development Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 ; N/A, data not reported.
McDonald et al (Sweden; n = 248) did not report demographic variables but described professional composition (psychologists/psychotherapists 30.6%, nurses 21.3%, social workers 15.7%, medical doctors/students 6.0% and other roles in smaller proportions). Reference McDonald, Dahlin and Bäärnhielm19 Pollio et al (Ukraine; n = 52) did not collect demographic data. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20
Ethnicity was reported in 2 studies: explicitly in Lewis et al, where 133 participants identified as White (80.1%), 10 as mixed (6.0%), 2 as Indigenous (1.2%) and 2 as Asian/Asian American (1.2%), with the remaining 19 (11.4%) selecting other categories or not responding; Reference Lewis, Myhra, Hartwell and Smith17 and categorically in Rodríguez-González et al (Hispanic/Latino/Latin American; White/Caucasian). Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 McDonald et al Reference McDonald, Dahlin and Bäärnhielm19 and Pollio et al Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 did not report ethnicity.
Occupational information was comprehensively reported in McDonald et al (Table 1). Reference McDonald, Dahlin and Bäärnhielm19 Lewis et al reported that 49.4% of participants were in clinical roles and 19.3% in administrative or clerical positions. Reference Lewis, Myhra, Hartwell and Smith17 Trainer or facilitator gender was not consistently reported across studies.
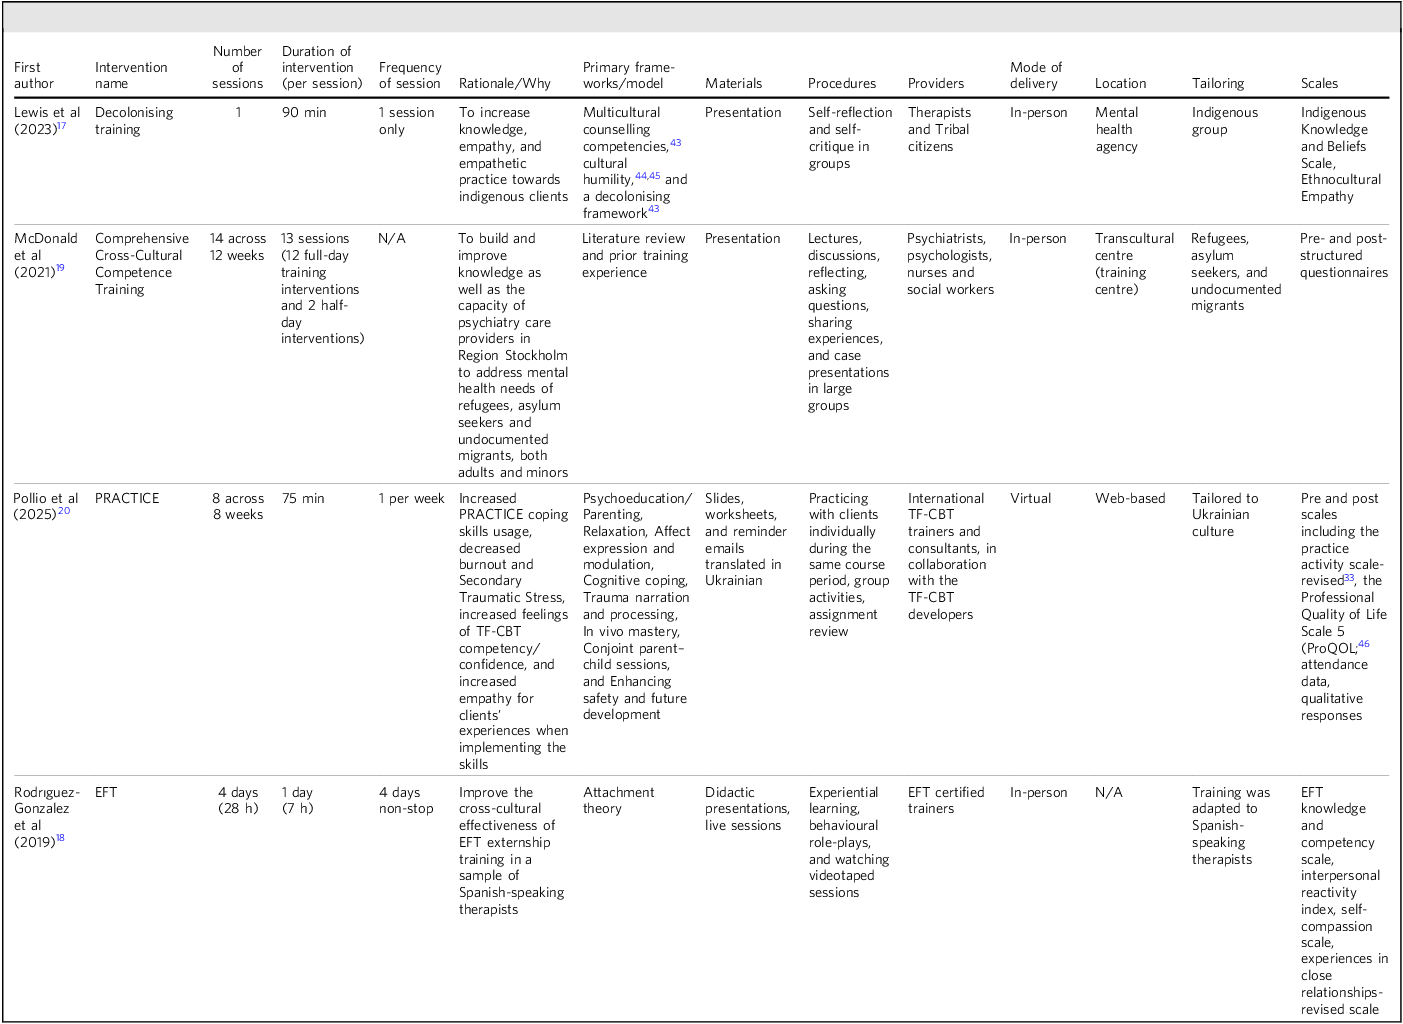
Four culturally informed training interventions were included (Table 2). The first was a 90 min, in-person, decolonising empathy workshop for community mental health staff in the USA. Reference Lewis, Myhra, Hartwell and Smith17 The second was a 14-session, in-person, ‘Comprehensive cross-cultural competence training’ course delivered over 12 weeks for providers working with refugees and asylum-seekers at a transcultural training centre in Sweden. Reference McDonald, Dahlin and Bäärnhielm19 The third was an eight-session, virtual trauma-focused CBT (TF-CBT) PRACTICE (the TF-CBT acronym for ‘Psychoeducation and Parenting skills, Relaxation, Affect expression and modulation, Cognitive coping, Trauma narration and processing, In vivo mastery, Conjoint parent–child sessions, and Enhancing safety and future development’, as described by Pollio et al Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 ) skills course delivered weekly to Ukrainian therapists during the ongoing conflict. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 The fourth was a 4-day, intensive (28 h total), EFT externship for Spanish-speaking clinicians conducted across Argentina, Costa Rica, Guatemala, Mexico, Panama and Spain. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Intervention characteristics and measurement instruments, organised by TIDieR items, for the four included training programs

Table 2 Long description
The table compares four culturally informed training interventions across various parameters. It has 4 rows and 11 columns. The columns are labeled as First author, Intervention name, Number of sessions, Duration of intervention (per session), Frequency of session, Rationale/Why, Primary frameworks/model, Materials, Procedures, Providers, Mode of delivery, Location, Tailoring, and Scales. The rows detail the interventions by Lewis et al (2023), McDonald et al (2021), Pollito et al (2025), and Rodriguez-Gonzalez et al (2019). Each row provides specific information about the intervention’s sessions, duration, frequency, rationale, frameworks, materials, procedures, providers, mode of delivery, location, tailoring, and scales used.
TIDieR, Template for Intervention Description and Replication; EFT, Emotionally Focused Therapy; TF-CBT, Trauma-Focused Cognitive Behavioral Therapy; N/A, data not reported.
Study designs comprised one single-group, pre–post evaluation, Reference Lewis, Myhra, Hartwell and Smith17 two mixed-methods evaluations Reference McDonald, Dahlin and Bäärnhielm19,Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 and one longitudinal cohort study with 6-month follow-up. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 Three interventions were delivered in-person Reference Lewis, Myhra, Hartwell and Smith17–Reference McDonald, Dahlin and Bäärnhielm19 and one online. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 Baseline sample sizes ranged from 52 to 249 mental health professionals. All interventions aimed to enhance providers’ interpersonal skills (such as empathy or cultural sensitivity) through training workshops or courses.
All interventions sought to enhance culturally responsive professional capabilities, with an emphasis on empathy. The decolonising workshop drew on multicultural counselling competencies, cultural humility and decolonising frameworks to improve knowledge and empathic practice with Indigenous clients. The Swedish course aimed to build providers’ capacity to meet refugee mental health needs by addressing culture, trauma and interpreter-mediated care. The Ukrainian TF-CBT course by Pollio et al targeted increased use of PRACTICE coping skills, reduced burnout and secondary traumatic stress, greater TF-CBT competency and confidence and increased empathy for clients’ experiences. The EFT externship by Rodríguez-González et al aimed to evaluate EFT training effectiveness for Spanish-speaking therapists while maintaining core attachment-based and experiential principles.
Materials included translated slides and handouts with simultaneous interpretation; Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 bilingual training materials and standard EFT externship manuals; Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 case vignettes and module content on culture, trauma and interpreter work; Reference McDonald, Dahlin and Bäärnhielm19 and a decolonising lesson plan-based workshop. Reference Lewis, Myhra, Hartwell and Smith17
Teaching modalities combined didactic teaching with interactive methods: brief reflective exercises and group dialogue; Reference Lewis, Myhra, Hartwell and Smith17 multi-module classroom teaching with case discussions and practice; Reference McDonald, Dahlin and Bäärnhielm19 weekly skills teaching and between-session practice aligned with PRACTICE components; Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 and lectures, demonstrations/role-plays and supervised practice according to the EFT externship format. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 Settings included a community mental health agency, a regional transcultural training centre, a nationwide web-based platform and in-person externships conducted across six Spanish-speaking sites in Argentina, Costa Rica, Guatemala, Mexico, Panama and Spain. Three interventions were delivered in person; Reference Lewis, Myhra, Hartwell and Smith17–Reference McDonald, Dahlin and Bäärnhielm19 that of Pollio et al was delivered fully online as a synchronous virtual course. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20
Facilitator backgrounds varied. The decolonising workshop was developed by Indigenous authors in the study; facilitator cultural background was not reported. The Swedish course by McDonald et al was delivered by health professionals at a transcultural training centre; cultural matching to refugee backgrounds was not indicated. Pollio et al’s Ukrainian TF-CBT course was delivered by international TF-CBT trainers and consultants, with simultaneous interpretation; some sessions involved local co-facilitation. Rodríguez-González et al’s EFT externship was led by bilingual certified EFT trainers.
Cultural adaptation: EVM mapping
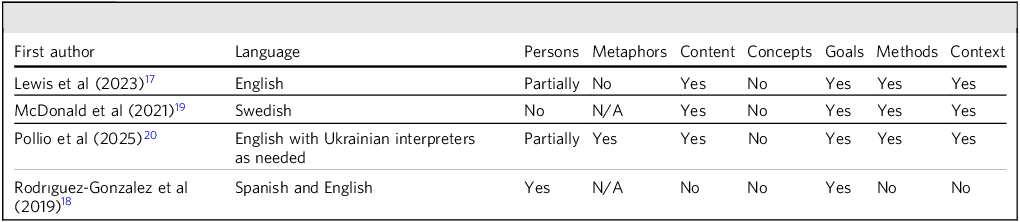
Each intervention was mapped to the eight EVM dimensions to characterise cultural adaptation: language (use of participants’ first or working language); persons (cultural background of facilitators); metaphors (incorporation of culturally specific symbols or sayings); content (integration of cultural history and relevant examples); concepts (adaptation of theoretical constructs); goals (alignment with cultural priorities); methods (culturally appropriate delivery techniques); and context (acknowledgment of sociopolitical factors). All four studies reported at least one EVM-aligned element, although the breadth and emphasis varied by setting and target population (Table 3).
Ecological Validity Model (EVM) mapping of cultural adaptation features across the four included interventions

Table 3 Long description
A table with four rows and eight columns mapping cultural adaptation features across four interventions using the Ecological Validity Model dimensions. The columns are labeled Language, Persons, Metaphors, Content, Concepts, Goals, Methods, and Context. The rows are labeled with the first author and year of the study. Row 1: Lewis et al (2023), English, Partially, No, Yes, No, Yes, Yes. Row 2: McDonald et al (2021), Swedish, No, N/A, Yes, No, Yes, Yes. Row 3: Pollio et al (2025), English with Ukrainian interpreters as needed, Partially, Yes, Yes, No, Yes, Yes. Row 4: Rodriguez-Gonzalez et al (2019), Spanish and English, Yes, N/A, No, No, Yes, No.
Columns indicate EVM dimensions. N/A, data not reported.
Language: training was delivered in English to largely non-Indigenous staff, Reference Lewis, Myhra, Hartwell and Smith17 in Swedish, Reference McDonald, Dahlin and Bäärnhielm19 with English sessions and simultaneous Ukrainian interpretation plus translated materials, Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 and in Spanish with some bilingual materials. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Persons: cultural matching of facilitators was not reported in Lewis et al (authors were Indigenous, facilitator background not specified). Reference Lewis, Myhra, Hartwell and Smith17 In McDonald et al, trainers were health professionals with no reported refugee background. Reference McDonald, Dahlin and Bäärnhielm19 Partial matching occurred in Pollio et al through a mix of international and local co-facilitators. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 In Rodríguez-González et al, bilingual certified EFT trainers delivered the externship. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Metaphors: only Pollio et al Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 reported the use of culturally specific metaphors incorporating local sayings and examples.
Content: Lewis et al Reference Lewis, Myhra, Hartwell and Smith17 provided the most extensive adaptation, integrating Indigenous history, colonisation and reflective exercises grounded in decolonising frameworks. McDonald et al Reference McDonald, Dahlin and Bäärnhielm19 emphasised refugee experiences and interpreter-mediated care. Pollio et al contextualised examples within Ukrainian culture and wartime realities. Rodríguez-González et al Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 retained standard EFT content with language adjustments.
Concepts: core theoretical constructs were preserved across studies. Lewis et al Reference Lewis, Myhra, Hartwell and Smith17 used standard empathy constructs; McDonald et al Reference McDonald, Dahlin and Bäärnhielm19 and Pollio et al Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 followed established CBT and TF-CBT models; Rodríguez-González et al maintained core EFT principles. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Goals: each intervention aligned its objectives with cultural priorities – improving care for Indigenous populations, Reference Lewis, Myhra, Hartwell and Smith17 for refugees, Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 supporting war-affected therapists Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 and expanding EFT training in Spanish-speaking regions. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Methods: delivery techniques reflected cultural considerations where described. Lewis et al employed self-reflection and group dialogue. Reference Lewis, Myhra, Hartwell and Smith17 McDonald et al used interactive discussion and narrative approaches. Reference McDonald, Dahlin and Bäärnhielm19 Pollio et al incorporated collective activities, peer support and pragmatic coping strategies. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 Rodríguez-González et al followed standard EFT pedagogy with lectures, demonstrations, role-plays and supervised practice. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Context: sociopolitical context was explicitly acknowledged in three studies. Lewis et al addressed historical trauma and colonisation; Reference Lewis, Myhra, Hartwell and Smith17 McDonald et al incorporated interpreter use and acculturation challenges; Reference McDonald, Dahlin and Bäärnhielm19 and Pollio et al recognised the shared trauma of ongoing war. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 Rodríguez-González et al focused primarily on language adaptation without explicit attention to broader sociocultural context. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
Study-level outcomes
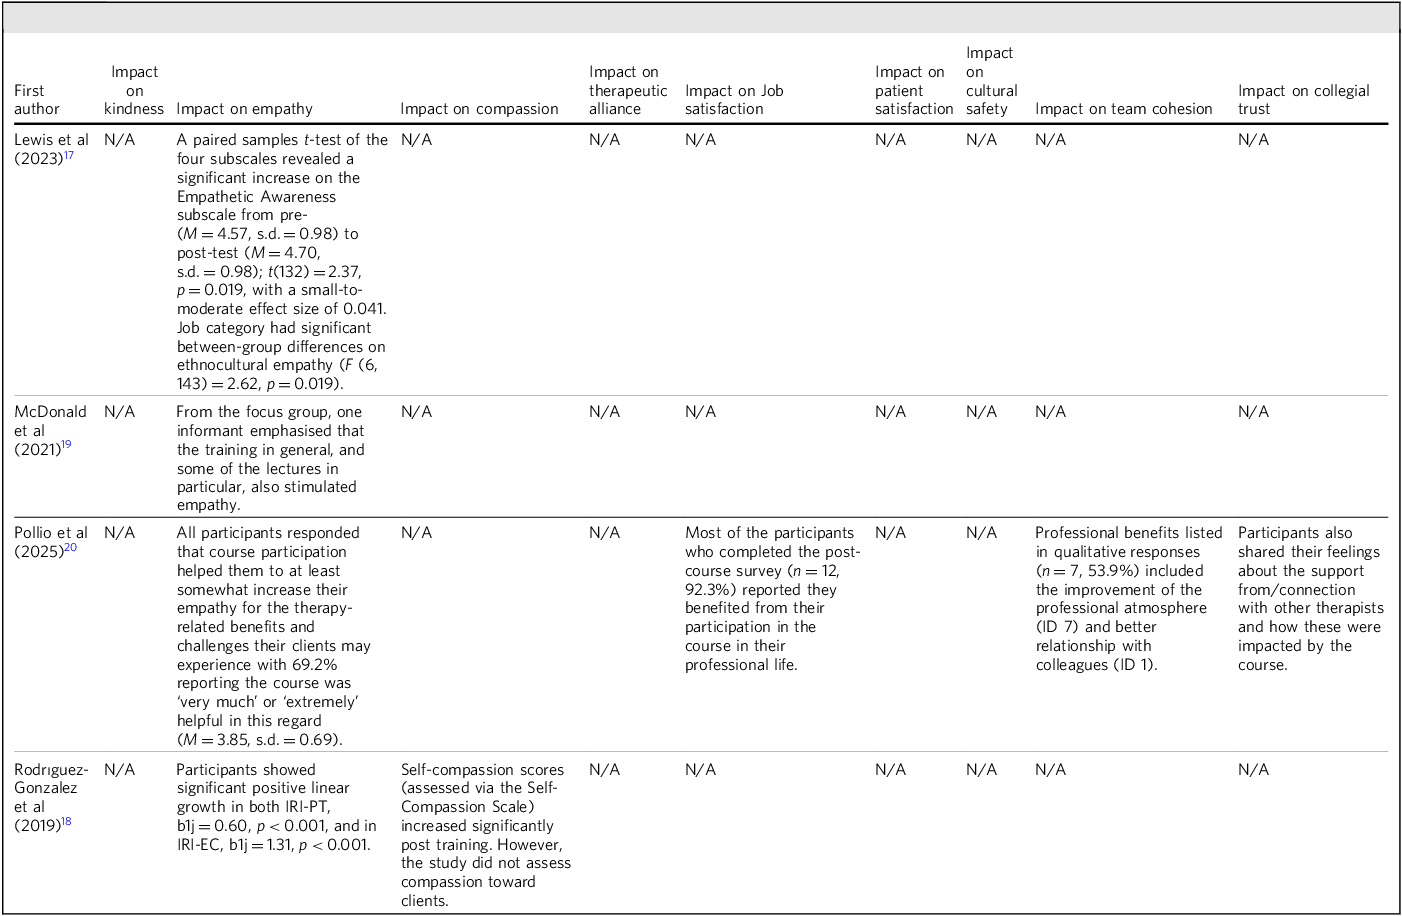
All four studies assessed empathy, with some also examining self-focused outcomes such as burnout or self-compassion (Table 4). Notably, kindness and compassion (towards patients or colleagues) were not directly measured in any study, despite their potential relevance to the study outcomes, nor were patient-rated outcomes (patient satisfaction or therapeutic alliance).
Study-level outcomes for kindness and empathy across the four included interventions

Table 4 Long description
The table compares the impact of four studies on various outcomes related to kindness and empathy. It has 4 rows and 9 columns. The columns are labeled as follows: First author, Impact on kindness, Impact on empathy, Impact on compassion, Impact on therapeutic alliance, Impact on job satisfaction, Impact on patient satisfaction, Impact on cultural safety, Impact on team cohesion, and Impact on collegial trust. Each row corresponds to a different study. Row 1: Lewis et al (2023), N/A, A paired samples t-test of the four subscales revealed a significant increase on the Empathetic Awareness subscale from pre- (M = 4.57, SD = 0.98) to post-test (M = 4.70, SD = 0.98); (t(132) = 2.37, p = 0.019, with a small-to-moderate effect size of 0.041. Job category had significant between-group differences on ethnocultural empathy (F (6, 143) = 2.62, p = 0.019), N/A, N/A, N/A, N/A, N/A. Row 2: McDonald et al (2021), N/A, From the focus group, one informant emphasized that the training in general, and some of the lectures in particular, also stimulated empathy., N/A, N/A, N/A, N/A, N/A, N/A. Row 3: Pollio et al (2025), N/A, All participants responded that course participation helped them to at least somewhat increase their empathy for the therapy-related benefits and challenges their clients may experience with 69.2 percent reporting the course was ‘very much’ or ‘extremely’ helpful in this regard (M = 3.85, SD = 0.69)., N/A, N/A, Most of the participants who completed the post-course survey (n = 12, 92.3 percent) reported they benefited from their participation in the course in their professional life., N/A, Professional benefits listed in qualitative responses (n = 7, 53.9 percent) included the improvement of the professional atmosphere (ID 7) and better relationship with colleagues (ID 1)., Participants also shared their feelings about the support/connection with other therapists and how these were impacted by the course. Row 4: Rodriguez-Gonzalez et al (2019), N/A, Participants showed significant positive linear growth in both IRI-PT, b1j = 0.60, p < 0.001, and in IRI-EC, b1j = 1.31, p < 0.001., Self-compassion scores (assessed via the Self-Compassion Scale) increased significantly post-training. However, the study did not assess compassion toward clients., N/A, N/A, N/A, N/A, N/A.
SEE, Scale of Ethnocultural Empathy; IRI-PT, Interpersonal Reactivity Index, Perspective Taking; IRI-EC, Interpersonal Reactivity Index, Empathic Concern; N/A, data not reported. Percentages in Pollio et al (2025) refer to participants who completed the post-course survey.
All four studies reported positive changes in empathy, although the nature and strength of the evidence varied.
-
(a) McDonald et al (Sweden): quantitative analysis did not find a significant pre–post change in knowledge scores regarding refugee mental health, but qualitative feedback suggested improved empathy and professional confidence in refugee care. Reference McDonald, Dahlin and Bäärnhielm19
-
(b) Rodríguez-González et al (Spanish-speaking countries): significant post-training increases were observed in perspective-taking and empathic concern on the interpersonal reactivity index, sustained at 6-month follow-up. Self-compassion also improved (self-compassion scale), although attachment style did not change. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
-
(c) Lewis et al (USA): cultural knowledge increased significantly on the Indigenous knowledge and beliefs scale (mean difference 2.23, 95% CI [1.82, 2.64], t(140) = 10.73, p < 0.001, η 2 = 0.45). Overall ethnocultural empathy did not change significantly (p = 0.176), but the empathic awareness subscale improved (4.57 ± 0.98 to 4.70 ± 0.98; t(132) = 2.37, p = 0.019, η² = 0.041). No other outcomes (e.g. kindness or alliance) were assessed. Across studies, improvements were most consistent in empathy-related measures and qualitative accounts of increased cultural understanding, suggesting that culturally informed approaches may enhance empathic awareness and professional well-being even in diverse training contexts. Reference Lewis, Myhra, Hartwell and Smith17
-
(d) Pollio et al (Ukraine): 92% of participants reported professional benefits, including increased confidence and empathy. Among 13 therapists with matched data, coping skill use improved significantly (PRACTICE skills activity scale, p = 0.010). Burnout and secondary traumatic stress scores declined, but not significantly. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20
Discussion
This rapid review of 4 studies involving 715 mental health professionals found improvements in empathy following culturally informed training interventions, although none directly measured kindness or compassion. Three studies demonstrated clear gains in empathy, two quantitatively and one qualitatively, with one showing subscale-specific improvement without overall change. Across interventions, improvements appeared related to both training duration and cultural adaptation.
Lewis et al reported a significant increase in empathic awareness on the ethnocultural empathy scale (p = 0.019), although total empathy scores did not change. Reference Lewis, Myhra, Hartwell and Smith17 Rodríguez-González et al identified significant linear growth in the interpersonal reactivity index subscales (perspective taking and empathic concern) at 6-month follow-up. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 Pollio et al found that 92% of Ukrainian therapists reported professional benefits and empathy gains, supported by significant improvement in coping skills (p = 0.010). Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 McDonald et al found qualitative evidence of enhanced empathy and professional identity among providers serving refugees. Reference McDonald, Dahlin and Bäärnhielm19 Collectively, these findings suggest that structured, culturally informed training can enhance empathy, although certainty is low due to heterogeneity and small sample sizes.
The modest effect observed by Lewis et al is consistent with prior work showing limited gains from single-session interventions. Reference Lewis, Myhra, Hartwell and Smith17 Meta-analytic evidence by Teding Van Berkhout and Malouff Reference Teding Van Berkhout and Malouff21 found a pooled moderate effect (Hedges’ g = 0.61); and Riess et al, Reference Riess, Kelley, Bailey, Dunn and Phillips22 for example, reported a larger improvement following an 8 h empathy course. Compared with these, Lewis et al’s effect (η² = 0.041) suggests that brief, single-exposure workshops may not allow sufficient depth for sustained empathy growth. Reference Lewis, Myhra, Hartwell and Smith17 Multi-session or experiential models, such as Rodríguez-González’s 4-day externship, appear more effective, probably due to repeated opportunities for reflection and interpersonal practice. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18
McDonald et al’s cross-cultural competence training provides further insight. Reference McDonald, Dahlin and Bäärnhielm19 Although quantitative change was not detected, qualitative data revealed perceived gains in empathy and professional role awareness. This aligns with Lamothe et al, who found that most empathy interventions showed qualitative improvements even when standardised scales failed to capture change. Reference Lamothe, Boujut, Zenasni and Sultan23 Such discrepancies may arise because empathy is contextually and culturally embedded; existing measures may not be sensitive to these nuances. As demonstrated in a meta-analysis by Hall et al, culturally adapted health interventions tend to produce stronger effects (g = 0.47 v. 0.15). Reference Hall, Ibaraki, Huang, Marti and Stice24 McDonald et al’s findings support this view, that cultural adaptation appears to enhance provider empathy and role clarity even when numerical scales underrepresent the effect. Reference McDonald, Dahlin and Bäärnhielm19
These findings emphasise that evaluating empathy and compassion in culturally diverse contexts may require mixed-methods designs; Reference Kariyawasam, Ononaiye, Irons and Kirby25–Reference Portz and Burns27 relying solely on self-report scales can underestimate meaningful attitudinal or relational growth. Reference Sunahara, Rosenfield, Alvi, Wallmark, Lee and Fulford28–Reference Jiang, Wang, Mei, Zhao, Lin and Zhang30 Culturally sensitive evaluation tools are essential to capture change accurately, particularly when working across linguistic and cultural boundaries. Reference Serrada-Tejeda, Sánchez-Herrera-Baeza, Rodríguez-Pérez, Máximo-Bocanegra, Martínez-Piédrola and Trugeda-Pedrajo31,Reference Sharma and Jensen32
Pollio et al further illustrated this point. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 Their trauma-focused CBT programme for Ukrainian therapists produced significant gains in coping skills and self-reported empathy, along with reductions in burnout and secondary traumatic stress, although the latter were not statistically significant. Qualitative feedback indicated enhanced collegial trust and professional confidence, markers of improved relational capacity. These findings echo prior research suggesting that compassion-based or empathy-focused interventions can strengthen well-being and professional connectedness. Reference Lamothe, Boujut, Zenasni and Sultan23,Reference Deblinger, Pollio, Cooper and Steer33 The small sample and brief duration may explain the non-significant quantitative outcomes; larger studies with extended follow-up may reveal more robust effects.
Duration and intensity appear critical. Pollio et al’s 8-session course showed benefits for coping and empathy, and Rodríguez-González et al’s 4-day externship yielded the strongest results, with substantial proportions of variance in empathy growth explained (pseudo-R 2 = 22–38%). Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18,Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 This suggests that immersive, experiential and culturally grounded models may be most effective. The significant and sustained increases in empathy and self-compassion observed by Rodríguez-González et al mirror Jazaieri et al, who found moderate effect sizes (Cohen’s d ≈ 0.45) for compassion cultivation training among healthcare workers. Reference Jazaieri, Jinpa, McGonigal, Rosenberg, Finkelstein and Simon-Thomas34 Such parallels indicate that empathy and self-compassion are mutually reinforcing; enhancing one may promote the other and buffer against burnout.
Despite these encouraging findings, kindness and compassion were notably absent as direct outcome measures. This reflects a wider literature gap: although empathy is routinely assessed, kindness and compassion are often implied but unmeasured. Reference Vieten, Rubanovich, Khatib, Sprengel, Tanega and Polizzi35–Reference Sinclair, Kondejewski, Hack, Boss and MacInnis37 Future studies could integrate validated measures such as the Santa Clara Brief Compassion Scale or Compassion for Others Scale to capture these constructs explicitly. Reference Plante and Mejia38–Reference Pommier, Neff and Tóth-Király40 Doing so would enable a fuller understanding of how interventions influence both emotional understanding and compassionate action.
The concept of intelligent kindness provides a useful framework for interpreting these findings. Reference Ballatt and Campling7 It extends beyond empathy to emphasise the deliberate, context-sensitive application of kindness in professional interactions, transforming empathic awareness into constructive, prosocial behaviour. Reference Ballatt and Campling7 Intelligent kindness involves awareness, ethical intent and responsive action aimed at reducing suffering and promoting well-being. In clinical settings it manifests through micro-affirmations, collaborative safety planning and culturally grounded communication that fosters trust and dignity. Reference Ballatt and Campling7,Reference Martinez-Torres, Boorom, Nogueira Peredo, Camarata and Lense41,Reference Rowe42
Although none of the reviewed interventions explicitly targeted intelligent kindness, several incorporated its principles implicitly. Lewis et al’s decolonising workshop invited participants to reflect on historical trauma and unconscious bias, an act of culturally intelligent awareness. Reference Lewis, Myhra, Hartwell and Smith17 McDonald et al’s cross-cultural course promoted perspective-taking across refugee and provider experiences, Reference McDonald, Dahlin and Bäärnhielm19 whereas Pollio et al’s programme fostered solidarity and mutual support among clinicians during wartime stress. Reference Pollio, Deblinger, Cooper, Garbade, Harrison and Pfeiffer20 Rodríguez-González et al’s experiential training emphasised attunement and emotional presence, foundational to compassionate practice. Reference Rodríguez-González, Schweer-Collins, Greenman, Lafontaine, Fatás and Sandberg18 These interventions collectively illustrate the practical relevance of intelligent kindness, even when unnamed.
Strengths and limitations
This review is, to our knowledge, the first to synthesise culturally informed interventions targeting empathy, kindness and compassion among mental health professionals. It included studies from diverse contexts, a pooled sample of 715 participants and applied systematic methods with validated frameworks, enhancing credibility.
However, only four heterogeneous studies were included, limiting generalisability and precluding meta-analysis. Kindness and compassion were not directly measured, leaving a key evidence gap. Demographic reporting was inconsistent, intervention fidelity was not systematically assessed and the rapid review design involved methodological shortcuts, including a two-database, English-language search, single-reviewer screening and no formal risk-of-bias assessment.
Overall, the review provides valuable insights into culturally informed empathy training while highlighting the need for larger, rigorous studies that directly evaluate kindness and compassion.
Future directions
Future research should assess not only empathy but also kindness and compassion using culturally validated, mixed-methods approaches. Core instruments could include the Sussex–Oxford Compassion for Others and Santa Clara Brief Compassion Scale for compassion, the Jefferson Scale of Empathy and Questionnaire of Cognitive and Affective Empathy for clinician empathy and patient-rated tools such as the CARE Measure and Working Alliance Inventory. Importantly, because most existing scales were developed in Western contexts, cross-cultural validation is essential to ensure accurate measurement across diverse populations. Longitudinal studies with multi-session interventions are needed to determine the durability of effects and optimal training dose. Outcome assessment should extend to professional well-being, burnout, collegial trust, therapeutic alliance and patient satisfaction.
Implementation research is also critical. Future studies should clarify who delivers training (clinicians, peers, community facilitators), whether follow-up or booster sessions are needed and how fidelity is monitored. Evaluations should consider scalability, cost-effectiveness and integration of culturally adapted training into routine practice across diverse settings, including in-patient, community and low- and middle-income contexts.
Clinical and policy implications
This study showcases the vital role of incorporating culturally informed practices in virtue-based interventions for mental health professionals with limited but promising outcomes across the literature. It underscores the need for more rigorous, larger-scale studies that include direct measures of intelligent kindness, empathy and compassion to prevent burnout and promote inclusive health policy advancements.
From a systems perspective, embedding intelligent kindness within professional development could enhance both clinician well-being and patient care. Compassionate, culturally informed communication strengthens therapeutic alliance, promotes equity and mitigates burnout. To achieve this, training programmes should integrate cultural humility, reflective practice and compassion-focused exercises within ongoing supervision and team development structures. Mixed-methods evaluation frameworks are recommended to capture both attitudinal shifts and behaviourally observable expressions of kindness in care.
In summary, culturally informed empathy training appears to foster meaningful professional growth among mental health providers, although current evidence is limited and heterogeneous. Empathy gains were evident across diverse contexts, but kindness and compassion remain underexplored. Integrating the principles of intelligent kindness and intentional, culturally grounded, action-oriented compassion offers a promising next step for research and clinical training. Future studies should include validated compassion measures, assess long-term outcomes and examine how culturally adaptive, kindness-based approaches can sustain professional well-being and enhance equitable mental healthcare globally.
About the authors
Dr Faisal A. Nawaz, MBBS, is a final-year psychiatry resident doctor and researcher at Al Amal Psychiatric Hospital in Dubai, UAE. Dr Nawaz has a special interest in cultural psychiatry, global mental health, digital health and medical education with over 70 publications in the field. Dr Nawaz is also the President of the Emirates Precision Psychiatry Special Interest Group, UAE, and co-founder of the Global Remote Research Scholars Program, USA. Firdous M. Usman, BSN, RN, OCN, is an oncology nurse at American Hospital Dubai, UAE. She holds a Bachelor of Science in Nursing from RAK Medical and Health Sciences University and completed the Medical Education and Innovation Fellowship Programme at Medics Academy, UK. She is currently pursuing a Master of Science in Health Professions Education. Her research interests include oncology nursing, medical education, simulation-based learning, digital health, and healthcare quality improvement. She has authored and co-authored several peer-reviewed publications and has presented her work at international conferences. Dr Syed Ali Bokhari, MBBS, is a specialist psychiatrist in the Mental Health of Older Adults Clinical Academic Group at Al Amal Psychiatric Hospital, Emirates Health Services, Dubai, UAE. He holds the Emirati Board of Psychiatry and is completing a Master of Science in Entrepreneurship in Digital Health at the University of Naples Federico II. He serves as Secretary General of the Emirates Precision Psychiatry Special Interest Group, UAE. His academic interests include old age psychiatry, mental health services research, cultural psychiatry and mental health stigma, digital mental health, and precision psychiatry. Rukaiya Usman is a final year psychology student at Manipal Academy of Higher Education, Dubai, UAE. She has a strong interest in child psychology, research and mental health advocacy. Her academic interests include psychological well-being and evidence-based approaches to improving mental healthcare. Dr Waleed Ahmed, FRCPsych, is a consultant psychiatrist and clinical director at Maudsley Health, Abu Dhabi, UAE. His clinical interests include neurodevelopmental conditions across the lifespan, eating disorders and forensic psychiatry. In his current role, he supports the development of compassionate, person-centred mental health services grounded in cultural fluency and humility. Dr Sean Cross, PhD, MRCPsych, is a consultant psychiatrist at the South London and Maudsley National Health Service (NHS) Foundation Trust, UK, and on the Board of the Trust as Chief Commercial Officer. He leads on a range of Trust based international engagement and is passionate about improving care through doing so. Dr. Nahida Nayaz Ahmed, MD, is a Consultant Psychiatrist and Chief Medical Officer of SAKINA, Abu Dhabi, UAE, where she leads one of the country’s largest integrated mental health networks. An American Board-certified psychiatrist with postgraduate training at Harvard Medical School and Tufts University affiliated teaching hospitals, she is faculty at the United Arab Emirates University and at Khalifa University in UAE. Dr Ahmed has led national initiatives in mental health service transformation, across healthcare, education, and community sectors. An invited international speaker, she has presented at leading regional and global conferences on mental health systems, integrated care, innovation, and healthcare leadership. Her research interests include health system transformation, collaborative care, digital psychiatry, and implementation science. Dr Nagina Khan, PhD, SFHEA, PGCert, BHSc, RMN, is a senior clinical research fellow at the Centre for Health Services Studies (CHSS), University of Kent, UK. She is Director of the MSc Applied Health and Care Research (National Institute for Health and Care Research (NIHR) INSIGHT Programme) and Research Inclusion Co-lead for the Applied Research Collaboration Kent, Surrey and Sussex (NIHR ARC KSS). Her research focuses on mental health, health services research, research inclusion, patient and public involvement, and reducing health inequalities through applied health and care research.
Data availability
Data availability is not applicable to this article because no new data were created or analysed in this study.
Acknowledgements
None.
Author contributions
F.A.N. led the conceptualisation, methodology design, writing of the original draft and critical revision of the manuscript. S.A.B. contributed to the conceptualisation, manuscript writing and critical review of the content. F.M.U., R.U., W.A., S.C., N.N.A. and N.K. contributed to the literature review and drafting and editing of the manuscript, as well as providing intellectual input during the revision process. All authors reviewed and approved the final version of the manuscript, and agree to be accountable for all aspects of the work.
Funding
This research received no specific grant from any funding agency, commercial or not-for-profit sectors.
Declaration of interest
None.
Ethical standards
Ethical approval was not required for this article because it is a review of existing literature and does not involve the collection or analysis of primary data from human participants.
Transparency declaration
The lead author and manuscript guarantor affirm that the manuscript is an honest, accurate and transparent account of the study being reported, and that no important aspects of the study have been omitted.



 Open access


eLetters
No eLetters have been published for this article.