


Introduction
The World Health Organization (WHO) has identified loneliness as an important public health concern, especially within the context of population aging (WHO, 2021). Globally, approximately one in four (27.6%) adults aged 60 to 110 experience loneliness (Salari et al., Reference Salari, Najafi, Rasoulpoor, Canbary, Heidarian and Mohammadi2025), i.e., ‘the distressing feeling that accompanies the perception that one’s social needs are not being met by the quantity or especially the quality of one’s social relationships’ (Hawkley & Cacioppo, Reference Hawkley and Cacioppo2010, p. 1). Loneliness can be experienced due to social isolation (i.e., an objective construct based on fewer or less frequent social contacts); however, it is still possible for individuals to feel lonely, even in the presence of others (Hawkley & Cacioppo, Reference Hawkley and Cacioppo2010). Based on the Canadian Longitudinal Study on Aging (CLSA), loneliness is even more common in older women and in adults over 75 years of age (Wister & Menec, Reference Wister, Menec, Raina, Wolfson, Kirkland and Griffith2018) and increased by 20 % during the pandemic (Kadowaki & Wister, Reference Kadowaki and Wister2022). Loneliness has emerged as a key psychosocial risk factor associated with many adverse health outcomes, including cardiovascular disease and diabetes (Valtorta et al., Reference Valtorta, Kanaan, Gilbody, Ronzi and Hanratty2016), neuro-psychological issues, such as cognitive decline, depression, and anxiety (Holt-Lunstad & Perissinotto, Reference Holt-Lunstad and Perissinotto2023), and even premature death (Holt-Lunstad, Reference Holt-Lunstad2022). Understanding the trajectory of loneliness in older adults and any modifiable risk factors of loneliness is therefore important to support healthy aging.
One potential factor that may increase vulnerability to loneliness in later life is changes in hearing ability. Hearing loss is one of the most prevalent chronic conditions among older adults, affecting approximately one in three individuals over the age of 65 years worldwide, with prevalence and severity of hearing loss increasing with age. With nearly 2.5 billion people experiencing some degree of hearing loss by 2050, this chronic condition is globally the fourth highest cause of disability. Longitudinal studies have also identified hearing loss as a potential risk factor for dementia, particularly when combined with other health risks such as physical inactivity (Livingston et al., Reference Livingston, Huntley, Liu, Costafreda, Selbæk and Alladi2024; Son et al., Reference Son, Speechley, Zou and Montero-Odasso2025). A systematic review by Shukla et al. (Reference Shukla, Harper, Pedersen, Goman, Suen, Price and Reed2020) found that hearing loss is consistently associated with greater loneliness and social isolation in older adults; however, because most studies have been cross-sectional, the directionality of this relationship remains unclear. That is, difficulty hearing may contribute to the experience of loneliness; however, it is also possible that loneliness contributes to future hearing difficulties (e.g., via an elevated stress response and/or cardiovascular disease) or that dynamic, bi-directional associations could exist between hearing and loneliness over time. Considering the prevalence and potential connections between hearing and loneliness, the current project aims to investigate longitudinal associations between hearing and loneliness in Canadians (45–64, 65+), establishing whether the data suggest bi-directionality in the associations or whether unidirectionality is a better explanation for the data. Additionally, we include an exploratory analysis to assess whether longitudinal associations between hearing and loneliness differ between individuals who report hearing device use and those who do not.
The majority of existing research on loneliness and hearing has been cross-sectional, using population-based studies (Bott & Saunders, Reference Bott and Saunders2021). Mick et al. (Reference Mick, Parfyonov, Wittich, Phillips and Pichora-Fuller2018), for example, studied the first wave of the CLSA tracking cohort data and showed that self-reported hearing loss, vision loss, and dual sensory loss were independently associated with loneliness and reduced availability of social support. Additional CLSA analyses have shown behavioural measures of hearing loss and vision loss positively associated with loneliness (Hämäläinen et al., Reference Hämäläinen, Phillips, Wittich, Pichora-Fuller and Mick2019), but that when sensory impairment was assessed by self-report and was controlled by the degree of behavioural loss, the associations with loneliness and other social factors were no longer significant (Hämäläinen et al., Reference Hämäläinen, Pichora-Fuller, Wittich, Phillips and Mick2021).
Beyond the CLSA, several studies have reported associations between hearing loss and loneliness in older adults (e.g., Döge et al., Reference Döge, Hackenberg, Beutel, Otten, Wild, Chalabi, Ghaemi Kerahrodi, Münzel, Lackner and Schmidtmann2025; Huang et al., Reference Huang, Reed, Deal, Arnold, Burgard and Chisolm2024; Kramer et al., Reference Kramer, Kapteyn, Kuik and Deeg2002). Döge et al. (Reference Döge, Hackenberg, Beutel, Otten, Wild, Chalabi, Ghaemi Kerahrodi, Münzel, Lackner and Schmidtmann2025) found that severe, profound, or complete hearing loss, as measured by pure-tone audiometry, significantly increased the risk for loneliness in a cross-sectional sample from the Gutenberg Health Study in Germany. Evaluating baseline data from the Longitudinal Aging Study Amsterdam, Kramer et al. (Reference Kramer, Kapteyn, Kuik and Deeg2002) found that older adults with greater self-reported hearing loss had elevated loneliness, even after controlling for the burden of chronic disease. Additionally, with baseline data from the United States based on the Aging and Cognitive Evaluation in Elders (ACHIEVE) trial, Huang et al. (Reference Huang, Reed, Deal, Arnold, Burgard and Chisolm2024) found that self-reported hearing loss was associated with greater loneliness and smaller social networks, behavioural hearing loss was associated with greater loneliness, and speech perception in noise ability was associated with smaller social networks.
Evidence from studies on hearing care interventions supports a directional pathway in which hearing loss contributes to subsequent loneliness in older adults. For example, the ACHIEVE trial showed that a hearing intervention (hearing aids, counselling, and personalized instruction with an audiologist) resulted in significantly less social isolation and loneliness over three years compared to a control group (Reed et al., Reference Reed, Chen, Huang, Pike, Arnold and Burgard2025). Participants who received the hearing intervention also retained on average one additional social connection over three years compared to controls and reported more diverse and high-quality social networks overall (Reed et al., Reference Reed, Chen, Huang, Pike, Arnold and Burgard2025). Improvements in loneliness have been identified after four to six weeks of hearing aid use (Weinstein et al., Reference Weinstein, Sirow and Moser2016) and after an auditory rehabilitation and exercise program (Jones et al., Reference Jones, Siever, Knuff, Van Bergen, Mick, Little and Miller2019). A 5-year longitudinal study also showed that when individuals received hearing aids or cochlear implants, loneliness stayed stable and did not increase (Applebaum et al., Reference Applebaum, Hoyer, Betz, Lin and Goman2019). Together, these findings suggest that hearing rehabilitation may alter downstream psychosocial consequences of hearing loss. However, it remains unclear whether similar patterns are observable in population-based longitudinal data, particularly when comparing individuals who do and do not use hearing devices.
Longitudinal evidence suggests that the association between hearing loss and loneliness is neither uniform across older adults nor independent of contextual factors such as hearing aid use, age, and sex. Using data from the Longitudinal Aging Study Amsterdam, Pronk et al. (Reference Pronk, Deeg, Smits, van Tilburg, Kuik, Festen and Kramer2011) demonstrated that baseline self-reported hearing loss and longitudinal declines in hearing were associated with subsequent increases in loneliness only within specific sub-groups. In particular, poorer hearing predicted greater loneliness over four to seven years among individuals who did not use hearing aids and among men, whereas these associations were not observed in hearing aid users or women. Moreover, Pronk et al. (Reference Pronk, Deeg, Smits, Twisk, van Tilburg, Festen and Kramer2014) showed that a faster rate of decline in speech-in-noise performance was associated with increasing loneliness primarily among individuals with moderate hearing loss at baseline and among those experiencing major social transitions, such as partner loss, underscoring the importance of heterogeneity in longitudinal pathways. More recent large-scale longitudinal studies also support sub-group-specific effects. Analyses from the Survey of Health, Ageing and Retirement in Europe showed that poorer self-reported hearing predicted higher loneliness two years later, with older age and female sex independently associated with greater loneliness, although hearing aid use did not moderate this association at the population level (Wagner et al., Reference Wagner, Schonenberg and Prell2025). Similarly, findings from the Jansen et al. (Reference Jansen, van Wier, Lissenberg-Witte, Smits and Kramer2025) provide nuanced longitudinal evidence on loneliness outcomes in relation to hearing aid uptake. While hearing aid use was not associated with reductions in loneliness in the overall sample, uptake was linked to lower total loneliness among adults older than 65 years.
Although the direction of the relationship between hearing and loneliness has most often been presented as loneliness as an outcome of prior hearing loss, an additional longitudinal study from the UK Biobank (Song et al., Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025) suggests that the opposite directionality may also be supported. That is, Song et al. (Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025) identified that compared to non-lonely participants, lonely individuals exhibited an increased risk of later hearing loss [median follow-up, 12.3 years; hazard ratio (HR), 1.36; 95% confidence interval (CI), 1.30 to 1.43]. In this study, hearing loss was measured by reviewing hospital in-patient records and identifying relevant International Classification of Diseases 10th Revision (ICD-10) diagnostic codes (a standardized system used internationally to classify medical diagnoses; codes H90–H91 for hearing loss). Stephan et al. (Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026) provided further evidence of a loneliness-to-hearing loss pathway using two large population-based cohorts from the United States and England and using a pure-tone audiometry measure of hearing loss. In this study, higher baseline loneliness was prospectively associated with poorer behaviourally measured hearing (i.e., pure-tone audiometry) and increased risk of hearing impairment at follow-up across both data samples. These associations persisted after adjustment for cardiometabolic conditions (hypertension, diabetes), smoking, depressive symptoms, and social isolation. Together, these findings challenge the conventional view that loneliness is only a consequence of hearing loss and instead support the possibility of longitudinal pathways in which loneliness may also contribute to auditory functioning.
There are several possible interacting mechanisms underlying this alternate pathway. For example, loneliness has been identified as a chronic stressor, elevating hypothalamic-pituitary-adrenal (HPA) axis activity, sympathetic arousal, and low-grade systemic inflammation (Hawkley & Cacioppo, Reference Hawkley and Cacioppo2010). This inflammatory response could lead to age-related cochlear degeneration, providing a plausible biological route to hearing loss (Kociszewska & Vlajkovic, Reference Kociszewska and Vlajkovic2022). Loneliness also increases the risk of cardiometabolic diseases such as cardiovascular disease and type 2 diabetes (Holt-Lunstad & Perissinotto, Reference Holt-Lunstad and Perissinotto2023). These conditions damage microvascular and metabolic pathways essential for auditory function and are established risk factors for age-related hearing loss (Mick et al., Reference Mick, Kabir, Pichora-Fuller, Jones, Moxham, Phillips and Wittich2023). Additionally, loneliness has been associated with unhealthy behaviours, such as increased levels of smoking, physical inactivity, poor diet, and worse sleep, which elevate metabolic and vascular risk (Shankar et al., Reference Shankar, McMunn, Banks and Steptoe2011). Many of these behaviours are recognized contributors to cardiometabolic diseases and age-related hearing loss.
Considering existing research, there is a need to investigate potential bi-directional associations between hearing and loneliness and to evaluate these associations based on sub-groups, such as age and sex. The current study addresses this gap by conducting a longitudinal analysis. This study will test whether the associations between hearing and loneliness operate bi-directionally over time or are more consistent with a unidirectional pathway. As a secondary analysis, we will also examine whether longitudinal associations between hearing and loneliness differ between individuals who report hearing device use at Baseline and those who do not.
Methods
The analysis was conducted on data from the comprehensive cohort of the CLSA using Baseline (2015), Follow-Up 1 (FU1), and FU2 data, stratified by age group (45–64, 65+ years) and sex (male, female). With data collected every three years, CLSA includes a tracking cohort (computer-assisted telephone interviews only) and a comprehensive cohort (both interviews and in-person data collection completed). Persons excluded from CLSA cohorts included those living in institutions at baseline, full-time members of the Canadian Armed Forces, persons living on federal First Nations reserves and other First Nations settlements, the three northern territories and some remote regions, those unable to respond in English or French, and those with cognitive impairment at baseline (i.e., the inability to understand the study consent discussion, as determined by a recruiter). The current study analysed data from the comprehensive cohort at Baseline (N = 30,097), FU1 (N = 27, 765), and FU2 (N = 25, 493; Raina et al., Reference Raina, Wolfson, Kirkland, Griffith, Balion, Cossette and Young2019; Raina et al., Reference Raina, Wolfson, Kirkland, Griffith, Oremus, Patterson and Brazil2009). Ethics board approval was acquired from Simon Fraser University (approval number 30002332). CLSA data access approval was also acquired (approval number 2401011).
Measures
Self-reported residual hearing
Self-reported residual hearing was determined using the following multiple-choice item: Is your hearing, using a hearing device if you use one…excellent, very good, good, fair, or poor. The current manuscript focuses on self-reported residual hearing because these data were collected consistently across all three study waves (Baseline, FU1, and FU2). In contrast, a substantial proportion of audiometric data are missing at FU2 due to in-person testing restrictions during the coronavirus 2019 (COVID-19) pandemic, limiting the feasibility of longitudinal analyses using audiometry. Accordingly, results based on audiometric hearing thresholds are presented in the Supplementary Material, while the primary analyses in this manuscript focus on self-reported residual hearing.
Hearing device use was measured using the following item: ‘Do you use an aid, specialized equipment, or services for persons who are deaf or hard of hearing, for example, a volume control telephone or TV decoder?’ (Yes/No). That is, the use of hearing aids, cochlear implants, and other devices was captured as part of this question.
Loneliness
Loneliness was measured using one item from the Centre for Epidemiological Studies Short Depression Scale (CES-D-10): ‘In the past week, how often did you feel lonely?’ with response options ‘rarely or never’ (<1 day), ‘some of the time’ (1 to 2 days), ‘occasionally’ (3 to 4 days), or ‘all of the time’ (5 to 7 days).
Covariates
Primary covariates included self-reported annual household income (<$20,000, $20,000 to $49,999, $50,000 to $99,999, $100,000 to $149,999, ≥$150,000), education level (some secondary, secondary graduate, some post-secondary, post-secondary graduate), and cultural background (White or non-White). A secondary group of covariates captured cardiovascular health factors, including smoking, heart disease, high blood pressure, heart attack, angina, diabetes, stroke, ministroke, or transient ischemic attack.
Statistical analysis
All data manipulation and statistical analyses were conducted in R version 4.3.3. Using the lavaan package version 0.6–19, cross-lagged path models (CLPMs) were fitted to estimate associations between hearing loss and loneliness over three timepoints (Baseline, FU1, and FU2). As suggested by Orth et al. (Reference Orth, Clark, Donnellan and Robins2021), autoregressive (i.e., the association within a measure over two adjacent timepoints) and cross-lagged (i.e., associations between measures over two adjacent timepoints) paths were constrained to be equal over time. CLPMs were selected to examine the temporal ordering of associations between self-reported residual hearing and loneliness while accounting for prior levels of each construct. This approach enables estimation of directional (cross-lagged) effects over time, while simultaneously modelling within-construct stability (autoregressive paths). We used a traditional CLPM framework because the primary objective was to examine population-level longitudinal associations across study waves, rather than explicitly separate within-person and between-person variance, as in random-intercept CLPM approaches.
A multi-group approach was used in order to estimate distinct parameter values for each combination of baseline age (45–64 years, 65+ years) and sex (male, female). This approach allows all parameters (autoregressive and cross-lagged paths) to vary freely across groups, providing a flexible test of whether, and to what degree, longitudinal associations differ by sub-group. This approach was selected for two reasons. First, some previous longitudinal studies have identified age- and sex-specific differences in the associations between hearing and psychosocial outcomes, suggesting that these relationships may not be uniform across populations (e.g., Pronk et al., Reference Pronk, Deeg, Smits, van Tilburg, Kuik, Festen and Kramer2011; Wagner et al., Reference Wagner, Schonenberg and Prell2025). Second, prior analyses using the CLSA data have commonly employed age- and sex-stratified models, supporting consistency with existing work (e.g., Best et al., Reference Best, Gan, Wister and Cosco2021; Hopper et al., Reference Hopper, Grady, Best and Stinchcombe2024).
Baseline income, education, age, and cultural background were included as covariates for each model. To examine potential biological mechanisms linking loneliness to subsequent hearing, we conducted additional sensitivity analyses incorporating cardiovascular-related covariates available in the CLSA (i.e., smoking, heart disease, high blood pressure, heart attack, angina, diabetes, stroke, ministroke, or transient ischemic attack). These variables have been selected to approximate pathways related to vascular and metabolic health, which have been proposed as mechanisms linking loneliness to subsequent hearing decline (e.g., Mick et al., Reference Mick, Kabir, Pichora-Fuller, Jones, Moxham, Phillips and Wittich2023; Song et al., Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025; Stephan et al., Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026). The analyses were intended to assess whether observed longitudinal associations were independent of these health-related factors.
As is typical for longitudinal research, attrition occurred across study waves (Baseline: N = 30,097; FU1: N = 27,765; FU2: N = 25,493). To retain observations and minimize bias due to incomplete data, models were estimated using the maximum-likelihood estimator. This approach allows for participants with incomplete data to be included under the assumption that data are missing at random and therefore does not require listwise deletion. This improves statistical power and reduces potential bias associated with attrition. Good model fit was indicated by comparative fit index (CFI) > 0.95 and root-mean-square error of approximation (RMSEA) <0.05. Standardized estimates and 95% CIs are reported below.
To examine the potential moderating role of hearing device use, an additional set of analyses compared hearing-device users and non-users. These follow-up models were estimated in pooled samples without age–sex stratification, as further stratification would have resulted in small sub-group sizes and unstable parameter estimates.
Results
Participant characteristics
The analytic sample included the comprehensive cohort (n = 30,097). With 51% female and 58% aged 45–64, the sample was primarily White (96%) and most of the sample reported completing some post-secondary education (78%; see Table 1).
Baseline participant characteristics

Table 1. Long description
The table categorizes data into four columns: 45 to 64 male (N = 8,437), 45 to 64 female (N = 9,014), 65 plus male (N = 6,340), and 65 plus female (N = 6,306).
* Age: Mean ages are approximately 55.7 for the younger male group, 55.5 for younger females, and 73.1 for both older groups.
* Ethnicity, White: High representation across all groups, ranging from 94.4 percent in younger males to 97.2 percent in older females.
* Education: The majority of participants are post-secondary graduates, though the percentage is higher in the 45 to 64 age groups (82.6 percent for males, 81.4 percent for females) compared to the 65 plus groups (74.9 percent for males, 67.8 percent for females).
* Total annual household income: Younger cohorts show higher income levels, with over 50 percent of 45 to 64 year old males and 40 percent of females earning 100,000 dollars or more. In contrast, the 65 plus groups show higher concentrations in the 20,000 to 99,999 dollar ranges, with older females having the highest percentage (9.1 percent) in the under 20,000 dollar category.
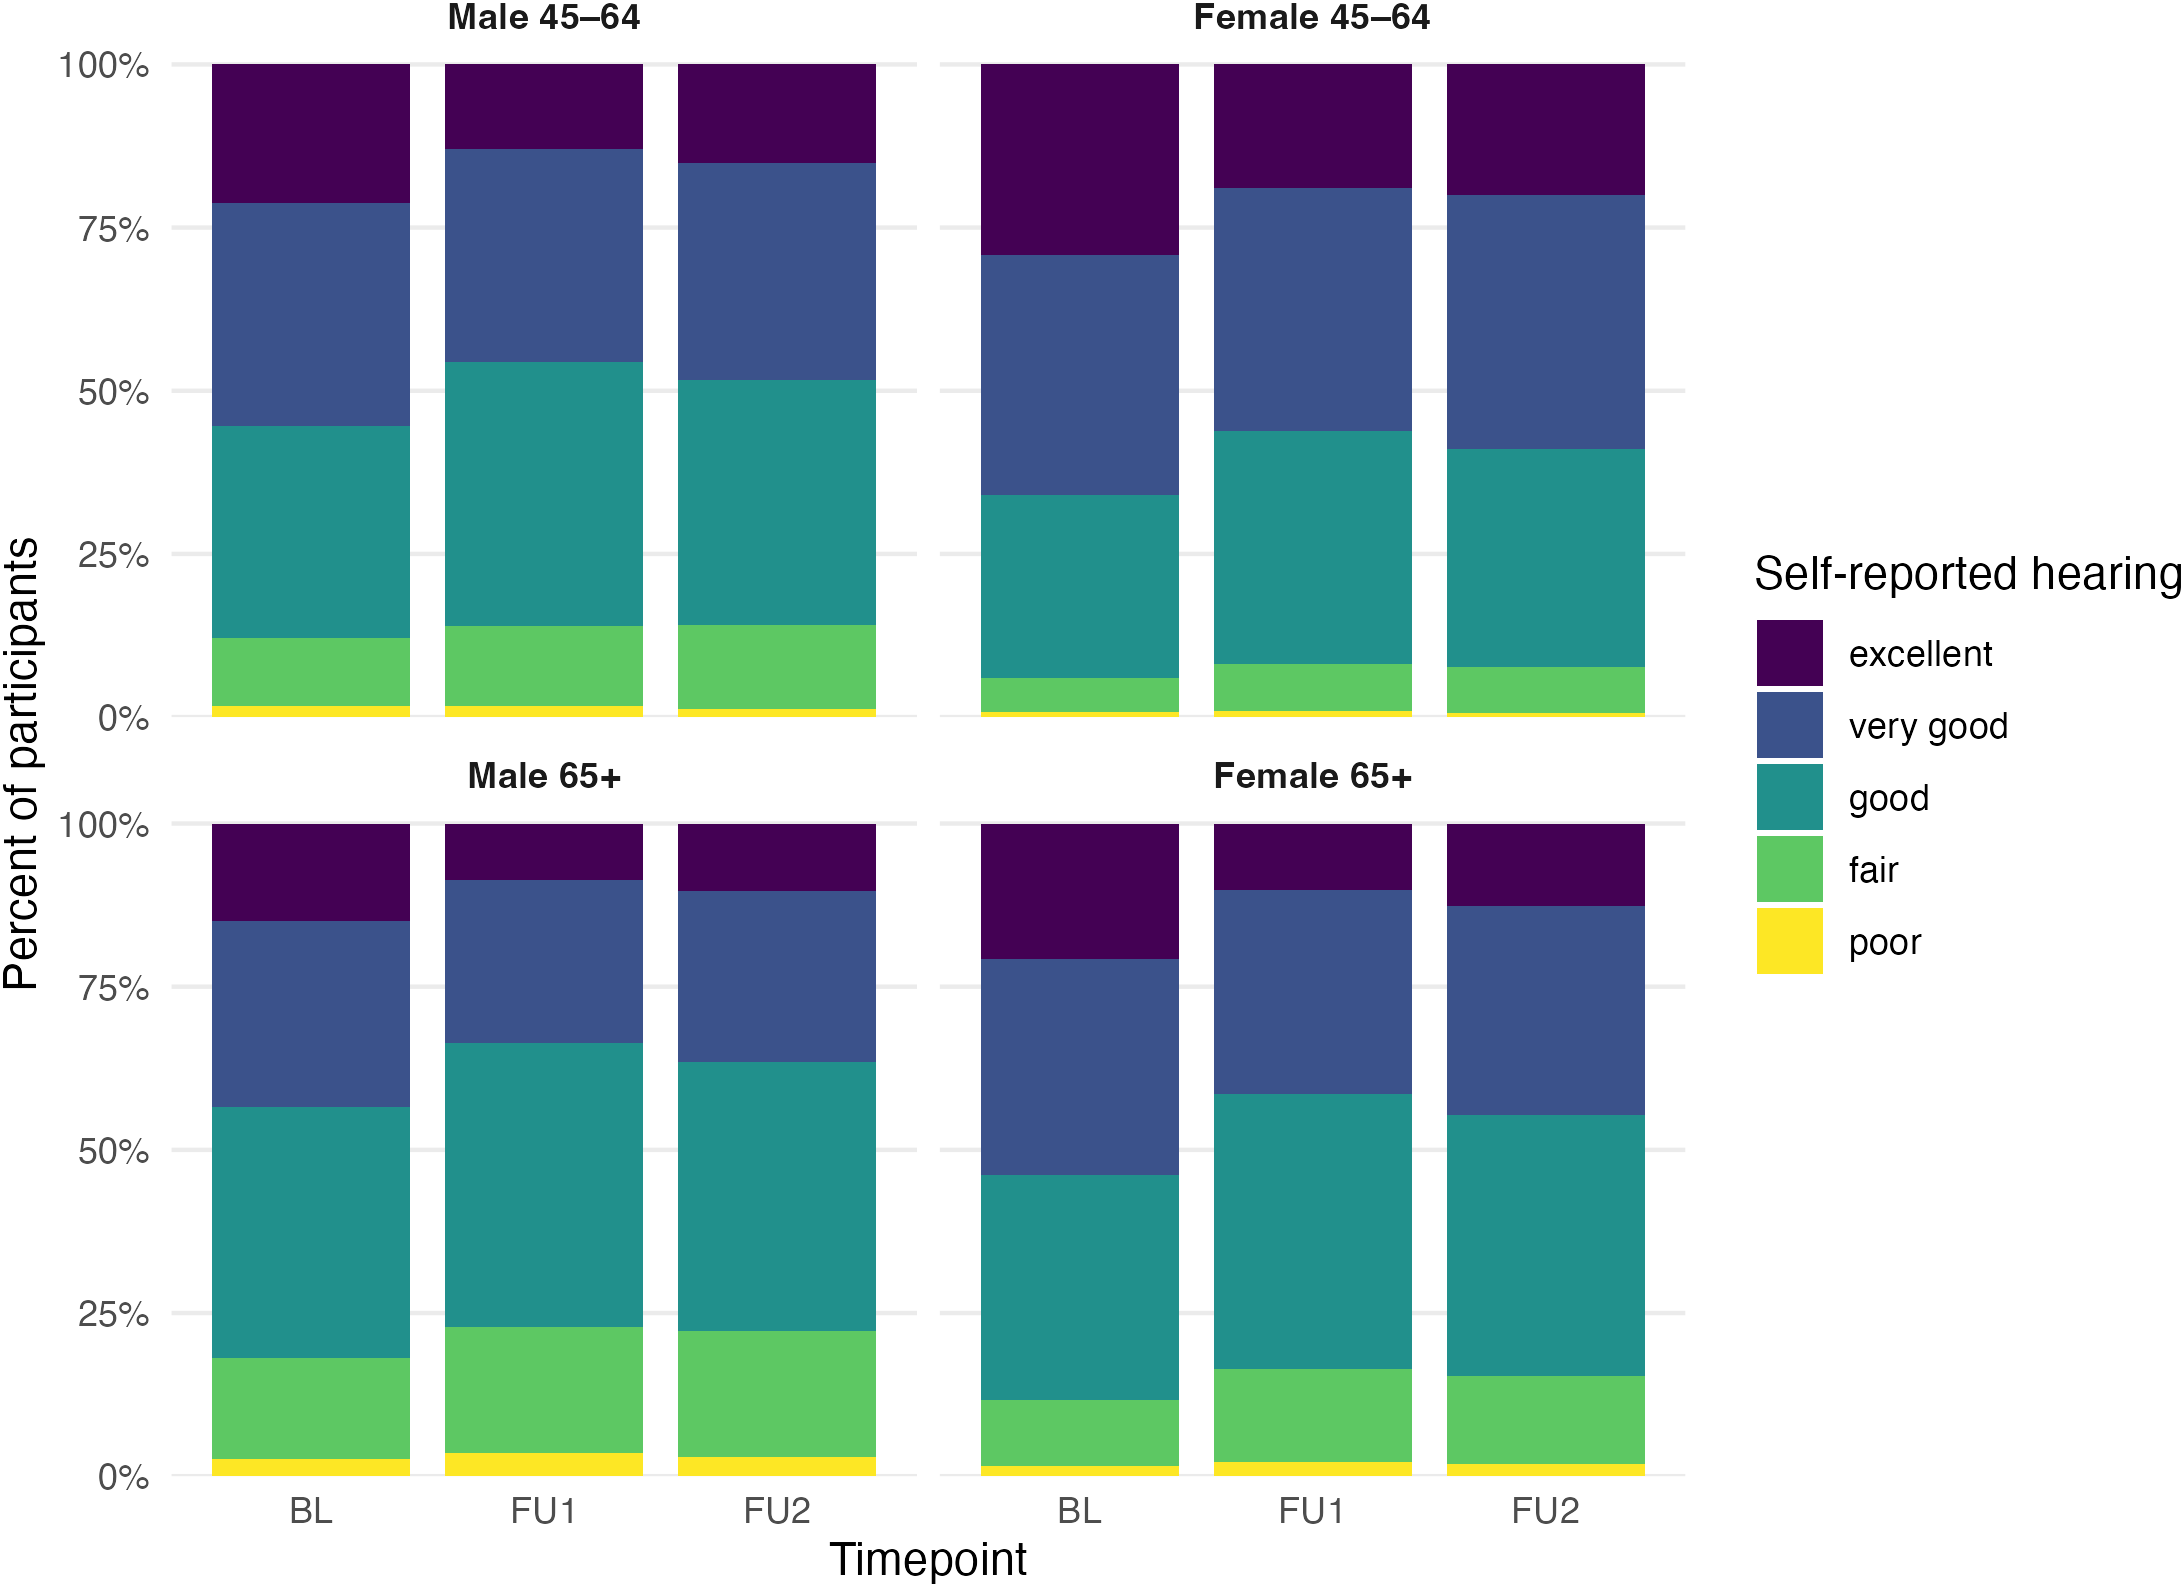
As shown in Figure 1, at baseline, older adults (65+) reported a higher prevalence of fair or poor self-reported residual hearing than adults aged 45–64, with rates of 18.1% among older males and 11.7% among older females, compared with 12.1% among younger males and 5.9% among younger females. Across waves, the proportion reporting fair or poor self-reported residual hearing increased among older males (from 18.1% at baseline to 22.3% at FU2) and older females (from 11.7% to 15.4%), whereas younger males showed a small increase (12.1% to 14.1%) and younger females remained relatively stable over time (5.9% to 7.6%).
Percentage of participants responding excellent, very good, good, fair, or poor to the self-reported hearing item.
Note: Percentages are calculated among participants in each sub-group with non-missing responses at each wave. Missing values for each timepoint are reported in Table 3.

Figure 1. Long description
The chart is divided into four panels: Male 45–64 (top-left), Female 45–64 (top-right), Male 65+ (bottom-left), and Female 65+ (bottom-right). The y-axis represents the Percent of participants from 0% to 100%. The x-axis lists three timepoints: B L, F U 1, and F U 2.
Each bar is stacked with five categories from bottom to top:
• yellow: poor
• light green: fair
• teal: good
• blue: very good
• dark purple: excellent
In the Male 45–64 panel, the ‘good’ and ‘very good’ categories dominate, with ‘excellent’ decreasing slightly from B L to F U 1.
In the Female 45–64 panel, the ‘excellent’ category (dark purple) is notably larger at B L (approx. 30%) compared to F U 1 and F U 2 (approx. 20%).
In the Male 65+ panel, the ‘good’ category (teal) is larger than in the younger cohort, and the ‘poor’ and ‘fair’ categories combined reach nearly 25% at F U 1.
In the Female 65+ panel, the ‘good’ category (teal) expands from B L to F U 2, while the ‘excellent’ category remains smaller than the younger female cohort, staying around 15-20% across timepoints.
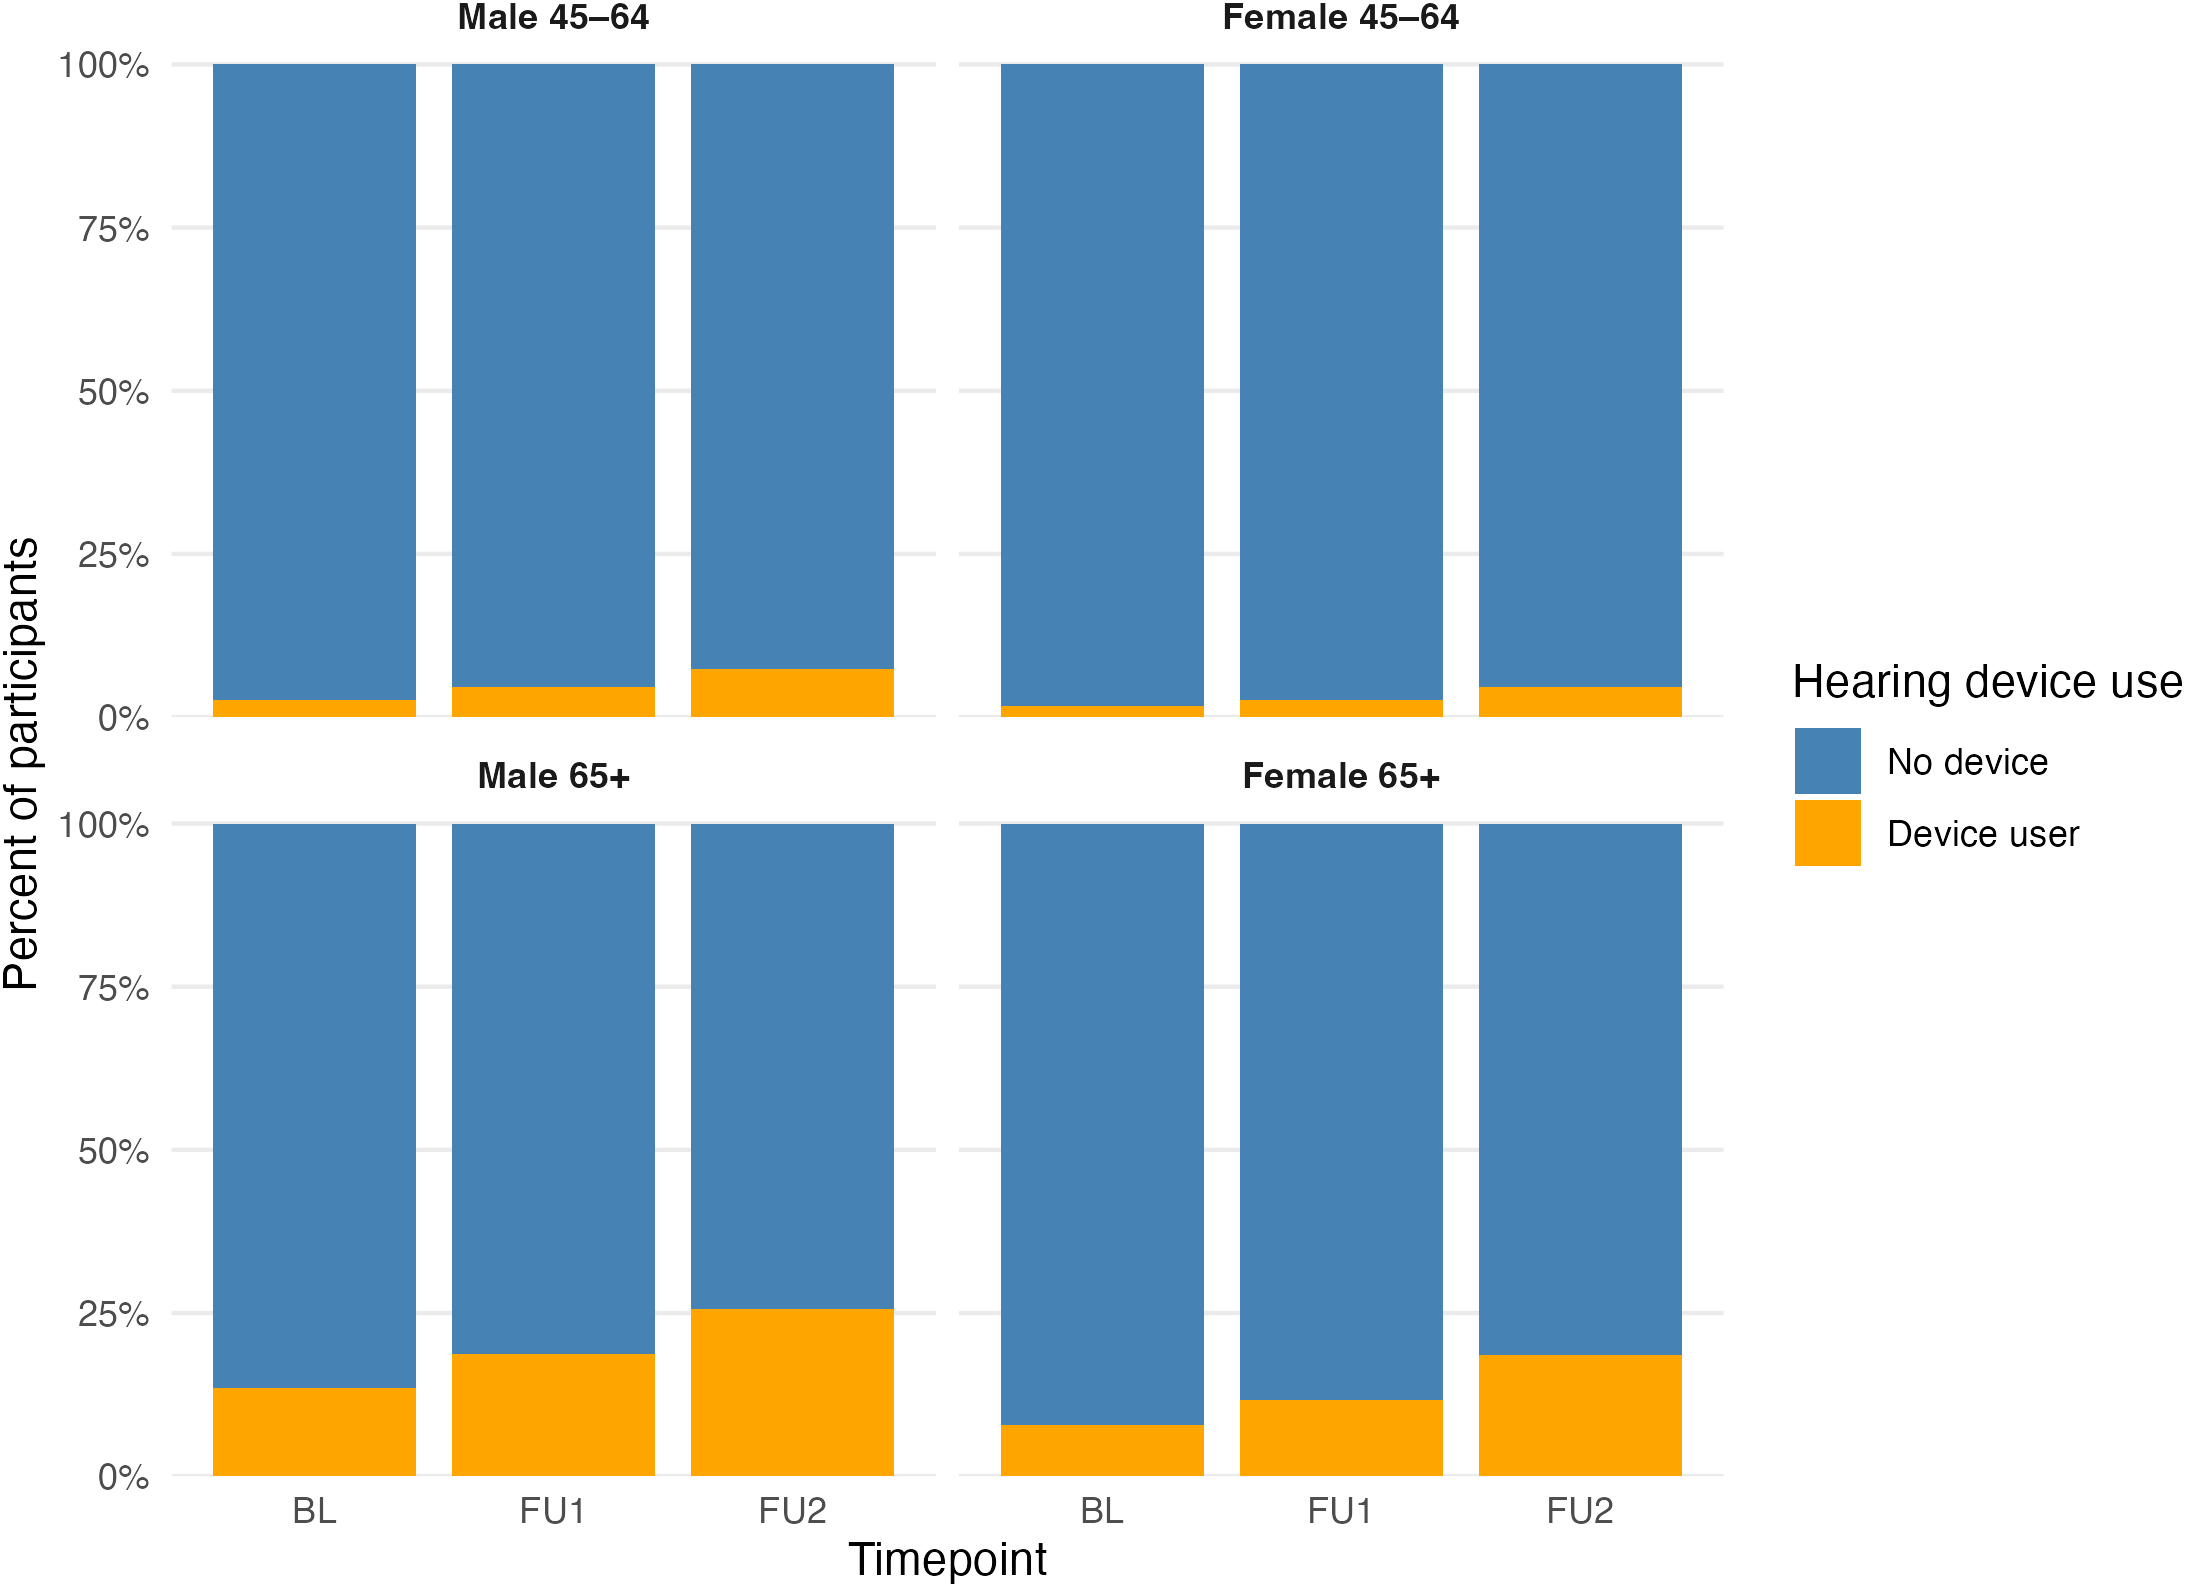
Hearing device use prevalence by age and sex across study timepoints is shown in Figure 2. At baseline, device use was more common among older adults (65+) than among adults aged 45–64, with rates ranging from 13.5% in males 65+ to 1.7% in females 45–64. Across timepoints, device use increased modestly in most sub-groups, with the largest increase observed among males 65+ (from 13.5% at baseline to 25.6% at FU2).
Percentage of participants using hearing aids by age, sex, and timepoint.
Note: Percentages are calculated among participants in each sub-group with non-missing responses at each wave.
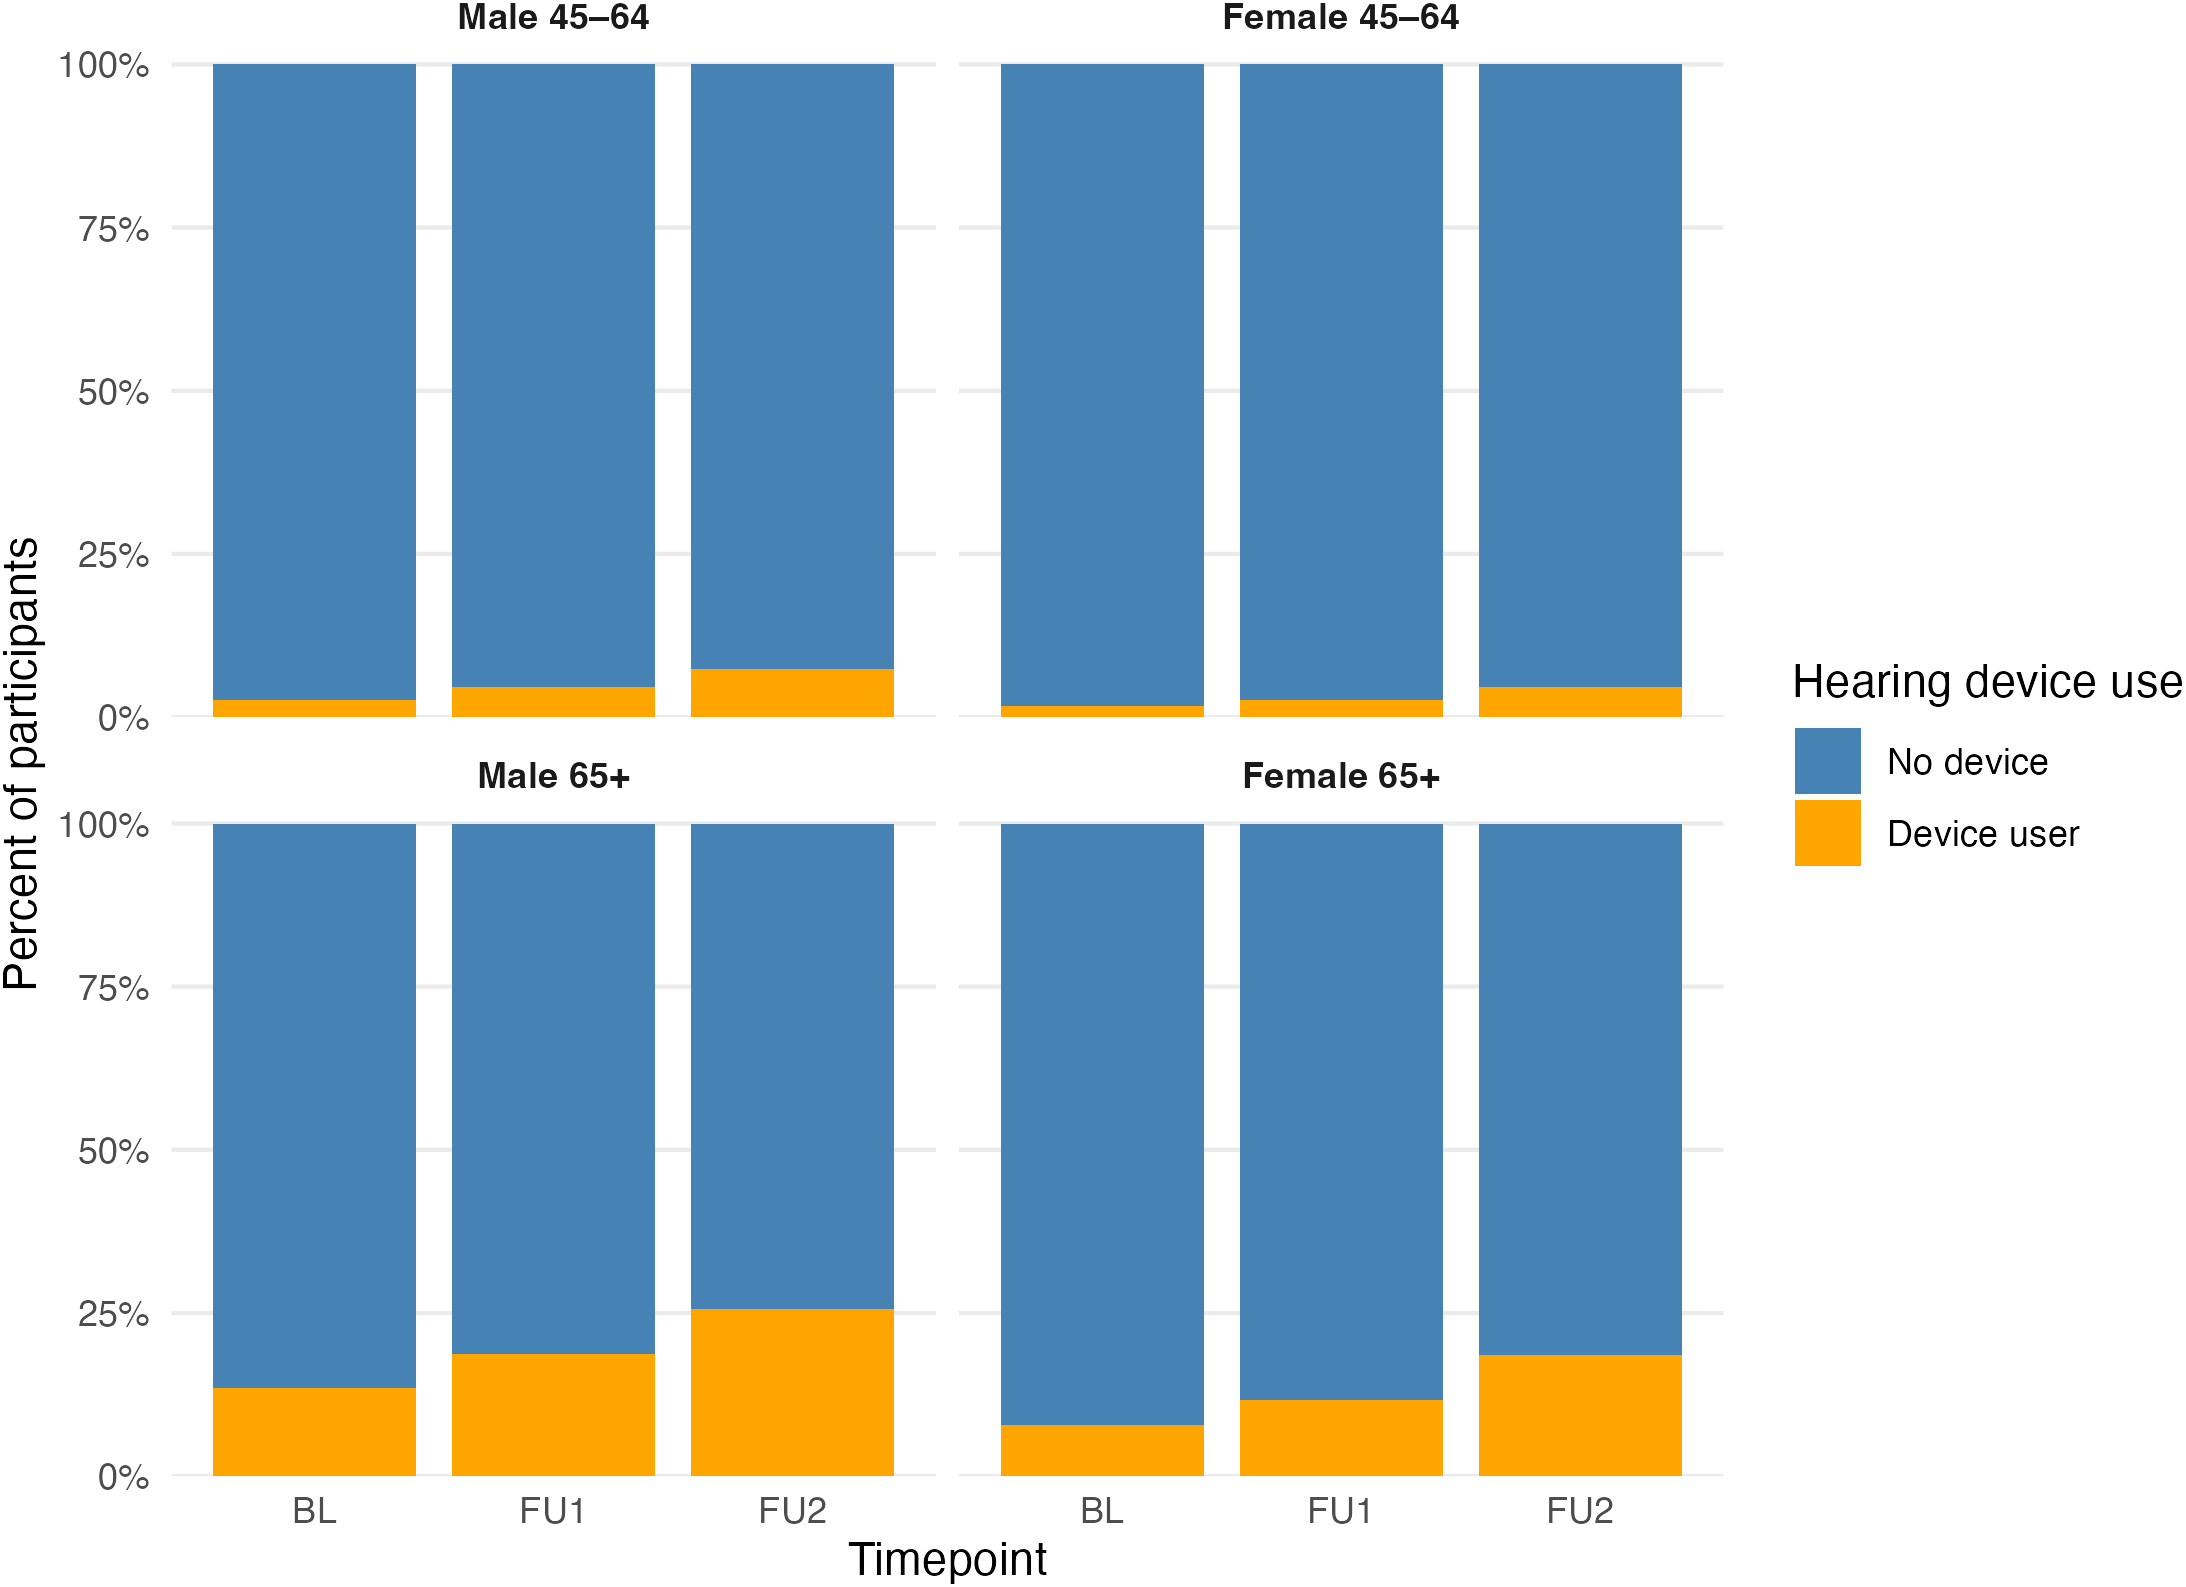
Figure 2. Long description
The chart is divided into four panels based on sex and age. The y-axis represents the Percent of participants from 0 to 100 percent. The x-axis shows three timepoints: B L, F U 1, and F U 2. A legend indicates that orange represents Device user and blue represents No device.
* Top-Left Panel (Male 45 to 64): Device use starts very low at B L and shows a slight linear increase reaching approximately 8 percent at F U 2.
* Top-Right Panel (Female 45 to 64): Device use is the lowest among all groups, starting near 2 percent at B L and rising slightly to about 5 percent at F U 2.
* Bottom-Left Panel (Male 65 plus): This group has the highest usage. Device use starts at approximately 13 percent at B L, increases to nearly 20 percent at F U 1, and reaches roughly 25 percent at F U 2.
* Bottom-Right Panel (Female 65 plus): Device use starts at approximately 8 percent at B L and increases steadily to nearly 20 percent at F U 2.
Across all four panels, there is a consistent trend of increasing hearing device usage over time, with the 65 plus age group showing significantly higher usage than the 45 to 64 group.
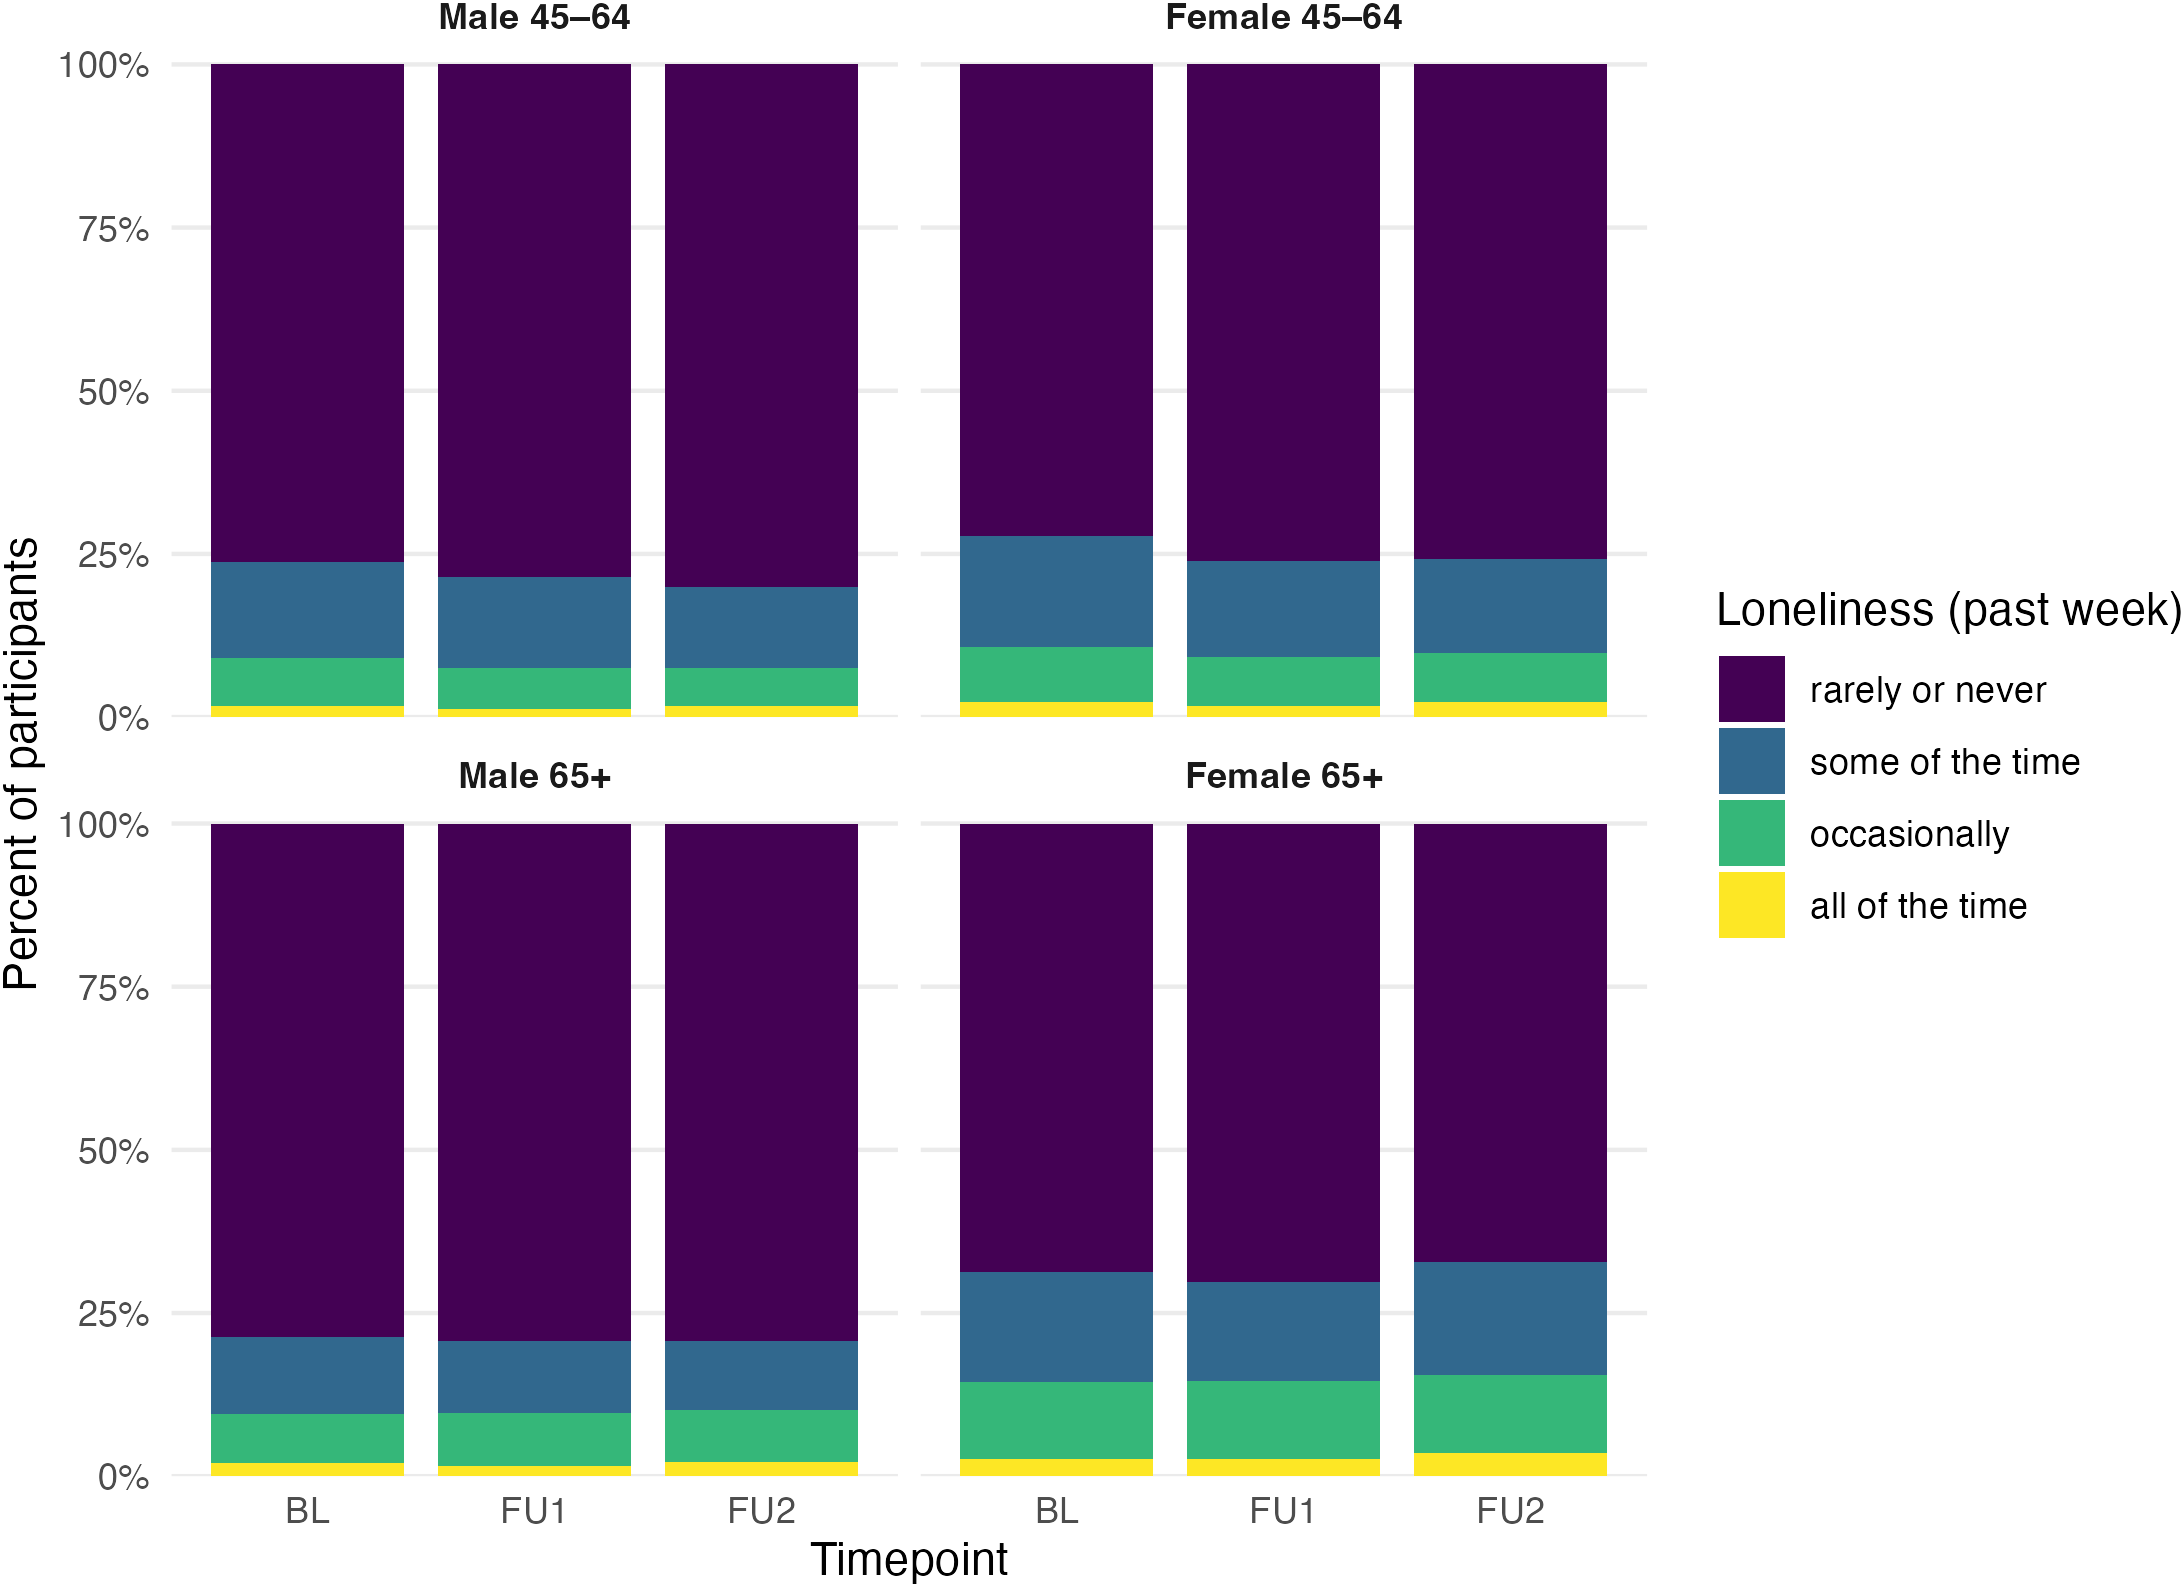
Figure 3 shows the distribution of loneliness frequency across waves by age and sex. At baseline, older females reported the highest loneliness levels, reporting occasionally or all of the time (14.5%), compared with 9.1%–10.8% across the remaining age–sex groups. Across waves, loneliness prevalence remained relatively stable in all sub-groups, with changes from baseline to FU2 of less than 2 percentage points in each group (e.g., older females: 14.5% at baseline and 15.4% at FU2; younger males: 9.1% and 7.6%, respectively).
Percentage of participants responding rarely or never, some of the time, occasionally, or all of the time, to the self-reported loneliness item.
Note: Percentages are calculated among participants in each sub-group with non-missing responses at each wave. Missing values for each timepoint are reported in Table 3. BL = Baseline, FU1 = Follow-Up 1, FU2 = Follow-Up 2.

Figure 3. Long description
A multi-panel figure with four panels arranged in a two-by-two grid. The y-axis for all panels is Percent of participants from 0 percent to 100 percent. The x-axis for all panels is Timepoint with three categories: B L, F U 1, and F U 2.
* Top-Left Panel: Male 45 to 64. The majority of participants, approximately 75 percent, report rarely or never feeling lonely across all timepoints. The remaining 25 percent is split between some of the time, occasionally, and all of the time, with all of the time being the smallest segment at roughly 2 percent.
* Top-Right Panel: Female 45 to 64. Similar to the male group, rarely or never is the largest category at approximately 75 percent. Some of the time accounts for about 15 percent, occasionally for 8 percent, and all of the time for 2 percent.
* Bottom-Left Panel: Male 65 plus. This group shows the highest percentage of rarely or never responses, exceeding 75 percent. The other three categories combined make up less than 25 percent of the total.
* Bottom-Right Panel: Female 65 plus. This group shows a slightly higher prevalence of loneliness compared to the male 65 plus group. Rarely or never accounts for approximately 70 percent, while some of the time and occasionally are slightly larger segments than in the male counterpart.
A legend to the right defines the stacked colors from bottom to top:
* Yellow: all of the time
* Green: occasionally
* Blue: some of the time
* Purple: rarely or never
Cross-lagged path models
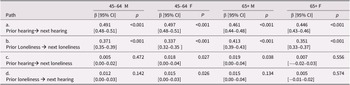
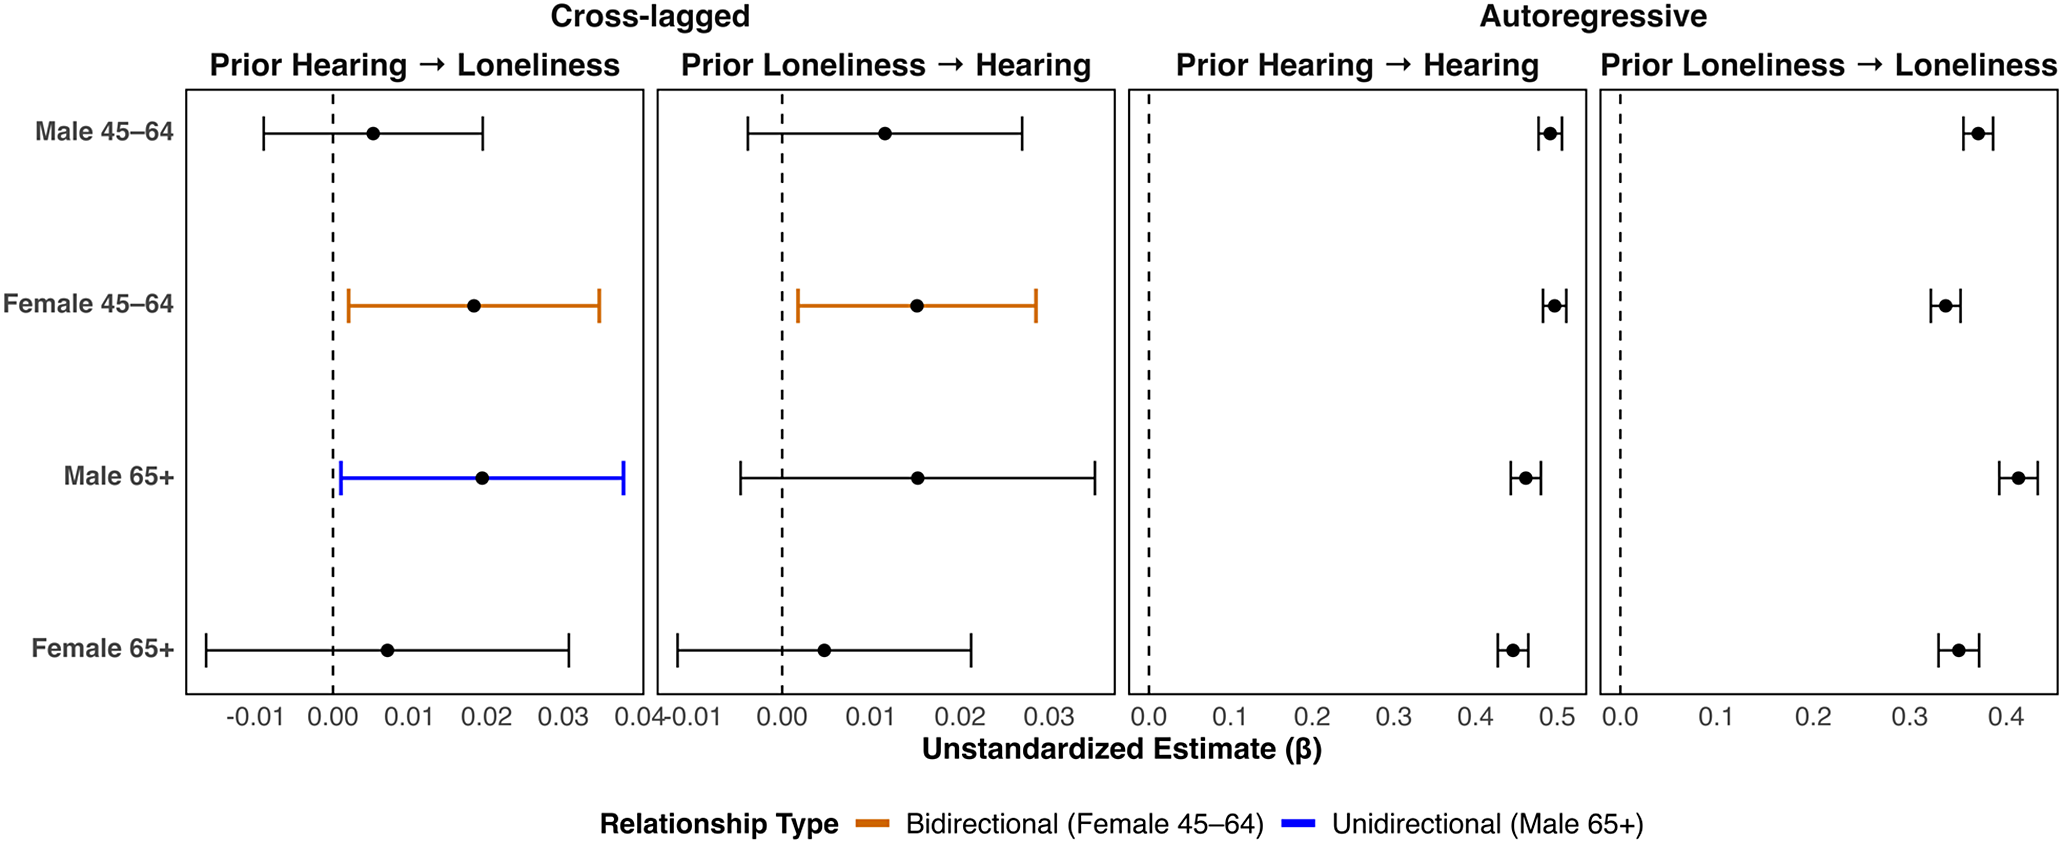
The results of the CLPMs are presented in Table 2 and Figure 4. The model demonstrated appropriate fit to the data: χ2(20) = 315.34, p < .001, CFI = .991, Tucker–Lewis Index = .927, RMSEA = .046 (90% CI [.041, .050]).
Cross-lagged path model results

Table 2. Long description
The table presents beta coefficients, 95 percent C I, and p-values for four paths across four groups: Males 45 to 64, Females 45 to 64, Males 65 plus, and Females 65 plus.
* Path a. Prior hearing to next hearing: Beta values range from 0.446 to 0.497, all with p-values less than 0.001.
* Path b. Prior loneliness to next loneliness: Beta values range from 0.337 to 0.413, all with p-values less than 0.001.
* Path c. Prior hearing to next loneliness: Significant results are found for Females 45 to 64 (beta 0.018, p equals 0.027) and Males 65 plus (beta 0.019, p equals 0.038). Results for Males 45 to 64 and Females 65 plus are non-significant.
* Path d. Prior loneliness to next hearing: A significant result is found only for Females 45 to 64 (beta 0.015, p equals 0.026). All other groups show non-significant p-values ranging from 0.134 to 0.574.
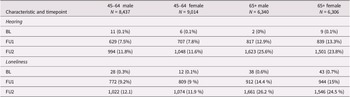
Missing data at each timepoint for hearing and loneliness items
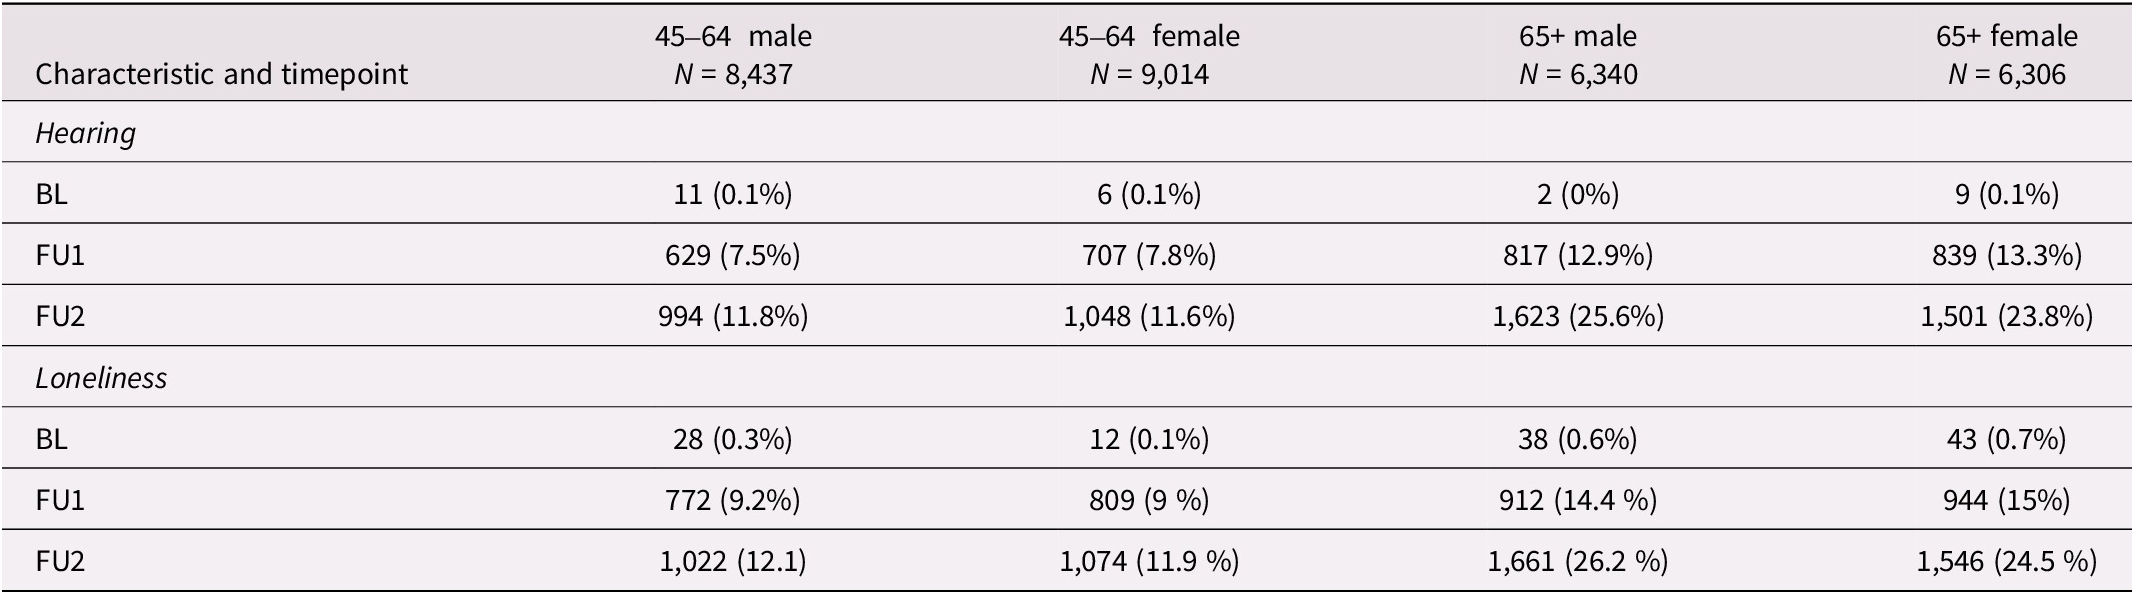
Table 3. Long description
The table consists of five columns. The first column lists the characteristic and timepoint: B L, F U 1, and F U 2. The subsequent four columns represent demographic groups: 45 to 64 male N equals 8,437; 45 to 64 female N equals 9,014; 65 plus male N equals 6,340; and 65 plus female N equals 6,306.
Under the Hearing category:
* B L: 11 0.1 percent; 6 0.1 percent; 2 0 percent; 9 0.1 percent.
* F U 1: 629 7.5 percent; 707 7.8 percent; 817 12.9 percent; 839 13.3 percent.
* F U 2: 994 11.8 percent; 1,048 11.6 percent; 1,623 25.6 percent; 1,501 23.8 percent.
Under the Loneliness category:
* B L: 28 0.3 percent; 12 0.1 percent; 38 0.6 percent; 43 0.7 percent.
* F U 1: 772 9.2 percent; 809 9 percent; 912 14.4 percent; 944 15 percent.
* F U 2: 1,022 12.1 percent; 1,074 11.9 percent; 1,661 26.2 percent; 1,546 24.5 percent.
Abbreviations: B L equals Baseline, F U 1 equals Follow Up 1, F U 2 equals Follow Up 2.
Abbreviations: BL = Baseline, FU1 = Follow Up 1, FU2 = Follow Up 2.
Cross-lagged path model results.

Figure 4. Long description
The multi-panel plot is divided into two main sections: Cross-lagged on the left and Autoregressive on the right. Each section contains two sub-panels. The y-axis on the far left lists four demographic groups: Male 45–64, Female 45–64, Male 65+, and Female 65+. The x-axis represents the Unstandardized Estimate beta.
1. Cross-lagged Section:
- Prior Hearing to Loneliness: All groups show positive estimates between 0.00 and 0.02. The Male 65+ group is highlighted with a blue line, and Female 45–64 with an orange line. Error bars for all groups cross the zero line except for Female 45–64 and Male 65+.
- Prior Loneliness to Hearing: Estimates are positive, ranging from approximately 0.005 to 0.015. Error bars for all groups cross the zero line.
2. Autoregressive Section:
- Prior Hearing to Hearing: All groups show strong positive estimates clustered between 0.4 and 0.5. Error bars are very narrow and do not cross zero.
- Prior Loneliness to Loneliness: All groups show strong positive estimates between 0.3 and 0.45. Error bars are narrow and do not cross zero.
A legend at the bottom indicates Relationship Type: an orange line for Bidirectional Female 45–64 and a blue line for Unidirectional Male 65+.
The results showed that for females aged 45–65 years at baseline, there was a bi-directional association between self-reported residual hearing and loneliness. That is, poorer self-reported residual hearing at the prior timepoint was associated with greater loneliness at the next timepoint (β = .018, 95% CI: .00 to .04, p = .027; path c), independent of the effect of covariates in the model. Additionally, for females aged 45–64 years, greater loneliness at the prior timepoint was independently associated with poorer self-reported residual hearing at the next timepoint (β = .015, p = .026, 95% CI: .00 to .03; path d). These bi-directional effects were not statistically significant in any other sub-group. For males 65+, cross-lagged effects from self-reported residual hearing to subsequent loneliness were significant (β = .019, p = .038, 95% CI: .00 to .04; path c), whereas effects from loneliness to self-reported residual hearing were not significant. Thus, for males 65 + years old, poorer self-reported residual hearing at the prior timepoint was associated with increased loneliness at the next timepoint, but loneliness did not predict future declines in hearing (i.e., unidirectionality of the data, hearing to loneliness).
Autoregressive paths for self-reported residual hearing (path a) and loneliness (path b) were consistently strong across timepoints and sub-groups. For self-reported residual hearing, autoregressive paths ranged from β = .426 to .512. For loneliness, paths ranged from β = .324 to .407. All autoregressive paths were statistically significant at p < .001, indicating moderate to high stability of self-reported residual hearing and loneliness over time. These autoregressive paths reflect the extent to which individuals’ levels of hearing and loneliness tended to persist over time: participants with poorer self-reported residual hearing or higher loneliness at one timepoint were likely to report similarly poorer hearing or higher loneliness at the next timepoint, regardless of changes in the other construct, cross-lagged effects, or covariates.
At baseline, residual correlations between self-reported residual hearing and loneliness were statistically significant and positive across all four sub-groups (β = .031 to .049, p < .05). At FU1 and FU2, residual covariances between self-reported residual hearing and loneliness remained statistically significant for males 45–65 (r = .029, p < .001). Among older adults, only males 65+ years old showed significant residual covariances between self-reported residual hearing and loneliness at FU1 and FU2 (r = .022–.023, p < .05), whereas older females showed no significant residual associations at either follow-up timepoint (r = −.001, p = .947).
To examine whether observed longitudinal associations were robust to adjustment for cardiovascular-related health factors, additional models were estimated, including cardiovascular covariates (i.e., smoking, heart disease, high blood pressure, heart attack, angina, diabetes, stroke, and transient ischemic attack). Model fit remained acceptable and comparable to the primary analyses (χ2(20) = 311.30, p < .001, CFI = .991, RMSEA = .046, SRMR = .007).
In these adjusted models, cross-lagged associations from loneliness to self-reported residual hearing were no longer statistically significant in most sub-groups. However, among females aged 45–64 years, a small bi-directional association between self-reported residual hearing and loneliness remained. Specifically, poorer self-reported residual hearing at the prior timepoint was associated with loneliness at the subsequent timepoint (β = .018, p = .033), and greater loneliness at the prior timepoint was associated with poorer subsequent self-reported residual hearing (β = .015, p = .033). No statistically significant cross-lagged effects were observed in the remaining sub-groups. As in the primary analysis, autoregressive paths for both self-reported residual hearing and loneliness remained statistically significant and moderate to strong in magnitude across all sub-groups (hearing: β ≈ .44–.51; loneliness: β ≈ .32–.41, all p < .001), indicating substantial stability of both constructs over time.
To further explore whether hearing device use was associated with differences in longitudinal associations between self-reported residual hearing and loneliness, additional CLPMs were estimated separately for participants who did not use hearing devices (n = 26,522) and those who reported hearing device use at baseline (n = 1,587). Both models demonstrated a good fit to the data (non-users: CFI = .990, RMSEA = .049; device users: CFI = .991, RMSEA = .035). Among participants who did not use hearing devices, statistically significant bi-directional cross-lagged associations were observed between self-reported residual hearing and loneliness. Poorer self-reported residual hearing at the prior timepoint was associated with greater loneliness at the subsequent timepoint (β = .011, p = .021; path c), and greater loneliness at the prior timepoint was similarly associated with poorer self-reported residual hearing at the subsequent timepoint (β = .009, p = .028; path d).
In contrast, among hearing device users (n = 1,587), cross-lagged associations between self-reported residual hearing and loneliness were not statistically significant. Neither self-reported residual hearing predicting subsequent loneliness nor loneliness predicting subsequent self-reported residual hearing reached statistical significance across adjacent timepoints. As in the non-user group, autoregressive paths for both self-reported residual hearing and loneliness remained statistically significant and moderate in magnitude, indicating temporal stability within constructs.
Discussion
This study examined longitudinal associations between self-reported residual hearing and loneliness over three timepoints using CLSA data, with analyses by age and sex. Across analyses, both self-reported residual hearing and loneliness showed moderate to strong stability over time, and these stability effects were substantially larger than the cross-lagged associations. This pattern has implications for interpretation, as strong autoregressive (stability) effects suggest that prior levels of hearing and loneliness account for a large portion of the variance at subsequent timepoints, leaving limited variance to be explained by cross-lagged pathways. Cross-lagged effects should therefore be interpreted as incremental and conditional on prior levels of each construct, rather than strong directional influences. Although some statistically significant cross-lagged paths were observed, the overall pattern suggests that hearing and loneliness are relatively stable domains (over approximately 6 years), with limited and sub-group-specific evidence of longitudinal associations. Additionally, these findings should be interpreted within the context of the CLSA sample, which excludes certain populations (e.g., individuals in long-term care, those unable to complete the assessments in English or French) and relies on self-reported measures, which may limit generalizability to the broader and more diverse Canadian aging population.
The finding that self-reported residual hearing and loneliness were associated at the same timepoints is consistent with previous cross-sectional research showing associations between hearing and loneliness, including population studies using self-reported and behavioural hearing measures (Döge et al., Reference Döge, Hackenberg, Beutel, Otten, Wild, Chalabi, Ghaemi Kerahrodi, Münzel, Lackner and Schmidtmann2025; Mick et al., Reference Mick, Parfyonov, Wittich, Phillips and Pichora-Fuller2018). The observed pathway from poorer self-reported residual hearing to later loneliness among males aged 65 years and older is also consistent with prior longitudinal research that hearing loss may contribute to later loneliness in some groups (Pronk et al., Reference Pronk, Deeg, Smits, van Tilburg, Kuik, Festen and Kramer2011; Wagner et al., Reference Wagner, Schonenberg and Prell2025). Pronk et al. (Reference Pronk, Deeg, Smits, van Tilburg, Kuik, Festen and Kramer2011), for example, found that poorer self-reported hearing predicted increased loneliness for men and those who did not use hearing aids. Wagner et al. (Reference Wagner, Schonenberg and Prell2025) also reported that poorer self-reported hearing predicted loneliness 2 years later.
However, it is important to note that the hearing to loneliness effect in the current study was small (β = .018), not consistent across sub-groups, and did not persist when cardiovascular covariates were included in the model. This attenuation suggests that the observed association may be partly explained by shared underlying health factors, such as cardiovascular and metabolic risk, rather than reflecting a robust independent pathway from hearing to loneliness. Although intervention study data suggest that hearing interventions or rehabilitation may improve or help stabilize loneliness and social outcomes (e.g., Applebaum et al., Reference Applebaum, Hoyer, Betz, Lin and Goman2019; Jones et al., Reference Jones, Siever, Knuff, Van Bergen, Mick, Little and Miller2019; Weinstein et al., Reference Weinstein, Sirow and Moser2016), the present observational results should not be interpreted as direct evidence that intervening on hearing loss will reduce loneliness. Rather, they provide limited population-level evidence that poorer residual self-reported hearing may precede later loneliness in some groups (i.e., older men), within a broader context of shared health and social factors.
Among females aged 45–64, small bi-directional associations were observed between self-reported residual hearing and loneliness. This finding aligns with emerging evidence that loneliness may not only be an outcome of changes in hearing but may also precede poorer hearing (Song et al., Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025; Stephan et al., Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026). Specifically, Song et al. (Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025) found that higher levels of loneliness predicted subsequent hearing loss using ICD-10 diagnostic codes, while Stephan et al. (Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026) reported similar prospective associations using pure-tone audiometry measures. These studies reported associations that were relatively consistent across age groups, while the present study identified bi-directional effects only within a specific sub-group (i.e., females 45–64).
Two key differences in study design may explain the lack of age group consistency in our study. First, the present study used a measure of self-reported hearing ability (with or without device use) rather than clinically diagnosed or behaviourally measured hearing. This measure may be less sensitive to physiological or clinical changes in auditory function captured by audiometry or medical records. Second, the analytic approaches substantially differ. While Song et al. (Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025) and Stephan et al. (Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026) examined prospective associations in a primary unidirectional framework (i.e., loneliness predicting later hearing outcomes), the present study used CLPMs to simultaneously estimate bi-directional associations while accounting for prior levels of both constructs. This approach provides a more conservative test of directional effects, as each pathway is adjusted for stability within constructs over time. Given the strong stability observed for both hearing and loneliness, this modelling framework may attenuate cross-lagged effects and reveal only those associations that are sufficiently robust within specific sub-groups. As a result, the smaller and more sub-group-specific effects observed in the present study may reflect the attenuation of associations once prior levels of hearing and loneliness are taken into account.
A further difference between the present study and prior longitudinal work relates to the duration of follow-up. Song et al. (Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025) examined incident hearing loss over a median follow-up of 12.3 years, while Stephan et al. evaluated hearing outcomes across 8–10-year periods. In contrast, the current CLSA analysis captured associations over approximately 6–8 years, depending on baseline enrollment timing. It is possible that longer follow-up periods may allow small cumulative associations between loneliness and hearing to emerge more consistently across broader populations and age groups. Shorter follow-up intervals, combined with strong autoregressive stability, may instead result in more modest or sub-group-specific associations.
Importantly, the cardiovascular adjusted models provide additional context for integrating these findings. While the bi-directional association for females 45–64 years of age remained statistically significant (yet small) after adjustment, cross-lagged effects were not observed in other groups, and overall effect sizes were attenuated. This pattern suggests that cardiovascular and health factors do not fully account for the observed bi-directional association in this sub-group but may contribute to the lack of consistent effects across the broader population. These findings are consistent with prior work (e.g., Song et al., Reference Song, Steptoe, Yang, Ma, Guo, Yu and Xia2025; Stephan et al., Reference Stephan, Sutin, Luchetti, Karakose, O’Súilleabháin and Terracciano2026), which highlights cardiovascular and inflammatory processes as potential mechanisms linking loneliness and hearing.
Implications and future directions
The present findings have implications for understanding the relationship between hearing and loneliness in Canadian population-based data, although these implications should be interpreted cautiously given the modest effect sizes, observational design, self-report measures, and a community-dwelling sample that may not fully represent more diverse or higher-risk older populations in Canada. Across analyses, cross-lagged associations were small, not consistently observed across sub-groups, and were attenuated after being adjusted for cardiovascular-related factors. This suggests that hearing and loneliness may be connected in part through shared underlying health and social determinants, rather than through strong, consistent directional pathways. Although the bi-directional association was small and limited to females 45–64, the pattern of bi-directionality is in alignment with interventions addressing both hearing health and social connection, such as group-based audiology rehabilitation and communication partner training (Reed, Reference Reed2010; Jones et al., Reference Jones, Siever, Knuff, Van Bergen, Mick, Little and Miller2019).
As a secondary analysis, we examined whether longitudinal associations between self-reported residual hearing and loneliness differed between participants who reported hearing device use and those who did not. These findings are preliminary and limited by the smaller sample size of device users and the use of a binary measure of device use, which does not capture timing, adherence, or type of intervention. Evidence from the ACHIEVE trial, as well as shorter auditory rehabilitation programs, suggests that hearing-focused intervention may improve or help stabilize social outcomes (Jones et al., Reference Jones, Siever, Knuff, Van Bergen, Mick, Little and Miller2019; Reed et al., Reference Reed, Chen, Huang, Pike, Arnold and Burgard2025; Weinstein et al., Reference Weinstein, Sirow and Moser2016). The current findings indicate that such effects are not clearly reflected in population-level longitudinal associations and may depend on broader context and factors such as health status, social engagement, and access to hearing care.
Future research with more detailed measurement of hearing care (e.g., uptake, adherence, and rehabilitation support) and designs that distinguish within-person change from stable between-person differences will be important for clarifying how hearing and loneliness are related over time. Future research should also more directly examine longitudinal predictors of hearing care uptake, including whether loneliness influences the likelihood of adopting hearing devices over time (Jansen et al., Reference Jansen, van Wier, Lissenberg-Witte, Smits and Kramer2025; Singh et al., Reference Singh, Goy, Wright-Whyte, Chasteen and Pichora-Fuller2025). From a clinical perspective, the present findings support the value of assessing both hearing and psychosocial well-being in older adults. Integrating screening for loneliness with hearing care and considering hearing difficulties within broader assessments of social and mental health may be useful for identifying individuals who could benefit from comprehensive, multidisciplinary support.
Strengths and limitations
Key strengths of this study are the use of large-scale longitudinal data from the CLSA, which enabled robust sub-group analysis by age and sex. The present study extends prior longitudinal and intervention-oriented work by explicitly testing bi-directional associations between hearing and loneliness. Among limitations, both hearing and loneliness were assessed via self-report, which may introduce biases (e.g., social desirability bias, recall bias, and response style differences), as well as discrepancies between self-reported versus behavioural assessments of sensory changes. Moreover, although typical of CLPM studies (see Orth et al., Reference Orth, Meier, Bühler, Dapp, Krauss, Messerli and Robins2024), the effect sizes of associations identified were small (approximately β = .02) and therefore suggest that there are likely many other factors that contribute to the associations between hearing and loneliness for future research to investigate. Although the CLSA provides a robust sample size for sub-group analysis by age and sex, the sample is primarily White and well educated. Our results may therefore reflect psychosocial and sensory aging that is more prevalent in this population. In a cross-sectional analysis of the 2022 Health and Retirement Study, Lewis et al. (Reference Lewis, Malak, Hamada and Toman2025) reported that Black older adults exhibited higher levels of loneliness compared to White older adults. However, this pattern reversed after accounting for socioeconomic and health factors in the model, suggesting that loneliness among White older adults may be more strongly tied to these factors. Lewis et al. (Reference Lewis, Malak, Hamada and Toman2025) also showed that Hispanic older adults consistently reported the lowest loneliness. It will be important for future longitudinal research to incorporate diverse samples to investigate whether the bi-directional associations between hearing and loneliness identified in our study extend to different cultural and ethnic groups.
An additional limitation relates to sex differences in the timing and progression of hearing loss. Males tend to experience earlier onset and more rapid progression of hearing loss than females, which may partially confound age-based sub-group comparisons (Humes, Reference Humes2023). Consequently, some observed age- and sex-specific patterns may reflect greater severity of hearing loss rather than chronological age. Although models adjusted for baseline hearing and accounted for within-person stability over time, future research should further disentangle age, sex, and degree of hearing impairment, ideally using objective audiometric thresholds or stratification by severity of hearing loss.
Conclusion
This study adds to the limited body of longitudinal research examining associations between hearing and loneliness in aging populations using large-scale Canadian cohort data. Across analyses, both loneliness and self-reported residual hearing showed moderate to strong stability over time, while cross-lagged associations were small and inconsistent across sub-groups. Our findings reveal sub-group-specific patterns, including bi-directional associations among women 45–64 years of age and unidirectional effects from hearing to loneliness among older men. However, these effects were modest and attenuated when cardiovascular covariates were included in the model, suggesting that shared health processes may contribute to these associations. Future research is needed to clarify potential mechanisms, sub-group differences, and implications for hearing care and community services.
Supplementary material
The supplementary material for this article can be found at http://doi.org/10.1017/S0714980826100774.
Data availability statement
Data are available from the Canadian Longitudinal Study on Aging (www.clsa-elcv.ca) for researchers who meet the criteria for access to de-identified CLSA data. Dr. Julie Beadle was the recipient of a CLSA Data Access Trainee Fee Waiver. The opinions expressed in this manuscript are the author’s own and do not necessarily reflect the views of the Canadian Longitudinal Study on Aging.
Acknowledgements
This research was made possible using the data/biospecimens collected by the Canadian Longitudinal Study on Aging (CLSA). Funding for the Canadian Longitudinal Study on Aging (CLSA) is provided by the Government of Canada through the Canadian Institutes of Health Research (CIHR) under grant reference: LSA 94473 and the Canada Foundation for Innovation, as well as the following provinces: Newfoundland, Nova Scotia, Quebec, Ontario, Manitoba, Alberta, and British Columbia. This research has been conducted using the CLSA dataset Baseline Comprehensive Dataset, Version 7.0, Follow-Up 1 Comprehensive Dataset, Version 5.0, and Follow-Up 2 Comprehensive Dataset, Version 2.0, under Application Number 2401011. The CLSA is led by Drs. Parminder Raina, Christina Wolfson, and Susan Kirkland. The time and commitment of the participants to the CLSA study platform are gratefully acknowledged, without whom this research would not be possible. The authors acknowledge funding from Canadian Hearing Services awarded to Andrew Wister.



 Open access

