


Introduction
Social connections are essential for human survival and functioning, with positive social relationships providing guidance, support and safety essential for healthy development (Holt-Lunstad, Reference Holt-Lunstad2022; Umberson & Montez, Reference Umberson and Karas Montez2010). A large body of research from across the social and behavioral sciences indicates that social experiences are interlinked with health and well-being across the lifespan (Holt-Lunstad, Reference Holt-Lunstad2022). Deficits in social relationships, particularly isolation and loneliness experienced early in life, are associated with poor mental health (Matthews et al., Reference Matthews, Danese, Wertz, Ambler, Kelly, Diver, Caspi, Moffitt and Arseneault2015; Qualter et al., Reference Qualter, Brown, Munn and Rotenberg2010), functioning (Thompson et al., Reference Thompson, Odgers, Bryan, Danese, Milne, Strange, Matthews and Arseneault2022; von Soest et al., Reference von Soest, Luhmann and Gerstorf2020) and socioeconomic outcomes (Bryan et al., Reference Bryan, Thompson, Goldman-Mellor, Moffitt, Odgers, So, Rahman, Wertz, Matthews and Arseneault2024). Growing awareness of the wide-reaching consequences of loneliness and social isolation has seen these phenomena become an important focus for researchers (Luhmann et al., Reference Luhmann, Buecker and Rüsberg2023; Umberson & Donnelly, Reference Umberson and Donnelly2023), as well as governments, public health bodies and third sector organizations across the world (Department for Culture, Media and Sport, 2023; Ending Loneliness Together [ELT], 2023; US Surgeon General, 2023; WHO, 2025).
Social isolation is conceptualized as the absence of positive social relationships and low embeddedness in social networks, typically characterized by a small social network and few social interactions (Holt-Lunstad & Steptoe, Reference Holt-Lunstad and Steptoe2022). Beyond this objective lack of social relationships, loneliness is defined as subjective dissatisfaction with the quality or quantity of one’s social relationships (Perlman & Peplau, Reference Perlman and Peplau1981; van Tilburg & de Jong Gierveld, Reference Van Tilburg and de Jong Gierveld2023). While loneliness and social isolation often co-occur, they are conceptually distinct and the correlation between the two constructs is modest (Coyle & Dugan, Reference Coyle and Dugan2012; Matthews et al., Reference Matthews, Danese, Wertz, Ambler, Kelly, Diver, Caspi, Moffitt and Arseneault2015). Indeed, loneliness may be experienced by individuals with abundant social connections and some individuals with little social contact may not feel lonely (de Jong Gierveld et al., Reference de Jong Gierveld, van Tilburg, Dykstra, Perlman and Vangelisti2006). While this conceptual distinction between loneliness and social isolation is widely accepted across the research literature, how these constructs relate and interact with each other over time has not been clearly characterized.
The evolutionary theory of loneliness considers social isolation to be a danger to an individual’s survival and proposes that loneliness has evolved as an adaptive signal that one’s beneficial social relationships are under threat (Cacioppo et al. Reference Cacioppo, Cacioppo and Boomsma2013; Cacioppo & Cacioppo, Reference Cacioppo, Cacioppo and Olson2018; Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015). Within this framework, the aversive experience of loneliness can work to motivate socially isolated individuals to build or rebuild positive social relationships through a series of cognitive and behavioral processes (Cacioppo & Cacioppo, Reference Cacioppo, Cacioppo and Olson2018). Specifically, loneliness may buffer the persistence of social isolation over time such that isolated individuals who experience loneliness may go on to have more social connections later on than other similarly isolated but less lonely individuals (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015), particularly when episodes of loneliness are short lived (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015). Although this reaffiliation process represents one mechanism within the broader evolutionary framework, it is reflected in qualitative research in which lonely individuals from childhood to older age consistently report that they experience loneliness as an aversive state that prompts them to improve or pursue new relationships and seek support from others (Besevegis & Galanaki, Reference Besevegis and Galanaki2010; McKenna-Plumley et al., Reference McKenna-Plumley, Turner, Yang and Groarke2023; Qualter et al., Reference Qualter, Verity, Walibhai, Fuhrmann, Riddleston, Alam, Conway and Lau2025; Schoenmakers et al., Reference Schoenmakers, van Tilburg and Fokkema2012).
While this conceptualization of loneliness as adaptive and motivating social connection is referenced widely in the literature on social connection (Hussain & Palmer, Reference Hussain and Palmer2024; Maes & Vanhalst, Reference Maes and Vanhalst2025; Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015), few studies have examined the role of loneliness in shaping social isolation over time. Loneliness is associated with a wide range of social difficulties that may act as barriers to building positive relationships, such that loneliness may precede social isolation or exacerbate it over time, rather than reduce it. Loneliness is consistently associated with withdrawal from social interactions (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015), with lonely individuals being less trusting of others and more anxious and pessimistic than less lonely people (Cacioppo et al., Reference Cacioppo, Hawkley, Ernst, Burleson, Berntson, Nouriani and Spiegel2006; Langenkamp, Reference Langenkamp2023; Lieberz et al., Reference Lieberz, Shamay-Tsoory, Saporta, Esser, Kuskova, Stoffel-Wagner, Hurlemann and Scheele2021). Lonely individuals also struggle to use their social skills (Knowles et al., Reference Knowles, Lucas, Baumeister and Gardner2015) and approach social situations in a more defensive manner (Cacioppo et al., Reference Cacioppo, Hawkley, Ernst, Burleson, Berntson, Nouriani and Spiegel2006; Cacioppo & Hawkley, Reference Cacioppo and Hawkley2009), such that even if they are motivated to seek connections with others, these attempts to reconnect may not be successful. As such, experiencing loneliness may precede or exacerbate social isolation, forming a self-reinforcing cycle of escalating social isolation and loneliness over time. Indeed, although evidence from older populations suggest that loneliness may facilitate the rekindling of existing social ties, it may also reduce motivation or success in forming new ties (Rook et al., Reference Rook, Oleskiewicz, Brown, August, Smith and Sorkin2024), with loneliness and social isolation dynamically reinforcing each other across time (Chang et al., Reference Chang, Chen, Xi, Wang and Chu2025; Das, Reference Das2021; Pan, Reference Pan2024).
While evolutionary loneliness theory acknowledges that the social difficulties and withdrawal associated with loneliness may exacerbate social isolation over time, research examining the theory has largely focused on the cognitive processes through which loneliness is hypothesized to motivate social behavior, rather than its effect on actual social isolation over time (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015). Further, although the theory was introduced in relation to adults, the prevalence and impact of loneliness and social isolation are increasingly recognized across childhood and young adulthood (Barreto et al., Reference Barreto, Victor, Hammond, Eccles, Richins and Qualter2021). In these developmental stages, the structure, purpose and dynamics of social relationships differ from adulthood (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015), such that the impact of loneliness on social behavior may also differ and be long-lasting. In particular, understandings of adulthood social isolation as an overall lack of social contact are not appropriate for children and adolescents who are typically connected to other people in the family and school environment (Caspi et al., Reference Caspi, Harrington, Moffitt, Milne and Poulton2006). As such, social isolation in this developmental stage can be conceptualized as poor integration into peer networks as indicated by social withdrawal and peer rejection (Caspi et al., Reference Caspi, Harrington, Moffitt, Milne and Poulton2006, Danese et al., Reference Danese, Moffitt, Harrington, Milne, Polanczyk, Pariante, Poulton and Caspi2009; Lacey et al., Reference Lacey, Kumari and Bartley2014; Lay-Yee et al., Reference Lay-Yee, Hariri, Knodt, Barrett-Young, Matthews and Milne2023; Thompson et al., Reference Thompson, Agnew-Blais, Allegrini, Bryan, Danese, Odgers, Matthews and Arseneault2023). In light of the distinct presentation of social isolation in childhood and adolescence, alongside broader developmental changes such as educational transitions, the influence of loneliness on social isolation during this developmental stage may differ from that observed later in life. Longitudinal research using repeated measures of loneliness and social isolation is needed to test these competing hypotheses and unravel how loneliness and social isolation lead to each other and interact across time early in life.
Similarly, while a growing body of evidence indicates that both loneliness and social isolation have wide-reaching consequences for individuals’ health and life chances (Holt-Lunstad, Reference Holt-Lunstad2017), few studies have investigated how loneliness and social isolation work together, or separately, to shape later outcomes. Although existing evidence indicates that loneliness and social isolation are independently associated with mental health conditions and mortality (Holt-Lunstad et al., Reference Holt-Lunstad, Smith, Baker, Harris and Stephenson2015; Matthews et al., Reference Matthews, Danese, Wertz, Odgers, Ambler, Moffitt and Arseneault2016), their independent effects on physical health conditions are less consistent and their independent effects on socioeconomic outcomes have not been investigated (Leigh-Hunt et al., Reference Leigh-Hunt, Bagguley, Bash, Turner, Turnbull, Valtorta and Caan2017).
Meanwhile, a robust body of research on cumulative risk exposure indicates that exposure to multiple social adversities in childhood, such as maltreatment, bullying, neglect and community violence, are associated with more severe negative consequences than exposure to a single risk factor (Deniz et al., Reference Deniz, Humphrey, Demkowicz, Lereya and Deighton2025; Evans et al., Reference Evans, Li and Whipple2013; Fisher et al., Reference Fisher, Caspi, Moffitt, Wertz, Gray, Newbury, Ambler, Zavos, Danese, Mill, Odgers, Pariante, Wong and Arseneault2015; Hardi et al., Reference Hardi, Peckins, Mitchell, McLoyd, Brooks-Gunn, Hyde and Monk2025). Similar to other risk factors for poor health and functioning, loneliness and social isolation may follow this accumulation principle such that experiencing both social deficits may have additive effects on long-term outcomes. Additionally, loneliness and social isolation may have synergistic effects on negative outcomes, with loneliness exacerbating the corrosive effects of social isolation. Lonelier individuals may be more sensitive to social isolation, finding the experience more stressful and resulting in greater impacts on health, wellbeing and functioning than in less lonely individuals.
While a small number of studies point to cumulative effects of loneliness and isolation in mid-life and older adulthood on health, disability and quality of life (Barnes et al., Reference Barnes, MacLeod, Tkatch, Ahuja, Albright, Schaeffer and Yeh2021; Shimada et al., Reference Shimada, Doi, Tsutsumimoto, Makino, Harada, Tomida, Morikawa and Arai2025), as well as synergistic effects on mortality risk (Beller & Wagner, Reference Beller and Wagner2018; Foster et al., Reference Foster, Gill, Mair, Celis-Morales, Jani, Nicholl, Lee and O’Donnell2023; Ward et al., Reference Ward, May, Normand, Kenny and Nolan2021), these studies have largely relied on cross-sectional data and focused on physical health in later life. As a result, the interplay of loneliness and social isolation before adulthood and their combined effects on poor outcomes are not well understood. Longitudinal research using repeated measures of loneliness and social isolation during childhood and adolescence is needed to better understand how they work together to impact long-term outcomes and inform intervention strategies to identify young people at most risk of poor health, functioning and socioeconomic outcomes.
Aims and hypotheses
In this study, we investigated the interplay of loneliness and social isolation at two time points across childhood and late adolescence, and how they work together to influence health, functional and socioeconomic outcomes in a nationally representative British cohort. In particular, we aimed to investigate five questions, with six related hypotheses:
-
1. How are loneliness and social isolation associated with each other from early to late adolescence?
-
We hypothesized that both phenomena in early adolescence precede loneliness and social isolation in later adolescence (H1).
-
2. Does loneliness buffer or exacerbate the associations between earlier social isolation and later isolation?
-
We hypothesized that loneliness does not buffer the association between earlier and later isolation but exacerbates isolation over time (H2).
-
3. Are loneliness and social isolation independently associated with later and concurrent mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
We hypothesized that loneliness and isolation are independently associated with poor mental health, coping and wellbeing, health behaviors and socioeconomic outcomes, even when controlling for each other (H3), and that these associations are partially, but not fully, explained by childhood indicators of mental health and functioning (H4).
-
4. Do loneliness and social isolation have a cumulative effect on concurrent and later outcomes?
We hypothesized that individuals who experience high levels of both loneliness and social isolation experience worse mental health, physical health behaviors, employment and coping behaviors than individuals who experience only one of the phenomena (H5).
-
5. Does loneliness exacerbate the association between social isolation and concurrent and later outcomes?
-
We hypothesized that loneliness exacerbates the association between social isolation and concurrent and future mental health, coping and wellbeing, health behaviors, and socioeconomic outcomes (H6).
Methods
Participants
Participants were members of the Environmental Risk (E-Risk) Longitudinal Twin Study, which follows the development of a cohort of 2,232 British twins. The sample was drawn from a larger birth register of twins born in England and Wales in 1994–1995 (Trouton et al., Reference Trouton, Spinath and Plomin2002). Full details of the sample are reported elsewhere (Moffitt & E-Risk Study Team, Reference Moffitt2002). Briefly, the E-Risk sample was constructed in 1999–2000, when 1,116 families (93% of those eligible) with same-sex 5-year-old twin pairs participated in home-visit assessments. This sample comprised 56% monozygotic (MZ) and 44% dizygotic (DZ) twin pairs. Sex was evenly distributed within zygosity (49% male). Ninety percent of participants were of White ethnicities. The study sample’s neighborhoods represent the full range of socioeconomic conditions in Great Britain. Figure S1 illustrates that E-Risk study families’ addresses mirror the deciles of the UK government’s 2015 Index of Multiple Deprivation, which ranks British neighborhoods in terms of relative deprivation at an area level of approximately 1,500 residents. Approximately 10% of the E-Risk study cohort fills each of the index’s 10% bands, indicating that the cohort accurately represents the distribution of deprivation in the United Kingdom (full detail in Supplement A).
Follow-up home visits were conducted when the children were aged 7 (98% participation), 10 (96%), 12 (96%), and 18 years (93%). A total of 2,066 individuals participated in the E-Risk assessments at age 18. All interviews were conducted after participants’ 18th birthday; the average age of the twins at the time of the assessment was 18.4 years (standard deviation [SD] = 0.36). There were no differences between those who did and did not take part at age 18 in terms of parental socioeconomic status (SES) assessed when the cohort was initially defined (χ2(2, N = 2,232) = 0.86, p = 0.65), age-5 IQ scores (t(2,208) = 0.98, p = 0.33), or age-5 emotional or behavioral problems (t(2,230) = 0.40, p = 0.69 and t(2,230) = 0.41, p = 0.68, respectively). Home visits at ages 5, 7, 10, and 12 years included assessments with participants as well as their mother or primary caretaker. The home visit at age 18 included interviews only with the participants.
The Joint South London and Maudsley and the Institute of Psychiatry Research Ethics Committee approved each phase of the study. Parents gave informed written consent, and twins gave assent between 5 and 12 years. Twins gave informed written consent at age 18.
Measures
Loneliness and social isolation
Loneliness. A measure of loneliness at age 12 was derived using three items from the Children’s Depression Inventory (Kovacs, Reference Kovacs1992; Matthews et al., Reference Matthews, Qualter, Bryan, Caspi, Danese, Moffitt, Odgers, Strange and Arseneault2023). Each item was presented as a set of three statements, and participants were instructed to select the statement that described them best: (1) “I do not feel alone,” “I feel alone many times” or “I feel alone all the time”; (2) “I have plenty of friends,” “I have some friends but I wish I had more” or “I do not have any friends”; and (3) “Nobody really loves me,” “I am not sure if anybody loves me,” or “I am sure that somebody loves me.” Items were coded 0–2, while item 3 was reverse coded. Responses were summed to produce a scale from 0 to 6 (mean = 0.48, SD = 0.86, ω = 0.49) where higher scores indicate higher feelings of loneliness.
Loneliness was measured at age 18 using four items from the UCLA Loneliness Scale, Version 3 (Russell, Reference Russell1996): “How often do you feel that you lack companionship?”, “How often do you feel left out?”, “How often do you feel isolated from others?” and “How often do you feel alone?” A very similar short form of the UCLA scale has previously been developed for use in large-scale surveys, and correlates strongly with the full 20-item version (Hughes et al., Reference Hughes, Waite, Hawkley and Cacioppo2004). At age 18, the scale was administered as part of a self-complete questionnaire. The items were rated “hardly ever” (0), “some of the time” (1), or “often” (2). Items were summed to produce a total loneliness score from 0 to 8 (mean = 1.57, SD = 1.94, ω = 0.84).
The correlation between loneliness measured at age 12 and at age 18 was moderate (r = 0.25, p < 0.001). The pattern of associations between loneliness and established correlates including mental health, personality and social isolation were similar for both the age-12 loneliness measure and the UCLA scale used at age 18 (Table S1).
Social isolation. At age 12, social isolation was assessed using six items from the Child Behavior Checklist (CBCL; Achenbach, Reference Achenbach1991a) and the matching items from the Teacher’s Report Form (TRF; Achenbach, Reference Achenbach1991b). The selected items were “would rather be alone than with others,” “not liked by other children [pupils],” “withdrawn, doesn’t get involved with others,” “complains of loneliness,” “doesn’t get along with other children [pupils]” and “feels or complains that no-one loves him/her.” This approach maps onto the conceptualization of childhood social isolation as a lack of social relationships resulting from social rejection and withdrawal proposed by Caspi and colleagues (2006) and utilized in previous research on early life social isolation (Danese et al., Reference Danese, Moffitt, Harrington, Milne, Polanczyk, Pariante, Poulton and Caspi2009; Matthews et al., Reference Matthews, Rasmussen, Ambler, Danese, Eugen-Olsen, Fancourt, Fisher, Iverson, Schultz, Sugden, Williams, Caspi and Moffitt2024; Thompson et al., Reference Thompson, Agnew-Blais, Allegrini, Bryan, Danese, Odgers, Matthews and Arseneault2023). Mothers completed the questionnaire in a face-to-face interview and teachers responded by post. For each respondent, items were summed to create two social isolation scales at each age; the mother and teacher scales were moderately correlated (r = 0.31, p < 0.001). This level of agreement is consistent with previous findings of parent and teacher ratings of children’s behavior and may be partly accounted for by situational specificity (Achenbach et al., Reference Achenbach, McConaughy and Howell1987). To integrate observations both in the classroom environment and outside of school, we averaged mothers’ and teachers’ reports to create a scale where higher scores reflect increased isolation (range = 0–11, mean = 0.94, SD = 1.37, ω mother-report = 0.76, ω teacher-report = 0.77, α = 0.78).
Social isolation was measured at age 18 using the Multidimensional Scale of Perceived Social Support (MSPSS, 12-item; Zimet et al., 1998). The MSPSS reflects an individual’s access to supportive relationships with family and friends. Although social isolation in adulthood is often assessed using indicators such as marital status or living alone (Holt-Lunstad & Steptoe, Reference Holt-Lunstad and Steptoe2022), these were not applicable to most 18-year-olds in the E-Risk cohort. In young adulthood, social isolation is more appropriately reflected in ties to friends, family and other close relationships. As access to support is contingent on maintaining these social ties, low social support reflects reduced embeddedness in a broader social network and was used here as a proxy for social isolation. The MSPSS includes twelve self-report items which consist of statements such as ‘‘there is a special person who is around when I am in need’’ and ‘‘I can count on my friends when things go wrong.’’ Participants rated these statements as ‘‘not true’’ (0), ‘‘somewhat true’’ (1) or ‘‘very true’’ (2). We reversed the scoring and summed the responses to produce a scale with higher scores reflecting greater social isolation (range = 0–24, mean = 3.28, SD = 4.34, ω = 0.94, α = 0.88).
The correlation between social isolation assessed at age 12 and at age 18 was r = 0.21 (p < 0.001). The pattern of associations between social isolation and mental health, personality, sex and loneliness were similar for both the age-12 and age-18 measures (Supplement B, Table S1).
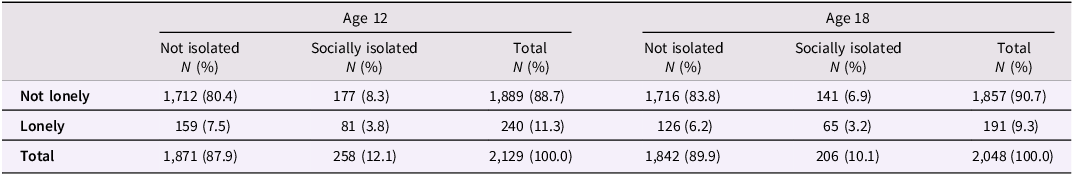
Cumulative loneliness and social isolation. To compute a cumulative measure of loneliness and social isolation at ages 12 and 18, we first dichotomized the scales, with individuals in the approximate top decile of each scale coded as lonely or isolated. This use of a top decile cut-off to capture loneliness and isolation is consistent with previous research in this cohort (Matthews et al., Reference Matthews, Qualter, Bryan, Caspi, Danese, Moffitt, Odgers, Strange and Arseneault2023) and mirrors the number of adolescents who report feeling lonely often (Office for National Statistics [ONS], 2018). At age 12, participants with a loneliness score greater than 1 were coded as lonely and participants with a social isolation score greater than 2 were coded as isolated (Table 1). At age 18, participants who scored higher than 4 on loneliness were classified as lonely and participants with social isolation scores greater than 9 were classified as isolated. We then classified participants as (1) neither lonely nor isolated, (2) lonely only, (3) isolated only, or (4) both lonely and isolated (Table 1).
Proportion of participants classified as lonely or socially isolated for the creation of a cumulative measure of loneliness and social isolation at ages 12 and 18
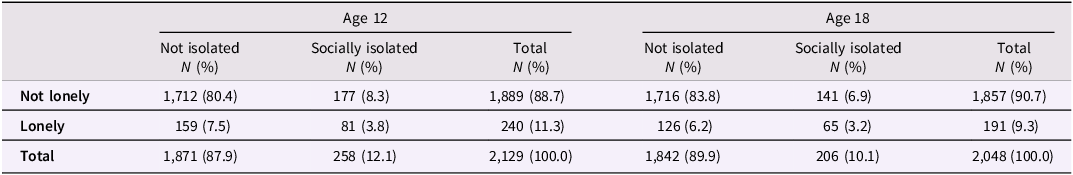
Table 1. Long description
The table presents the proportion of participants classified as lonely or socially isolated at ages 12 and 18. It has four rows and six columns. The columns are labeled as Not isolated, Socially isolated, and Total for both ages 12 and 18. The rows are labeled as Not lonely, Lonely, and Total. The values in the table are as follows: Row 1: Not lonely, Not isolated, 1,712 (80.4 percent), Socially isolated, 177 (8.3 percent), Total, 1,889 (88.7 percent). Row 2: Lonely, Not isolated, 159 (7.5 percent), Socially isolated, 81 (3.8 percent), Total, 240 (11.3 percent). Row 3: Total, Not isolated, 1,871 (87.9 percent), Socially isolated, 258 (12.1 percent), Total, 2,129 (100.0 percent). Row 4: Not lonely, Not isolated, 1,716 (83.8 percent), Socially isolated, 141 (6.9 percent), Total, 1,857 (90.7 percent). Row 5: Lonely, Not isolated, 126 (6.2 percent), Socially isolated, 65 (3.2 percent), Total, 191 (9.3 percent). Row 6: Total, Not isolated, 1,842 (89.9 percent), Socially isolated, 206 (10.1 percent), Total, 2,048 (100.0 percent).
At age 12, participants with a loneliness score greater than 1 were coded as lonely and participants with a social isolation score greater than 2 were coded as isolated. At age 18, participants who scored higher than 4 on loneliness were classified as lonely and participants with social isolation scores greater than 9 were classified as isolated.
Age 18 outcomes
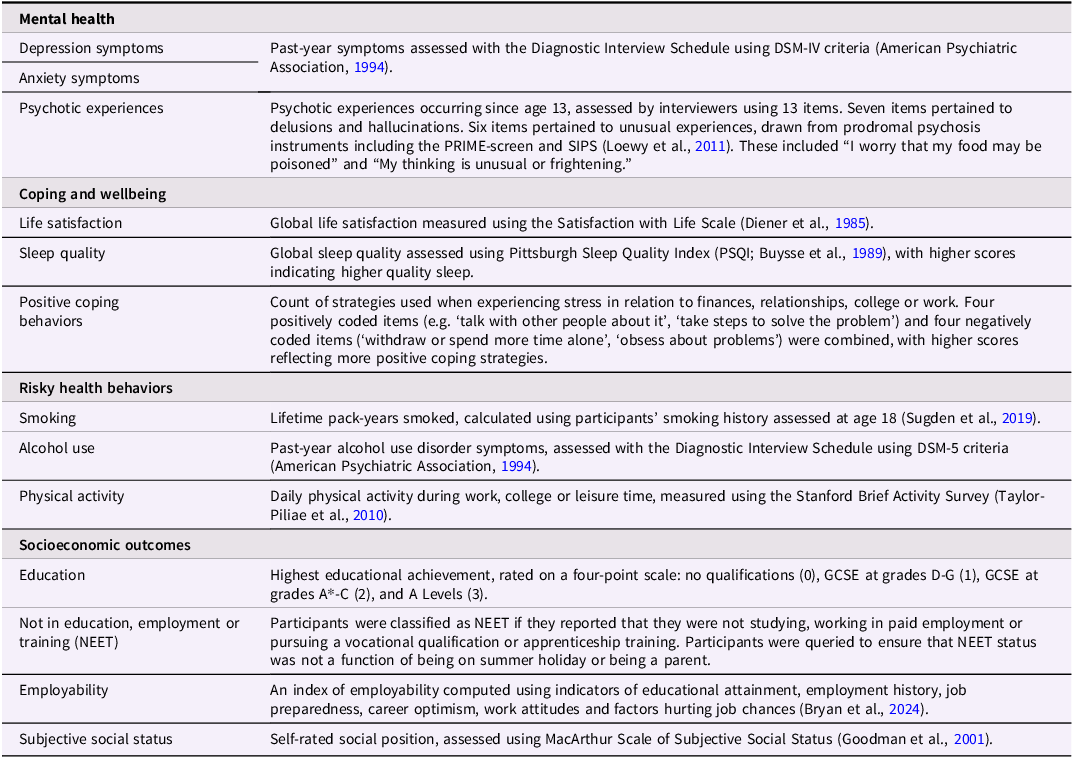
We grouped age-18 outcomes into four domains: mental health, risky health behaviors, coping and functioning and socioeconomic outcomes (see Table 2 for details). Mental health was indicated by depression symptoms, anxiety symptoms and psychotic experiences. Coping and functioning were indicated by life satisfaction, sleep quality and positive coping with stress. The risky health behavior domain included smoking, alcohol use and day-to-day physical activity. Socioeconomic outcomes were indicated by participants’ highest educational achievement, if they were not currently in employment or education (NEET), their employability and subjective social status. Our selection of outcomes was guided by previous research (Matthews et al., Reference Matthews, Danese, Caspi, Fisher, Goldman-Mellor, Kepa, Moffitt, Odgers and Arseneault2019; Thompson et al., Reference Thompson, Odgers, Bryan, Danese, Milne, Strange, Matthews and Arseneault2022).
Summary of mental health, coping and wellbeing, health behavior and socioeconomic outcomes assessed at age 18
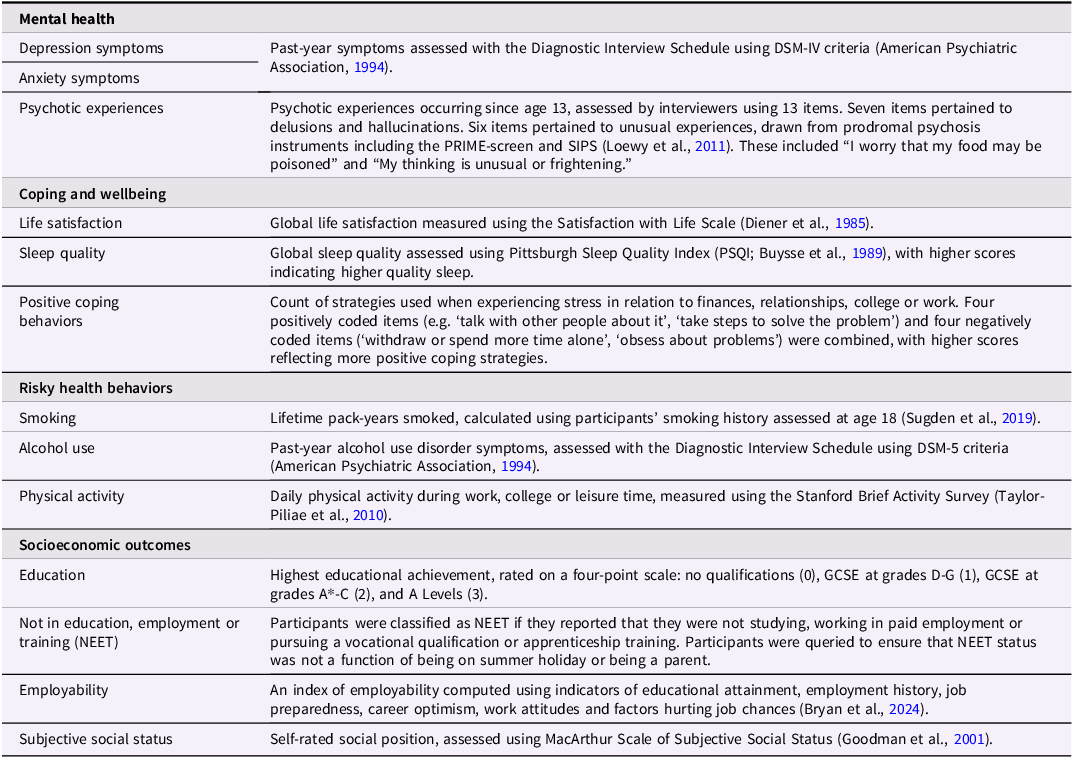
Table 2. Long description
A table summarizing mental health, coping and wellbeing, risky health behaviors, and socioeconomic outcomes assessed at age 18. The table has 15 rows and 2 columns. The first column lists the categories and the second column describes the assessments. Row 1: Mental health. Row 2: Depression symptoms, Past-year symptoms assessed with the Diagnostic Interview Schedule using DSM-IV criteria. Row 3: Anxiety symptoms. Row 4: Psychotic experiences, Psychotic experiences occurring since age 13, assessed by interviewers using 13 items. Seven items pertained to delusions and hallucinations. Six items pertained to unusual experiences, drawn from prodromal psychosis instruments including the PRIME-screen and SIPS. These included ‘I worry that my food may be poisoned’ and ‘My thinking is unusual or frightening.’ Row 5: Coping and wellbeing. Row 6: Life satisfaction, Global life satisfaction measured using the Satisfaction with Life Scale. Row 7: Sleep quality, Global sleep quality assessed using Pittsburgh Sleep Quality Index, with higher scores indicating higher quality sleep. Row 8: Positive coping behaviors, Count of strategies used when experiencing stress in relation to finances, relationships, college or work. Four positively coded items (e.g. ‘talk with other people about it’, ‘take steps to solve the problem’) and four negatively coded items (withdraw or spend more time alone, ‘obsess about problems’) were combined, with higher scores reflecting more positive coping strategies. Row 9: Risky health behaviors. Row 10: Smoking, Lifetime pack-years smoked, calculated using participants’ smoking history assessed at age 18. Row 11: Alcohol use, Past-year alcohol use disorder symptoms, assessed with the Diagnostic Interview Schedule using DSM-5 criteria. Row 12: Physical activity, Daily physical activity during work, college or leisure time, measured using the Stanford Brief Activity Survey. Row 13: Socioeconomic outcomes. Row 14: Education, Highest educational achievement, rated on a four-point scale: no qualifications (0), GCSE at grades D-G (1), GCSE at grades A-C (2), and A Levels (3). Row 15: Not in education, employment or training (NEET), Participants were classified as NEET if they reported that they were not studying, working in paid employment, or pursuing a vocational qualification or apprenticeship training. Participants were queried to ensure that NEET status was not a function of being on summer holiday or being a parent. Row 16: Employability, An index of employability computed using indicators of educational attainment, employment history, job preparedness, career optimism, work attitudes and factors hurting job chances. Row 17: Subjective social status, Self-rated social position, assessed using MacArthur Scale of Subjective Social Status.
Covariates
Age-5 covariate. Parental SES was measured using a standardized composite of household income, parents’ education, and parents’ occupation when participants were aged 5. These variables significantly loaded onto one latent factor, which was then split into tertiles that grouped the sample into low, medium and high parental SES (Trzesniewski et al., Reference Trzesniewski, Moffitt, Caspi, Taylor and Maughan2006).
Age-12 covariates. Childhood mental ill health and personality was indicated by depression symptoms anxiety symptoms and neuroticism. Depression symptoms were measured using participants’ self-report on the Children’s Depression Inventory, with loneliness items removed (Kovacs, Reference Kovacs1992). Anxiety was measured using child self-report using the 10-item Multidimensional Anxiety Scale for Children (MASC; March et al., Reference March, Parker, Sullivan, Stallings and Conners1997). Neuroticism was assessed using an adapted form of the Big Five Inventory completed by interviewers after the home visit (John & Strivastava, Reference John, Strivastava, Pervin and John1999).
Statistical analyses
How are loneliness and social isolation associated with each other from early to late adolescence?
To assess the direction and strength of the associations between loneliness and social isolation across adolescence, we used a cross-lagged panel model (CLPM). This simultaneously estimates the stability of each construct from one time to the next (autoregressive paths), the cross-sectional covariance between the constructs at each timepoint, and the bi-directional effects between the constructs across time (cross-lag paths). This model accounted for both the concurrent associations between loneliness and social isolation at ages 12 and 18, and their stability over time. As the data in the present study had two time points with measures of loneliness and social isolation, more sophisticated analytical techniques such as the random intercept CLPM (Hamaker et al., Reference Hamaker, Kuiper and Grasman2015) were not suitable in this study. We handled missing values using Full Information Maximum Likelihood and accounted for the non-independence of twin observations by using robust standard errors with the vce(cluster) command.
We used chi-square tests to estimate differences in the strength of the cross-sectional, autoregressive and cross-lagged paths. Specifically, we tested for differences in the stability of loneliness and of social isolation across adolescence, for differences in the strength of the cross-sectional associations between loneliness and social isolation at age 12 and at age 18, and for differences in the cross-lagged associations between loneliness and social isolation across adolescence.
Does loneliness buffer or exacerbate the association between earlier social isolation and later isolation?
We investigated the effect of age-12 loneliness and social isolation on age-18 social isolation using two linear regression models planned a priori. We first tested whether age-12 loneliness and social isolation had independent effects on age-18 social isolation, adjusting for parental SES and sex. We then added the interaction between age-12 loneliness and social isolation as a second step to test whether loneliness moderates the association between social isolation at ages 12 and 18. We then investigated the interaction by performing a simple slopes test and plotting the results.
Are loneliness and social isolation independently associated with concurrent and later mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
We tested whether age-12 loneliness and social isolation preceded age-18 outcomes using a series of logistic and linear regression models planned a priori. As a first step, we tested whether age-12 loneliness and social isolation were associated with each outcome in separate univariate models. We then added loneliness and isolation into the same model in step 2 to test whether loneliness and social isolation were independently associated with each outcome. In step 3, we added measures of age-12 depression, anxiety and neuroticism to test whether the effect of loneliness and social isolation on each outcome was accounted for by childhood mental health symptoms and personality.
In step 4, we tested whether age-18 loneliness and social isolation were associated with each outcome in univariate models. In step 5, we combined age-18 loneliness and social isolation into one model to test their independent associations with each outcome. We then added age-12 depression, anxiety and neuroticism to the model as a final step to test whether these associations could be explained by childhood covariates.
Do loneliness and social isolation have a cumulative effect on concurrent and later mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
To test whether age-12 loneliness and social isolation have an additive effect on age-18 mental health, wellbeing, health behaviors and socioeconomic outcomes, we regressed each outcome on a cumulative index of childhood loneliness and social isolation. To test whether age-18 loneliness and social isolation have an additive effect on concurrent outcomes, we similarly regressed each outcome on a cumulative index of age-18 loneliness and isolation. All models adjusted for age-12 mental health symptoms and personality.
Does loneliness exacerbate the association between social isolation and concurrent and later mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
To test whether loneliness moderates the association between childhood social isolation and age-18 outcomes, we regressed each outcome on age-12 loneliness, social isolation and an interaction term combining loneliness and social isolation, adjusting for age-12 mental health and personality. We then tested whether loneliness moderates the concurrent association between age-18 social isolation and age-18 outcomes by regressing each outcome on age-18 loneliness, social isolation and an interaction term combining loneliness and social isolation, adjusting for age-12 covariates. For any significant interactions, we plotted the results and performed a simple slopes test.
All analyses controlled for sex and parental SES. Standard errors were adjusted for clustering of twin observations within families in all models. Analyses were conducted in Stata 18 (StataCorp, 2023). The research questions, hypotheses and analysis plan was pre-registered at https://sites.duke.edu/moffittcaspipr https://github.com/bridgetbryan/loneliness-isolation-interplay and analysis code is available at https://github.com/bridgetbryan/loneliness-isolation-interplay.
Results
Do loneliness and social isolation lead to each other from early to late adolescence?
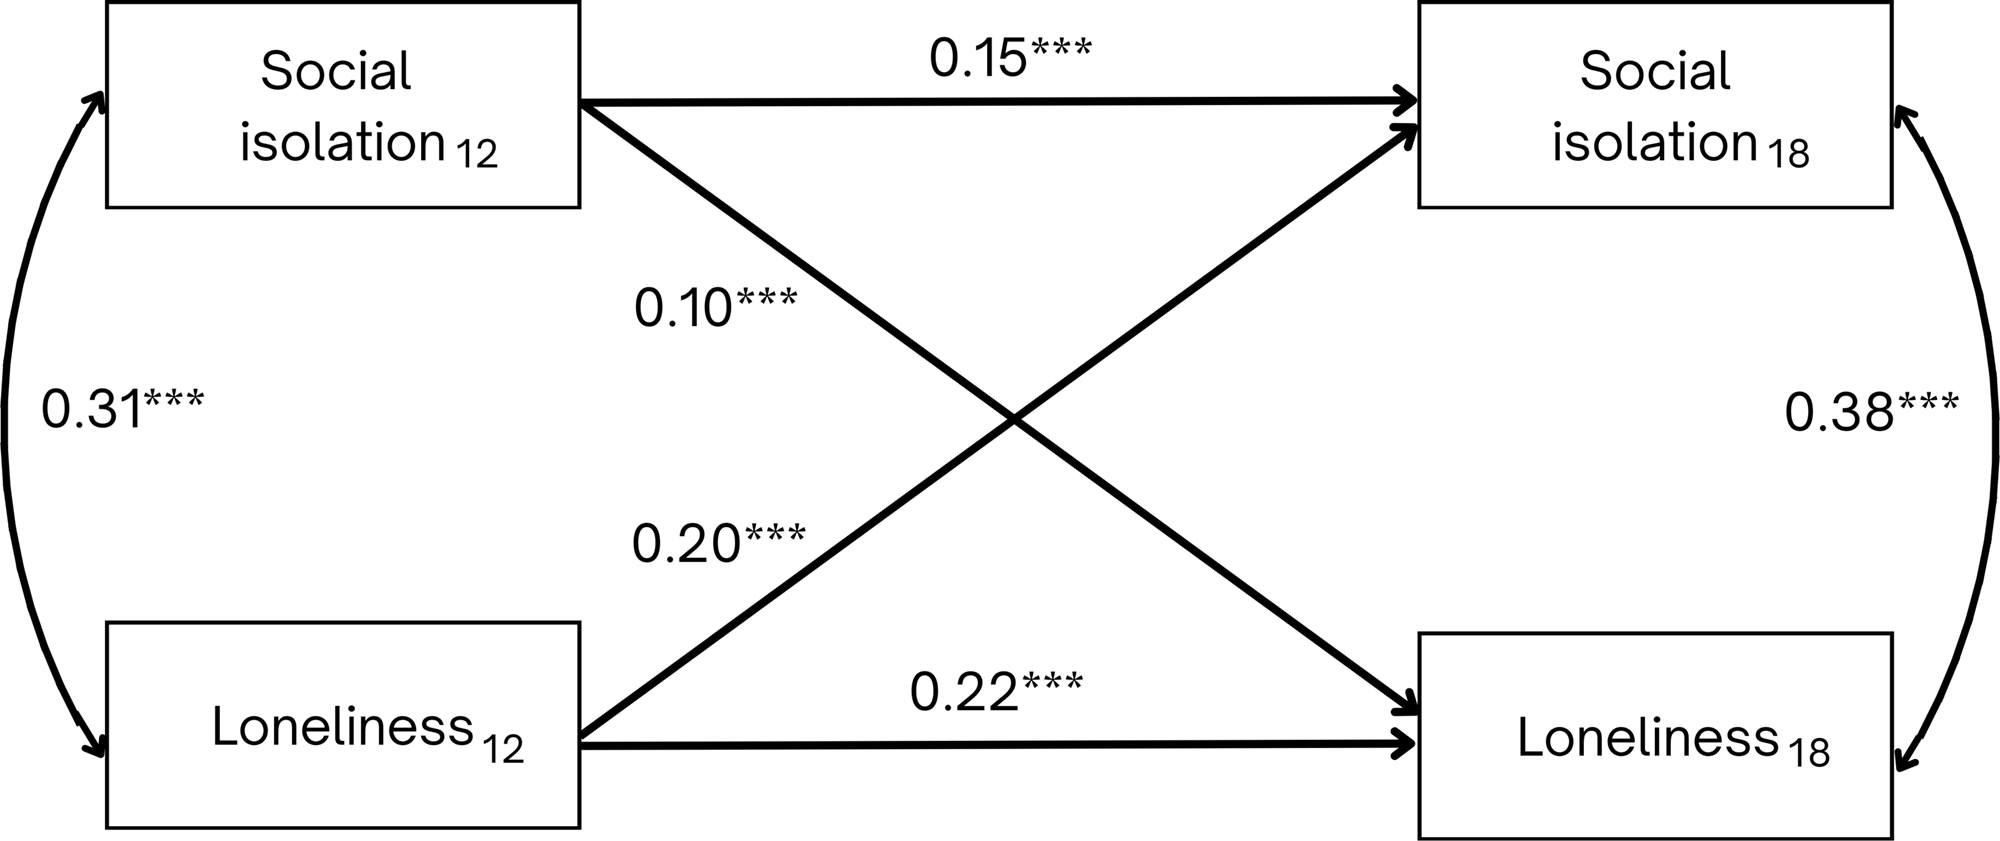
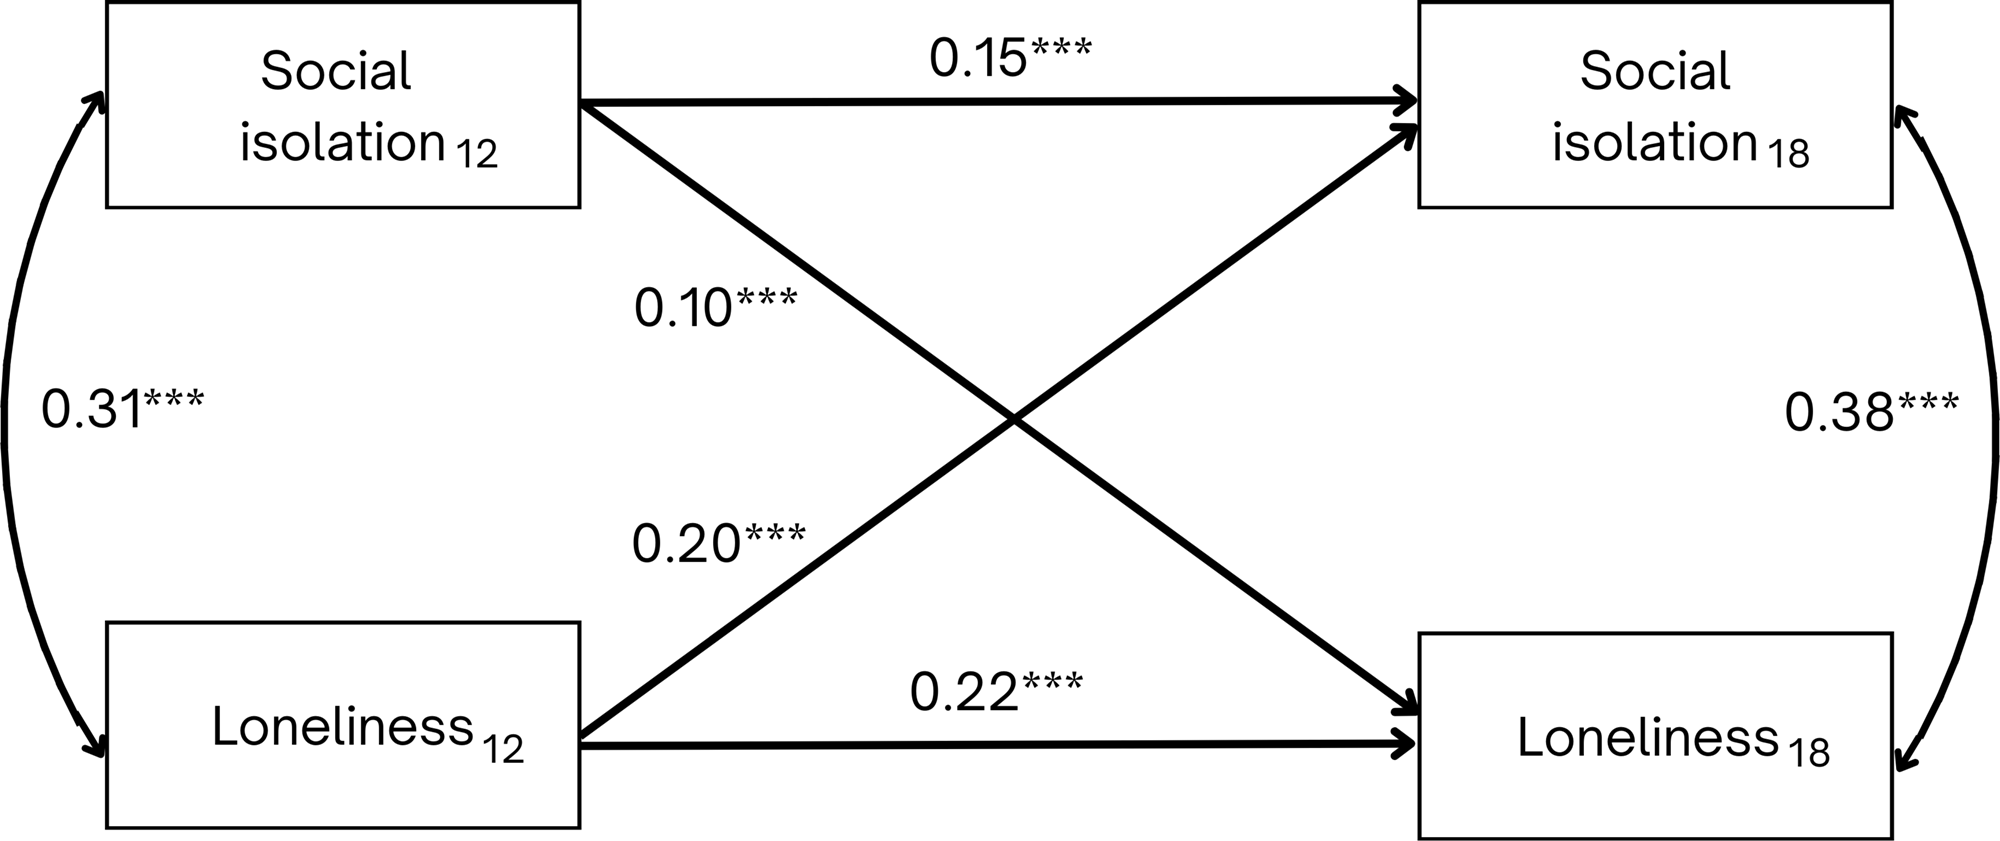
When examining the associations between loneliness and social isolation across ages 12 and 18, we found that the autoregressive effects of loneliness and social isolation were significant and similar in strength (loneliness 12–18 β=0.22, isolation 12–18 β=0.15; χ 2(1) = 2.68, p = 0.10; Figure 1). Loneliness and social isolation were also cross-sectionally associated at both timepoints, with this association stronger at age 18 (r 12 = 0.31, r 18 = 0.38; χ 2(1) = 3.7, p = .05). Consistent with H1, results for the lagged effects show bidirectional associations, with participants who were lonelier in early secondary school going on to be more isolated as they entered young adulthood, and more isolated 12-year-olds reporting higher loneliness as young adults. When examining the strength of the lagged effects, the influence of childhood loneliness on isolation in young adulthood was stronger than the effect of childhood isolation on loneliness in young adulthood (isolation12-loneliness18 β=0.10, loneliness12-isolation18 β=0.20; χ 2(1) = 6.03, p = 0.01). Results did not differ between male and female participants, or between mother or teacher reported social isolation at age 12 (full details in Supplement C).
Cross-lag model for the longitudinal association between loneliness and social isolation across ages 12 and 18. Values on single-headed arrows are standardized partial regression coefficients. Values on double-headed arrows between variables at the same time-point are correlation coefficients. N = 2,195. ***p < .001.
Does loneliness buffer or exacerbate the association between earlier social isolation and later isolation?
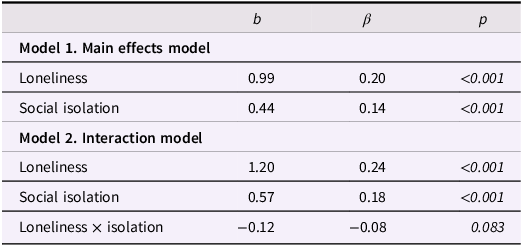
Both loneliness and social isolation experienced at age 12 were associated with increased levels of social isolation 6 years later (Table 3, model 1). The main effect of age-12 social isolation on age-18 isolation did not differ by sex or by mother or teacher report of social isolation at age 12 (Supplement D). The association between loneliness at age 12 and isolation at age 18 was stronger for girls (B = 0.25, p < 0.001) than boys (B = 0.15, p = 0.001).
Associations between age-12 loneliness and social isolation and age-18 social isolation
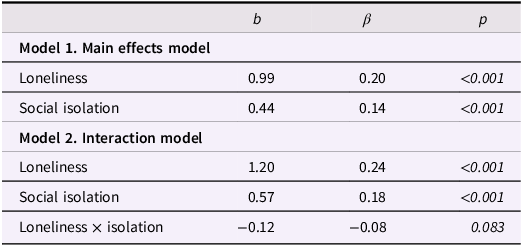
Table 3. Long description
The table presents data on the associations between loneliness and social isolation at age 12 and social isolation at age 18. It has two models: Model 1, Main effects model, and Model 2, Interaction model. Each model includes rows for Loneliness, Social isolation, and Loneliness x isolation. The columns are labeled b, β, and p. Model 1 shows values for Loneliness as b 0.99, β 0.20, p <.001; Social isolation as b 0.44, β 0.14, p <.001. Model 2 shows values for Loneliness as b 1.20, β 0.24, p <.001; Social isolation as b 0.57, β 0.18, p <.001; Loneliness x isolation as b -0.12, β -0.08, p .083.
b indicates unstandardized regression coefficients, β indicates standardized regression coefficients. All models adjust for parental socioeconomic status and sex.
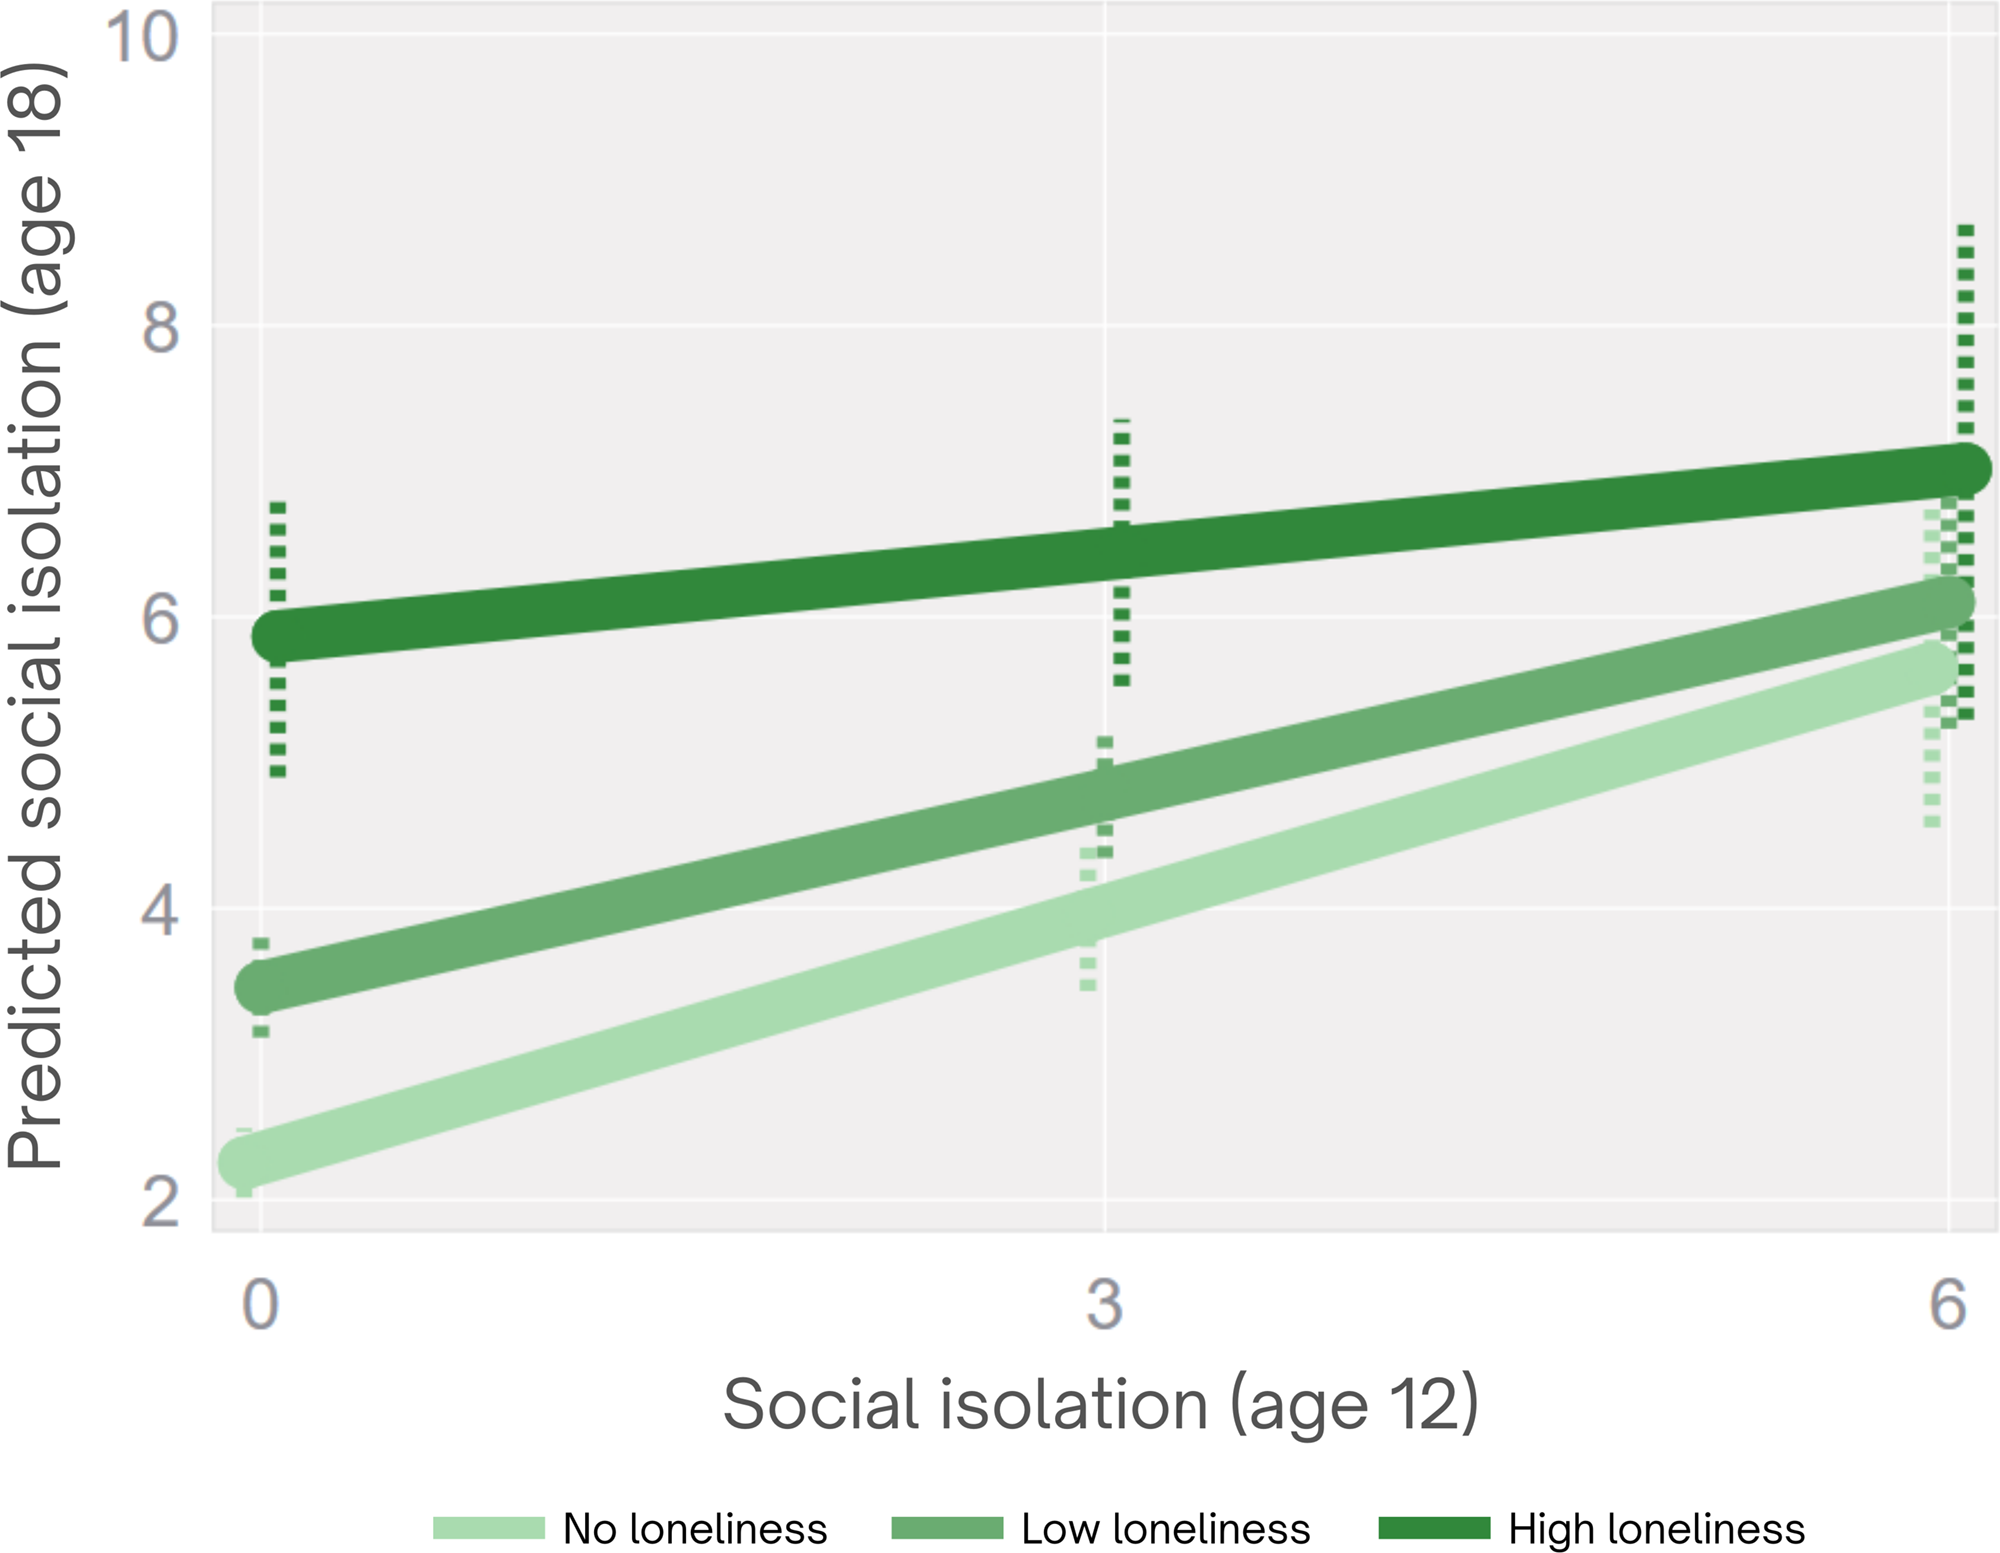
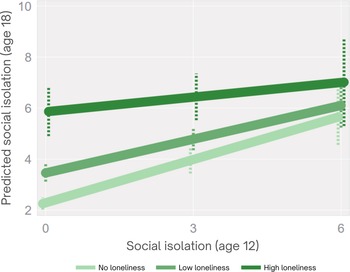
There was marginal evidence for an interaction between age-12 loneliness and social isolation in their effect on age-18 social isolation (Table 3, model 2). The possible moderating effect of loneliness on the association between isolation at ages 12 and 18 is illustrated in Figure 2. Among children who reported no loneliness or low levels of loneliness, greater social isolation at age 12 was associated with greater social isolation at age 18 (no loneliness: b = 0.57, p < 0.001, low loneliness: b = 0.44, p < 0.001). This effect was reduced among children with high loneliness scores, who experienced high levels of social isolation at age 18 no matter their level of isolation at age 12 (b = 0.19, p = 0.29). These findings indicate that, while loneliness does not buffer the association between earlier and later isolation over time, it also does not exacerbate isolation over time, providing partial support for H2.
Associations between age-12 and age-18 social isolation according to age-12 loneliness. For illustrative purposes, at age 12, no loneliness reflects a score of 0, low loneliness represents a score of 1, high loneliness reflects a score of 3. Model adjusts for parental socioeconomic status and sex.
Are loneliness and social isolation independently associated with later and concurrent mental health problems, wellbeing, risky health behaviors and socioeconomic outcomes?
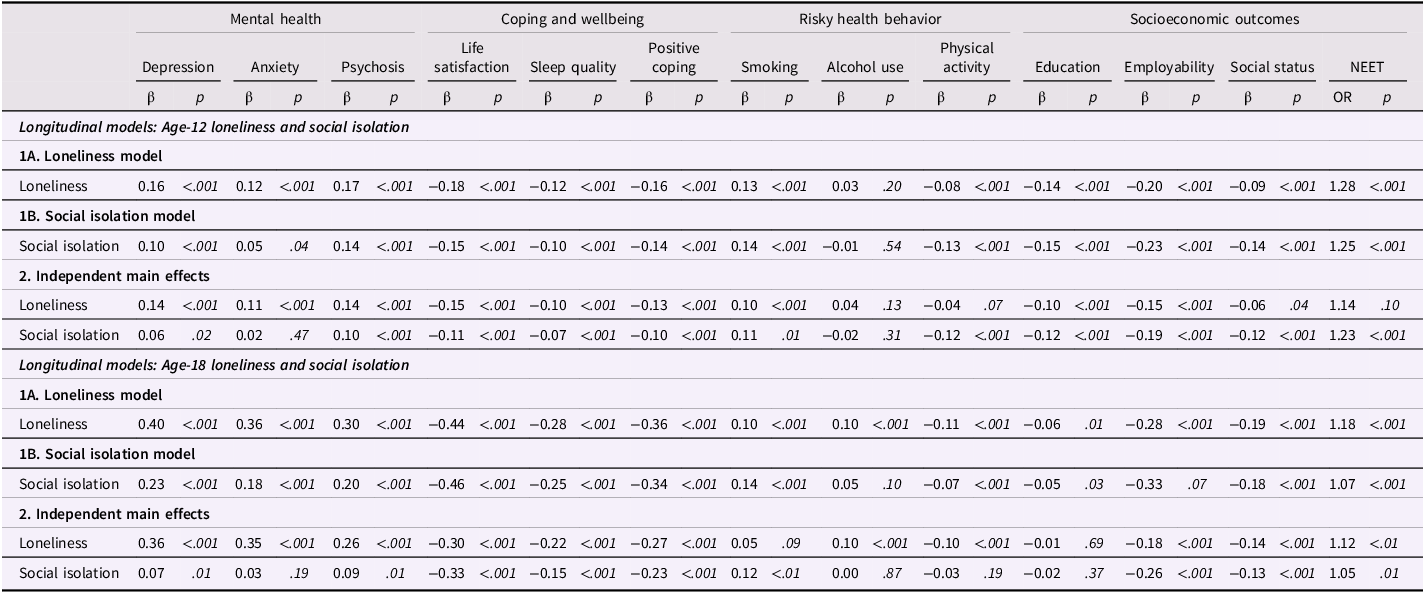
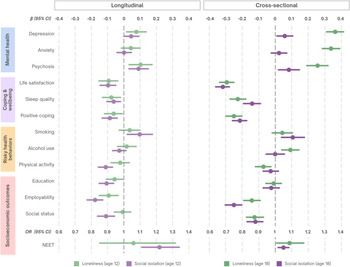
Experiences of loneliness and social isolation in childhood were independently associated with a range of poor outcomes in young adulthood, with lonelier and more isolated 12-year-olds going on to experience poor mental health, worse wellbeing and reduced socioeconomic outcomes at age 18 (Table 4, model 2), consistent with H3. There was partial support for H4: the associations between childhood loneliness, social isolation and most indicators of mental health and wellbeing in young adulthood were robust when adjusting for childhood mental health problems and personality (Figure 3). The associations between childhood social isolation and age-18 depression, and childhood loneliness and later anxiety were accounted for by childhood mental health symptoms and personality. Childhood social isolation was also robustly associated with all young adulthood socioeconomic outcomes; the associations between loneliness and reduced educational achievement and lower employability at age 18 persisted after accounting for earlier mental health symptoms. While childhood social isolation was associated with risky health behaviors at age 18 when accounting for childhood confounders, the association between loneliness and these outcomes were explained by childhood measures.
Hierarchical regression analyses modelling the association between loneliness and social isolation and age-18 outcomes
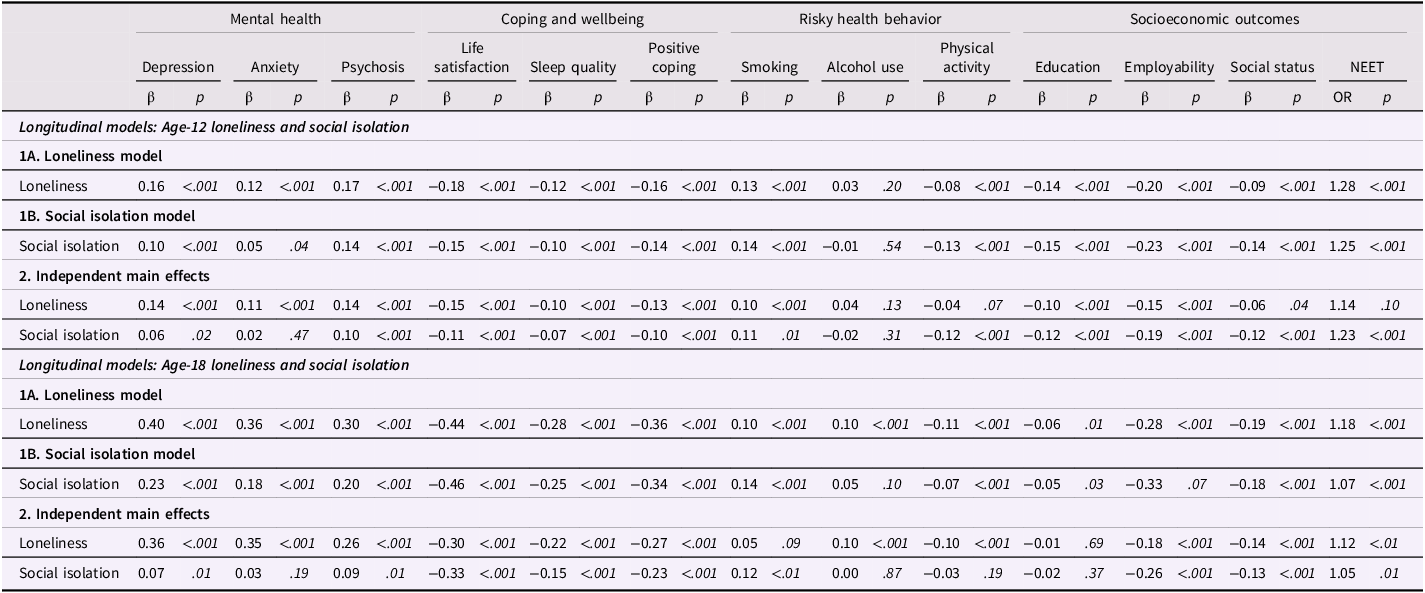
Table 4. Long description
The table presents hierarchical regression analyses modeling the association between loneliness and social isolation at age 12 and various outcomes at age 18. It includes data on mental health, coping and wellbeing, risky health behavior, and socioeconomic outcomes. The table is divided into several sections: longitudinal models for age 12 loneliness and social isolation, loneliness model, social isolation model, and independent main effects. Each section provides beta coefficients and p-values for different variables such as depression, anxiety, psychosis, life satisfaction, sleep quality, positive coping, smoking, alcohol use, physical activity, education, employability, social status, and NEET. The table has multiple rows and columns, with each row representing different models and each column representing different outcomes and their statistical measures.
All models adjust for parental socioeconomic status and sex.
Independent associations between loneliness, social isolation and age-18 outcomes, adjusted for age-12 mental health and personality. Beta estimates and 95% confidence intervals (CI) are shown for all associations aside from not in employment, education or training (NEET) status. For NEET status, odds ratios (OR) and 95% confidence intervals are shown. All models adjust for age-12 mental health, parental socioeconomic status and sex.
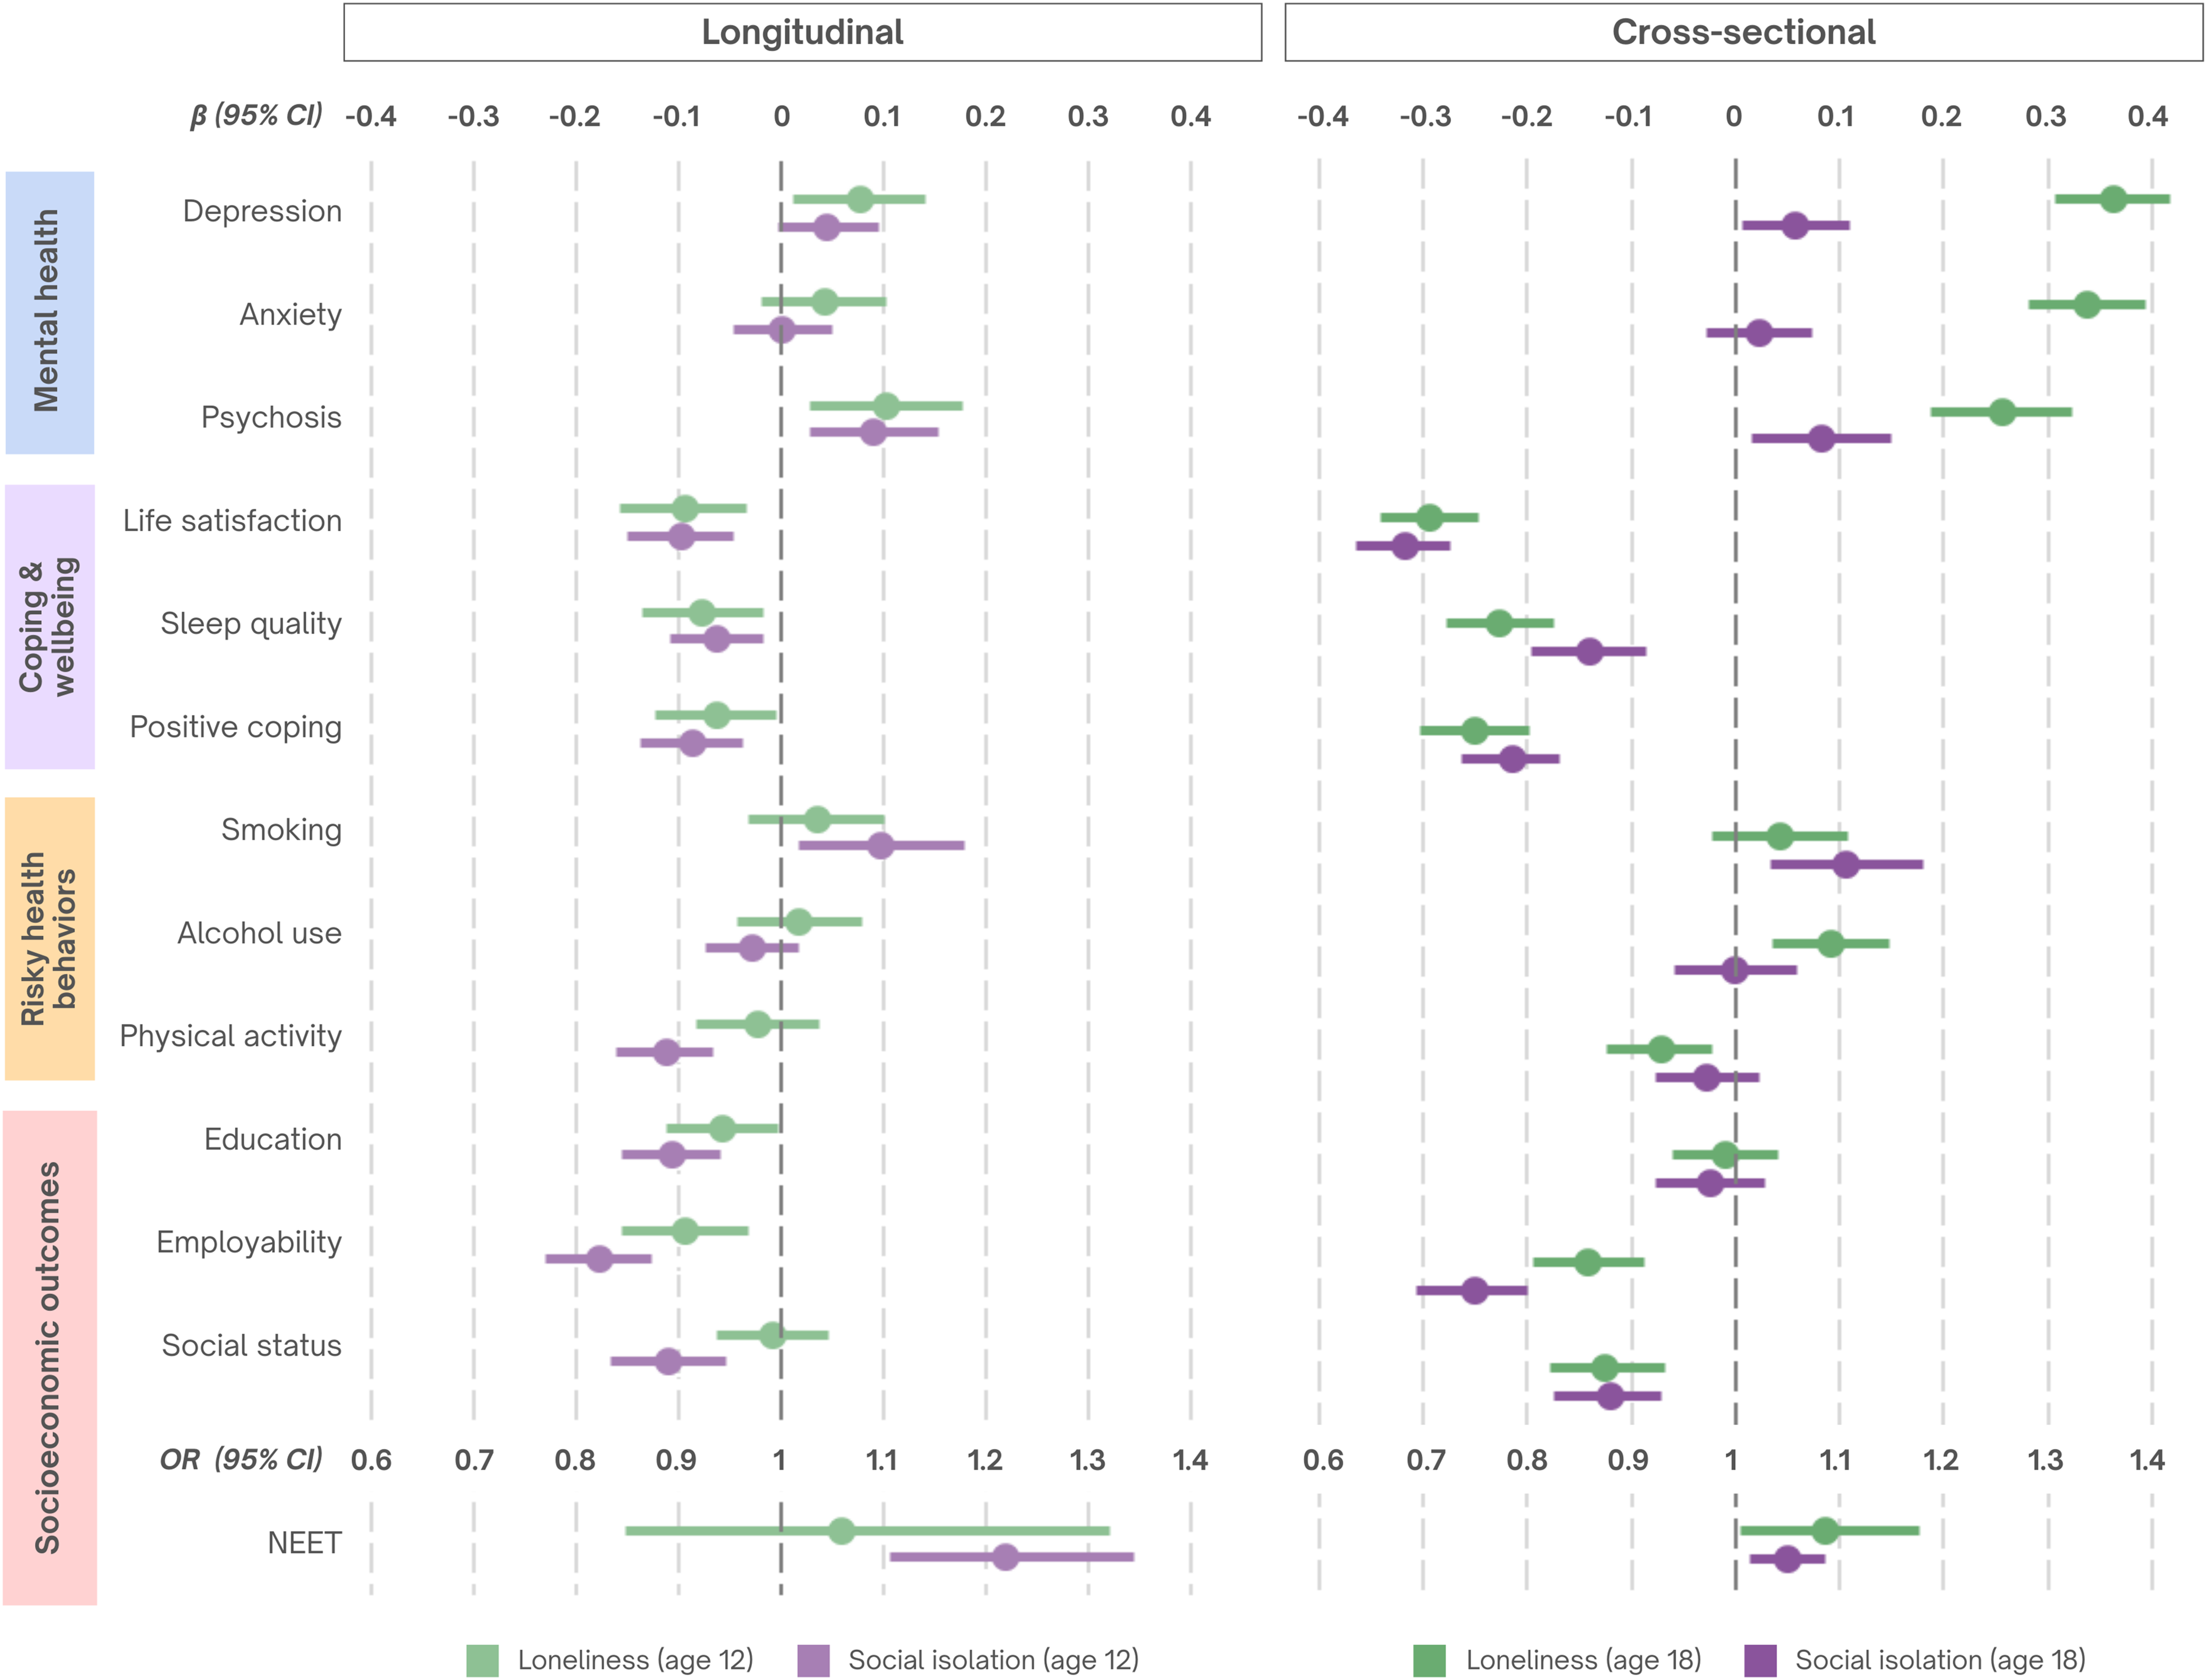
Loneliness and isolation in young adulthood were also independently associated with concurrent mental health difficulties, worse wellbeing and poor socioeconomic outcomes (Table 4, model 4). When adjusting for childhood mental health and personality, lonelier or more isolated young adults concurrently experienced elevated depression symptoms, anxiety symptoms and more psychotic experiences than their less lonely or isolated peers, with loneliness more strongly associated with mental health difficulties than social isolation (Figure 3). Both loneliness and social isolation were similarly associated with all indicators of coping and wellbeing and socioeconomic outcomes, excluding educational attainment (Figure 3). Conversely, loneliness and isolation were not independently associated with risky health behaviors. Loneliness was associated with higher alcohol use and lower physical activity, while social isolation was associated with higher smoking in young adulthood (Figure 3).
Do loneliness and social isolation have a cumulative effect on concurrent and later mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
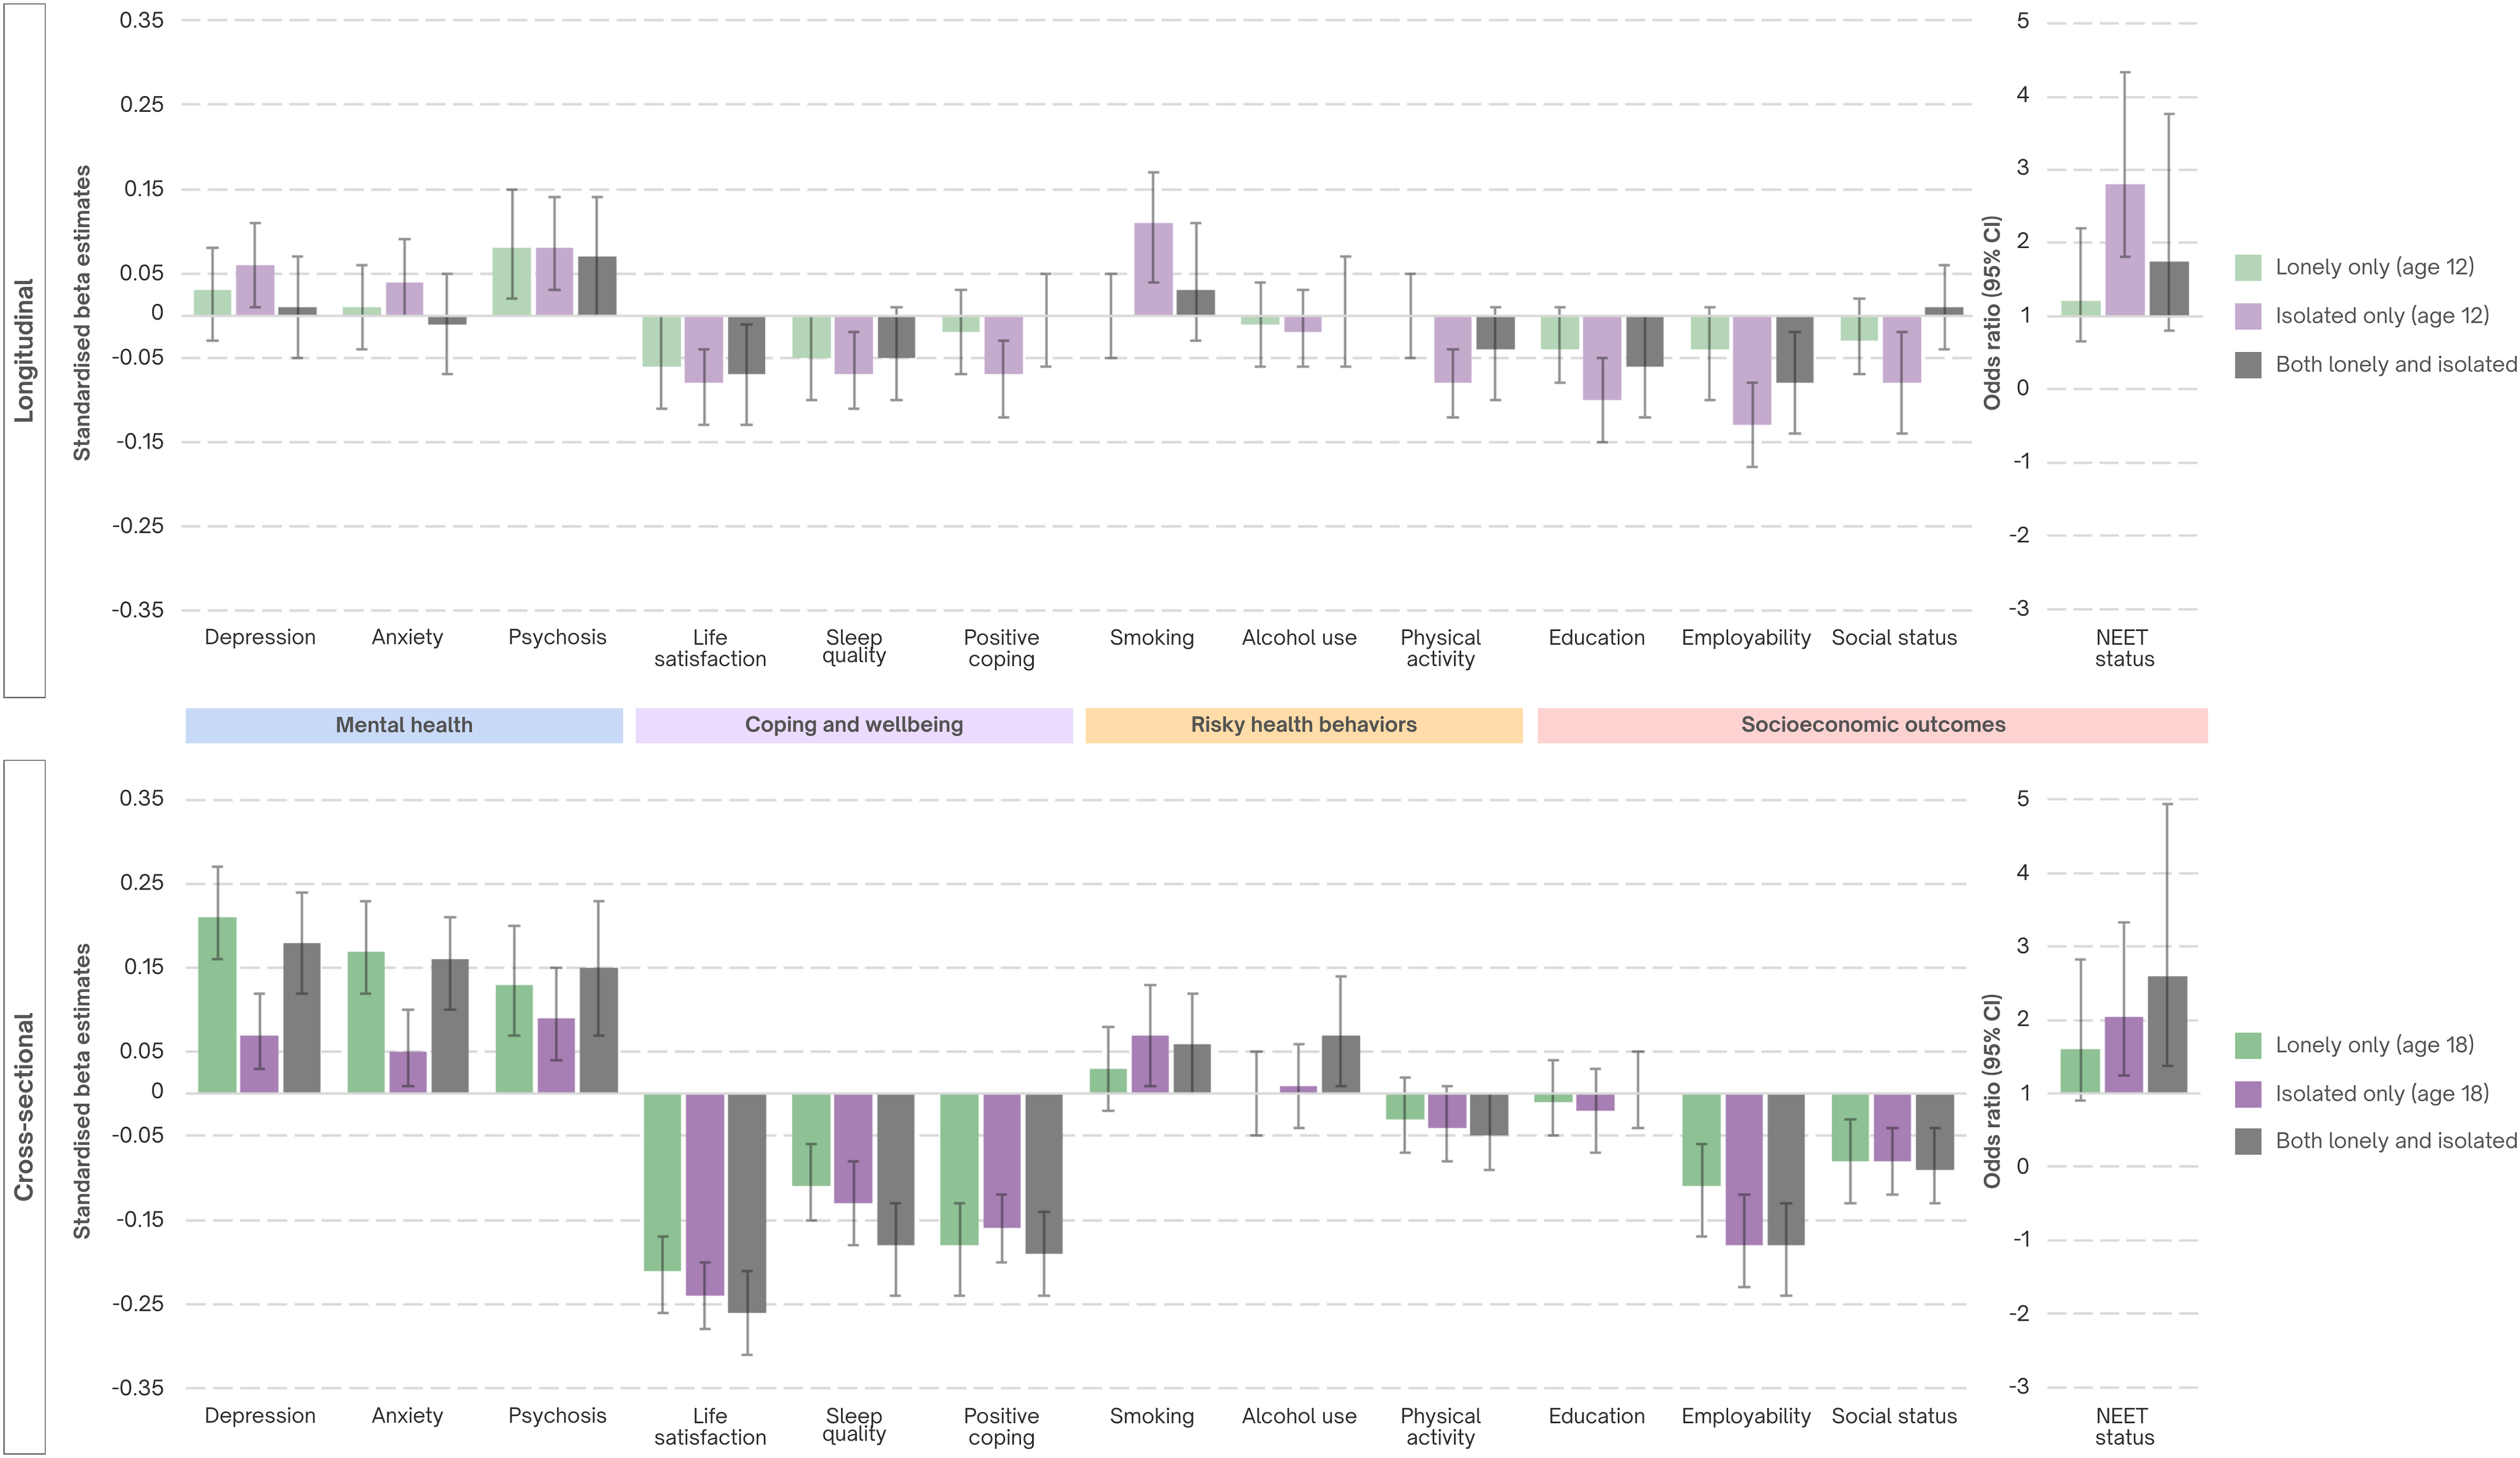
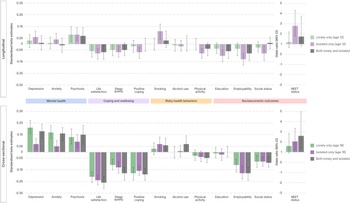
We did not find evidence for a cumulative association between age-12 or age-18 loneliness and social isolation and age-18 outcomes (H5). Compared with young people who did not experience loneliness or social isolation, 18-year-olds who reported high levels of either loneliness or social isolation had elevated mental health symptoms, reduced positive coping and wellbeing and fared poorly on key indicators of young adulthood socioeconomic outcomes (Figure 4). While young people who experienced both loneliness and social isolation had similar poor outcomes, the magnitude of the effect of experiencing both loneliness and isolation on each outcome was not significantly higher than the effect of experiencing only one type of social deficit.
Associations between social isolation and loneliness and mental health, coping and wellbeing, risky health behaviors and socioeconomic outcomes. Beta estimates and 95% confidence intervals (CI) are shown for all associations aside from not in employment, education or training (NEET) status. For NEET status, odds ratios (OR) and 95% confidence intervals are shown. All models compare to the neither lonely nor isolated group. All models adjust for age-12 mental health and personality, parental socioeconomic status and sex.
Does loneliness exacerbate the association between social isolation and concurrent and later mental health problems, coping and wellbeing, risky health behaviors and socioeconomic outcomes?
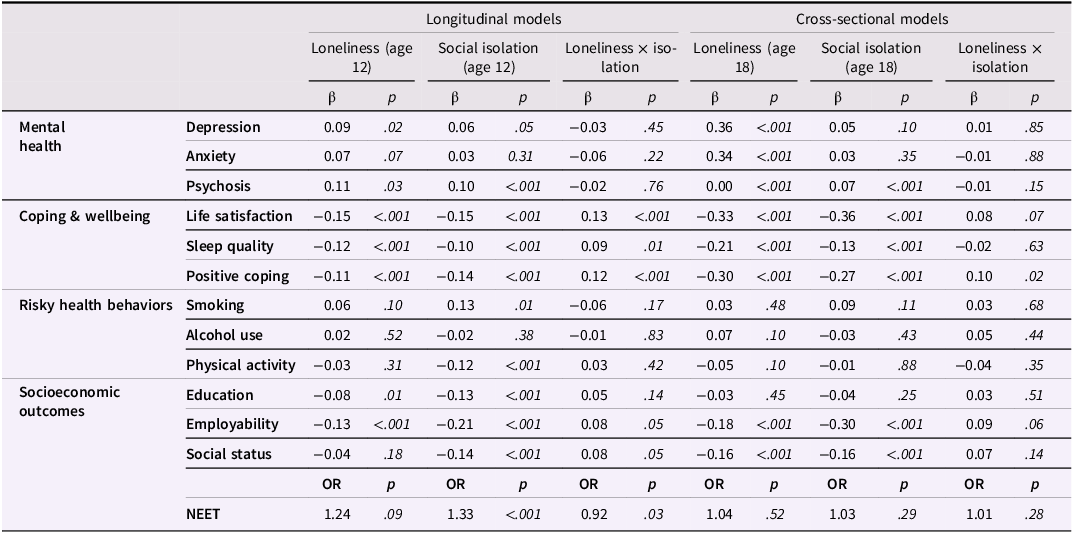
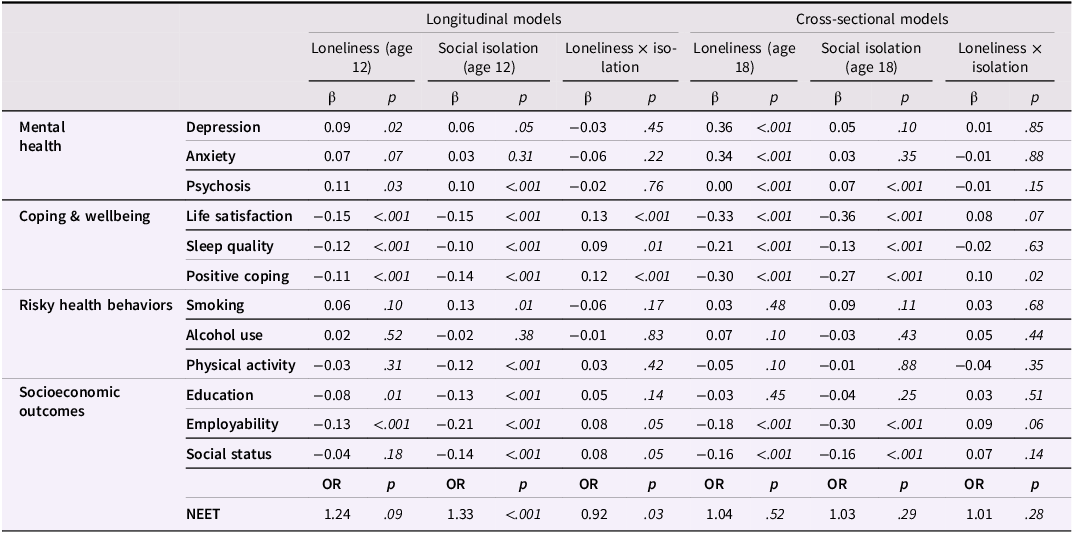
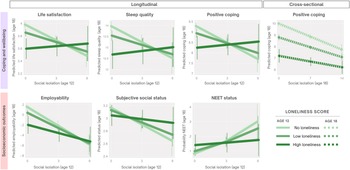
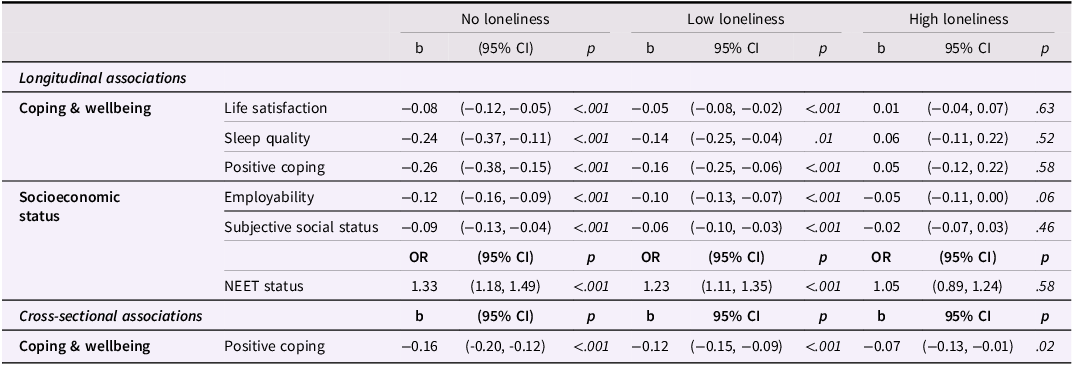
While we found evidence that loneliness moderates the effect of social isolation on indicators of coping and wellbeing and socioeconomic outcomes in young adulthood, we observed a ceiling, or saturation, effect rather than an exacerbation effect (H6). The interaction term combining age-12 loneliness and social isolation predicted age-18 life satisfaction, sleep quality and positive coping, as well as employability, social status and NEET status (Table 5). The interaction terms were not associated with any outcomes in the mental health or health behavior domains (Table 5). Figure 5 illustrates the moderating effect of loneliness on the association between childhood social isolation and young adulthood wellbeing and socioeconomic outcomes. For children who reported no or low levels of loneliness, higher isolation at age 12 was associated with reduced life satisfaction, sleep quality, positive coping behaviors, employability and social status, and increased odds of being NEET as they entered young adulthood (Table 6). Conversely, for children with high levels of loneliness at age 12, social isolation had little impact on these outcomes at age 18, with these children going on to experience poor wellbeing and socioeconomic outcomes no matter their level of isolation at age 12.
Main and interaction effects of loneliness and social isolation on age 18 outcomes
Long description
A table with six rows and eight columns comparing the effects of loneliness and social isolation on various outcomes at ages 12 and 18. The columns are divided into two main categories: Longitudinal models and Cross-sectional models. Each category has three sub-columns: Loneliness (age 12), Social isolation (age 12), and Loneliness x isolation for longitudinal models; Loneliness (age 18), Social isolation (age 18), and Loneliness x isolation for cross-sectional models. Each sub-column contains B and p values. The rows are categorized into Mental health, Coping & wellbeing, Risky health behaviors, and Socioeconomic outcomes, with specific outcomes listed under each category. Row 1: Depression, B values are 0.09, 0.06, -0.03, 0.36, 0.05, 0.01, p values are 0.02, 0.05, 0.45, <.001, 0.10, 0.85. Row 2: Anxiety, B values are 0.07, 0.03, -0.06, 0.34, 0.03, -0.01, p values are 0.07, 0.31, 0.22, <.001, 0.35, 0.88. Row 3: Psychosis, B values are 0.11, 0.10, -0.02, 0.00, 0.07, -0.01, p values are 0.03, <.001, 0.76, <.001, <.001, 0.15. Row 4: Life satisfaction, B values are -0.15, -0.15, 0.13, -0.33, -0.36, 0.08, p values are <.001, <.001, <.001, <.001, <.001, 0.07. Row 5: Sleep quality, B values are -0.12, -0.10, 0.09, -0.21, -0.13, -0.02, p values are <.001, <.001, 0.01, <.001, <.001, 0.63. Row 6: Positive coping, B values are -0.11, -0.14, 0.12, -0.30, -0.27, 0.10, p values are <.001, <.001, <.001, <.001, <.001, 0.023. Row 7: Smoking, B values are 0.06, 0.13, -0.06, 0.03, 0.09, 0.03, p values are 0.10, 0.01, 0.17, 0.48, 0.11, 0.68. Row 8: Alcohol use, B values are 0.02, -0.02, -0.01, 0.07, -0.03, 0.05, p values are 0.52, 0.38, 0.83, 0.10, 0.43, 0.44. Row 9: Physical activity, B values are -0.03, -0.12, 0.03, -0.05, -0.01, -0.04, p values are 0.31, <.001, 0.42, 0.10, 0.88, 0.35. Row 10: Education, B values are -0.08, -0.13, 0.05, -0.03, -0.04, 0.03, p values are 0.01, <.001, 0.14, 0.45, 0.25, 0.51. Row 11: Employability, B values are -0.13, -0.21, 0.08, -0.18, -0.30, 0.09, p values are <.001, <.001, 0.05, <.001, <.001, 0.06. Row 12: Social status, B values are -0.04, -0.14, 0.08, -0.16, -0.16, 0.07, p values are 0.18, <.001, 0.05, <.001, <.001, 0.14. Row 13: NEET, OR values are 1.24, 1.33, 0.92, 1.04, 1.03, 1.01, p values are 0.09, <.001, 0.03, 0.52, 0.29, 0.28.
All models adjust for sex, childhood socioeconomic status and childhood mental health.
Associations between social isolation and coping, wellbeing and socioeconomic outcomes according to loneliness severity. In the longitudinal panel, no loneliness is indicated by a score of 0 at age 12, low loneliness is indicated by a score of 1 and high loneliness by a score of 3 at age 12. In the cross-sectional panel, no loneliness is indicated by a score of 0, low loneliness is indicated by a score of 3 and high loneliness by a loneliness score of 7. NEET indicates not in education, employment or training. All models adjust for age-12 mental health and personality, parental socioeconomic status and sex.
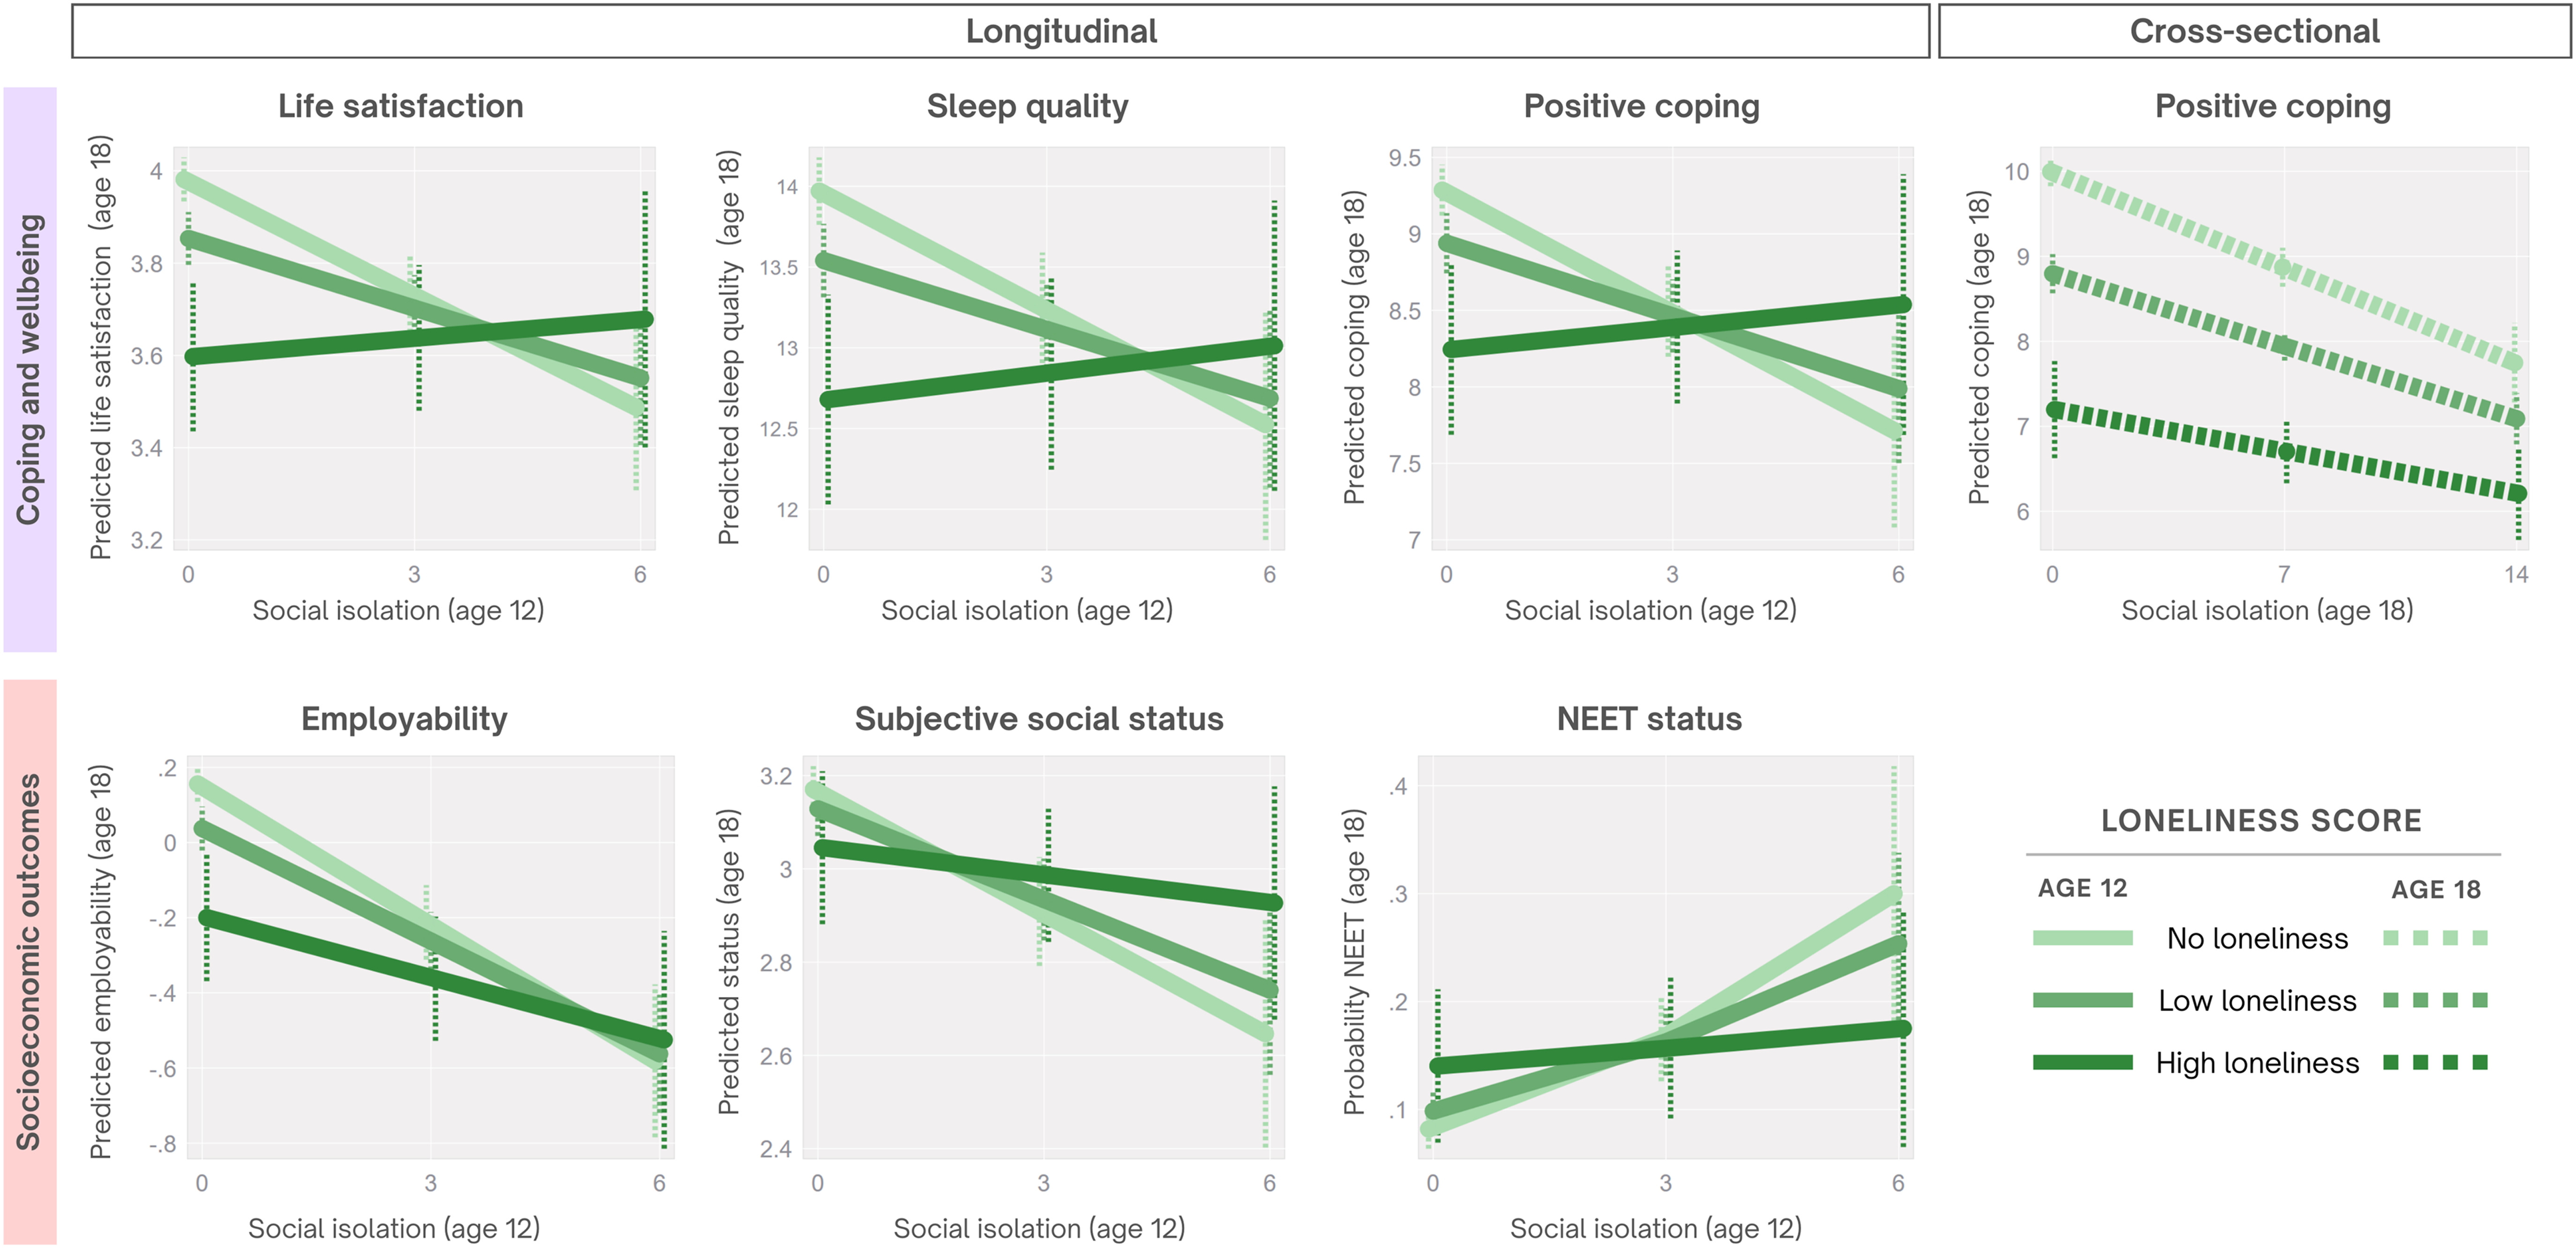
Associations between social isolation and coping and wellbeing and socioeconomic outcomes according to loneliness severity
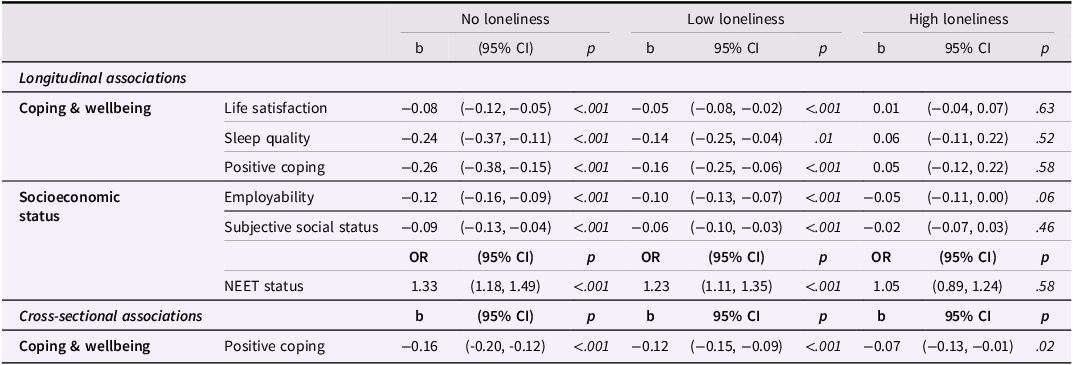
Table 6. Long description
The table presents longitudinal and cross-sectional associations between social isolation and various outcomes based on levels of loneliness: no loneliness, low loneliness, and high loneliness. It has 12 rows and 11 columns. The columns are labeled as follows: No loneliness (b, 95% CI, p), Low loneliness (b, 95% CI, p), and High loneliness (b, 95% CI, p). The rows are grouped into Coping & wellbeing and Socioeconomic status, with specific variables listed under each group. For Coping & wellbeing, the variables are Life satisfaction, Sleep quality, and Positive coping. For Socioeconomic status, the variables are Employability, Subjective social status, and NEET status. The table provides coefficients (b), 95% confidence intervals (CI), and p-values (p) for each variable across the different levels of loneliness. Notable trends include significant negative associations between social isolation and life satisfaction, sleep quality, positive coping, employability, and subjective social status for individuals with no or low loneliness. For those with high loneliness, the associations are generally not significant.
For longitudinal models, no loneliness is indicated by a score of 0, low loneliness is indicated by a score of 1 and high loneliness by a score of 3 at age 12. In the cross-sectional model, no loneliness indicated by a score of 0, low loneliness indicated by a score of 3 and high loneliness by a loneliness score of 7 at age 18.
When investigating concurrent associations between loneliness, isolation and outcomes in young adulthood, we found that the interaction term combining age-18 loneliness and social isolation was significantly associated only with positive coping behaviors (Table 5). Similar to the moderating effects observed in the longitudinal models, the association between social isolation and concurrent coping behaviors is weaker among the loneliest young people, who reported less positive coping behaviors than their less lonely peers whether they were isolated or not (Figure 5, Table 6).
Sensitivity analyses
To test whether findings were the product of using an arbitrary cutoff score to create the groups, we conducted analyses using an alternative top 25% cut off. The results were consistent with the main findings (Supplement E). We also conducted sensitivity analyses using the age-12 social isolation measure with the “complains of loneliness” item excluded. The results were also consistent with the main findings (Supplement F), indicating that the inclusion of this item does not meaningfully influence the observed associations.
Discussion
Although there is growing concern about the corrosive effects of loneliness and social isolation for health and wellbeing, few studies have directly investigated their interplay over time or how they work together to shape outcomes. Our findings indicate that loneliness and social isolation are independently and positively associated with each other over time. In particular, our results show that loneliness experienced in the context of social isolation is not reliably associated with long-term social reconnection, raising questions about the degree to which loneliness can be understood to play a positive role in driving social repair. Beyond the associations between loneliness and social isolation, our findings highlight their long-lasting implications for a range of outcomes, although experiencing both social deficits together does not appear to lead to a cumulatively greater impact on these outcomes. Altogether, our findings underline the pervasive and enduring effects of early loneliness and social isolation and raise questions about whether loneliness plays an adaptive role in driving social reconnection. These findings highlight the importance of addressing loneliness early in life to prevent cycles of disconnection, health problems and socioeconomic difficulties becoming entrenched.
The evolutionary theory of loneliness hypothesizes that loneliness drives socially isolated individuals to repair or rebuild their social connections and, as a result, buffers the persistence of social isolation over time (Cacioppo & Cacioppo, Reference Cacioppo, Cacioppo and Olson2018). Our findings do not support this buffering hypothesis, instead indicating that socially isolated children who experience loneliness go on to have high levels of social isolation as they enter young adulthood, similar to children who did not experience loneliness. This echoes emerging evidence from aging adults for whom increased loneliness is not consistently associated with long term social repair (Chang et al., Reference Chang, Chen, Xi, Wang and Chu2025; Das, Reference Das2021; Pan, Reference Pan2024). Our findings were similar when considering moderate and high levels of childhood loneliness, casting doubt about the assertion that milder loneliness is more likely to be ‘adaptive’ and prompt social reaffiliation than more severe loneliness (Hussain & Palmer, Reference Hussain and Palmer2024). Together, these results raise questions about the degree to which loneliness can be held to have an adaptive function in driving increased social connection.
The discrepancy between our findings and evolutionary understandings of loneliness may stem from failures in loneliness-induced motivation to reconnect (Qualter et al., Reference Qualter, Vanhalst, Harris, Van Roekel, Lodder, Bangee, Maes and Verhagen2015) translating into successful reconnection in the long term. The desire to reconnect may not consistently lead to connection-seeking behavior, with lonely individuals often withdrawing from social interactions (Cacioppo & Hawkley, Reference Cacioppo and Hawkley2009; Gardner et al., Reference Gardner, Pickett, Jefferis and Knowles2005) or dealing with feelings of loneliness by developing independence and self-reliance (Besevegis & Galanaki, Reference Besevegis and Galanaki2010). Alternatively, lonely individuals may actively attempt to rekindle or forge new relationships, but the social difficulties and social anxiety associated with loneliness (Knowles et al., Reference Knowles, Lucas, Baumeister and Gardner2015; Maes et al., Reference Maes, Nelemans, Danneel, Fernández-Castilla, Van den Noortgate, Goossens and Vanhalst2019) may render these attempts unsuccessful. Additionally, for lonely individuals who successfully reconnect with others, mental health and other difficulties that co-occur with loneliness may act as barriers to maintaining positive and satisfying relationships in the long-term. Within this context, loneliness may indeed play a role in providing motivation for isolated individuals to connect with others, but additional factors such as social skills, traits and circumstances could determine whether an isolated individual reconnects with others or stays isolated long-term. Research using long-term longitudinal data with more granular assessment of loneliness and social isolation across adolescence, as well as qualitative exploration of lonely people’s motivations, strategies and barriers to connection is needed to improve our understanding of the pathways through which loneliness impacts long term social connections.
Our findings also underline the wide-ranging negative consequences of loneliness and social isolation for health, wellbeing and socioeconomic position in adolescence and young adulthood. Our study builds on research that demonstrates associations between loneliness or social isolation on health and functional outcomes (Bryan et al., Reference Bryan, Thompson, Goldman-Mellor, Moffitt, Odgers, So, Rahman, Wertz, Matthews and Arseneault2024; Leigh-Hunt et al., Reference Leigh-Hunt, Bagguley, Bash, Turner, Turnbull, Valtorta and Caan2017; Thompson et al., Reference Thompson, Odgers, Bryan, Danese, Milne, Strange, Matthews and Arseneault2022) by showing that, when considered together, both loneliness and social isolation in early adolescence are prospectively and independently associated with multiple indicators of poor mental health, wellbeing and socioeconomic outcomes at the cusp of young adulthood. Partially consistent with H4, while some of these associations were robust when accounting for childhood mental health and personality, the associations between social isolation and later mental health and loneliness and educational attainment were explained by these childhood experiences, suggesting that the pathways linking loneliness and social isolation to later outcomes may differ across social deficits and life domains. The pattern of associations between loneliness, isolation, and concurrent and later outcomes also varied, with childhood social isolation particularly strongly associated with subsequent poor socioeconomic outcomes, and loneliness in young adulthood consistently co-occurring with mental health symptoms. This variation in the patterns of associations between these social deficits and young adulthood outcomes underlines the importance of understanding loneliness and isolation as different but linked phenomena and considering how they shape outcomes when experienced during different developmental periods. Within this context, research and interventions aiming to understand and mitigate the negative consequences of loneliness and social isolation must not treat these phenomena as interchangeable but consider how they work together, as well as separately, to impact outcomes.
In addition to their distinct contributions, our findings indicate that loneliness and social isolation jointly influence health, wellbeing, and socioeconomic outcomes in a non-additive manner, potentially exhibiting a ceiling or saturation effect. We observe that isolated and lonely individuals experience similar difficulties to those who experienced only one type of social deficit. We also found that that the negative impact of isolation on wellbeing and socioeconomic outcomes is strongest in the absence of loneliness and plateaus for individuals who experience high levels of loneliness. This potential ceiling effect may be explained by the substantial impacts of both loneliness and isolation on health, wellbeing and socioeconomic outcomes, such that there is little room to capture additional effects when both are experienced together. Alternatively, isolation and loneliness may impact these outcomes through similar pathways such that some of their effects overlap and do not accumulate linearly. The finding that the impact of loneliness and isolation on outcomes are non-additive in adolescence and young adulthood diverge from some existing evidence of cumulative effects on health in late adulthood (Barnes et al., Reference Barnes, MacLeod, Tkatch, Ahuja, Albright, Schaeffer and Yeh2021; Shimada et al., Reference Shimada, Doi, Tsutsumimoto, Makino, Harada, Tomida, Morikawa and Arai2025), suggesting that the pathways through which they shape outcomes may vary across the life course. Longitudinal research considering the developmental and social complexities of loneliness and social isolation and drawing on data from across adulthood could enhance our understanding of how loneliness and isolation shape outcomes across the life span.
Strengths and limitations
The use of repeated, prospective assessments of loneliness and social isolation across adolescence is an important strength of this study. While these data allowed us to test key questions about the interplay of loneliness and social isolation across time, the assessment of these constructs at only two timepoints and with a six-year time lag has some important limitations, however. Firstly, while an important assertion of evolutionary theories of loneliness is that less severe, short-term episodes of loneliness are most likely to be ‘adaptive’ and lead to improved social connection, it was not possible to differentiate between the effects of transient and persistent loneliness on young adulthood outcomes. As such, we could not test this aspect of the theory, although we found that less severe loneliness did not buffer the effect of social isolation over time. Future research with granular assessment of loneliness and social isolation, including multiple assessments across adolescence or more intensive hourly or daily assessment, could build on our findings by investigating how both the persistence and severity of episodes of loneliness shape social connections long-term.
Secondly, the use of two measurement waves spanning multiple developmental periods introduces several considerations for the interpretation of the CLPM findings. First, although best practice recommends the use of identical measures across time (Cole & Maxwell, Reference Cole and Maxwell2003), this was not possible given that the study spans multiple developmental stages. As such, we used age-appropriate measures of loneliness and social isolation in childhood and late adolescence whose similar associations with key correlates at both time points support their consistency as indicators of these constructs across development (Table S1). Second, the six-year interval between timepoints and the lower internal consistency of the age-12 loneliness measure may have attenuated the associations observed in the CLPM. However, the persistence of associations across this period suggests that these relationships are robust over time. Third, we employed a traditional CLPM, which allows estimation of cross-sectional, auto-regressive, and cross-lagged associations with two waves of data but does not distinguish within-person dynamics from stable between-person differences (Hamaker, Reference Hamaker2023). As such, the observed associations likely reflect a combination of trait-like differences and changes in loneliness and social isolation over time. Future research with at least three waves of data using the same measures could apply more advanced approaches, such as the random intercept CLPM (Hamaker et al., Reference Hamaker, Kuiper and Grasman2015), to better disentangle these processes
Our findings should also be interpreted in light of the study’s focus on childhood and adolescence. We used measures of social isolation that capture low embeddedness within age-appropriate social networks, which is consistent with prior research that conceptualizes childhood isolation in terms of peer relationships (e.g., Lacey et al., Reference Lacey, Kumari and Bartley2014; Matthews et al., Reference Matthews, Danese, Wertz, Odgers, Ambler, Moffitt and Arseneault2016; Morneau-Vaillancourt et al., Reference Morneau-Vaillancourt, Oginni, Assary, Krebs, Thompson, Palaiologou, Lockhart, Arseneault and Eley2023; Thompson et al., Reference Thompson, Agnew-Blais, Allegrini, Bryan, Danese, Odgers, Matthews and Arseneault2023). These measures differ from commonly used indicators of social isolation in adulthood, such as living alone or participation in community activities, which are not appropriate for younger populations. Within this context, differences between our findings in children and adolescents and previous findings in older populations may reflect differences in how loneliness and isolation shape health and functional outcomes in different developmental stages, as well as differences in how these constructs were measured across life.
Additionally, as the age 18 indicator of social isolation was based on participants’ self-reported access to supportive relationships, it captured both the availability of social ties and participants’ perceptions of those ties, which may introduce some overlap with loneliness. This may be reflected in the cross-sectional association between the constructs at age 18 (r = 0.38), which is comparable but somewhat stronger than that observed in studies using structural indicators of social isolation in adulthood (e.g., r ≈ 0.18–0.30; Preacher et al., Reference Preacher, Rucker, MacCallum and Nicewander2005; Coyle & Dugan, Reference Coyle and Dugan2012; Steptoe et al., Reference Steptoe, Shankar, Demakakos and Wardle2013). Nevertheless, there is evidence that the measures capture related but distinct constructs. The items in the two measures capture different dimensions of social connection: the social isolation items assess the availability of support from family, friends, and close others (e.g., “I have friends with whom I can share my joys and sorrows,” “My family really tries to help me”), whereas the loneliness items focus on subjective experiences and feelings about disconnection (e.g., “How often do you feel alone?” “How often do you feel left out?”). Consistent with this, the pattern of associations with other outcomes also differed between loneliness and social isolation, with loneliness more strongly related to mental health and alcohol use, and social isolation more strongly related to socioeconomic outcomes such as employability, further suggesting that the constructs are related but not interchangeable. Future research using existing or new instruments that capture other dimensions of social isolation in adolescence, including the number and quality of friendships and the frequency of social interactions with peers, such as the CIassmates Social Isolation Questionnaire (Alivernini & Manganelli, Reference Alivernini and Manganelli2016) or the Social Isolation Questionnaire (dos Santos et al., Reference dos Santos, Soares, Gaoua, Rangel Junior, Lima and de Barros2024), would add depth to our understanding of the role of social isolation in shaping loneliness, health and functional outcomes.
Similarly, the measures of loneliness and social isolation in early adolescence were not designed to assess these constructs but were constructed using items from broader instruments designed to screen for emotional and behavioral problems. Nevertheless, the scales demonstrate good content validity, with the social isolation items drawn from the CBCL (Achenbach, Reference Achenbach1991a) capturing reductions in social engagement that may reflect either social withdrawal or peer rejection. Similarly, the loneliness items closely parallel those included in the children’s loneliness scale, which is widely regarded as the gold-standard measure of loneliness in children and young adolescents (Maes et al., Reference Maes, Van den Noortgate, Vanhalst, Beyers and Goossens2017). These items have also been used to assess loneliness and social isolation in several previous studies in this cohort (e.g. Bryan et al., Reference Bryan, Thompson, Goldman-Mellor, Moffitt, Odgers, So, Rahman, Wertz, Matthews and Arseneault2024; Matthews et al., Reference Matthews, Caspi, Danese, Fisher, Moffitt and Arseneault2022; Thompson et al., Reference Thompson, Agnew-Blais, Allegrini, Bryan, Danese, Odgers, Matthews and Arseneault2023), supporting the comparison of the present findings to earlier work
Additionally, as loneliness and social isolation both exist on a continuum and there is no consensus on how best to define whether an individual is lonely versus not lonely, or isolated versus not isolated, we have treated both constructs as continuous wherever possible. We used a top 10% cutoff to construct a cumulative measure of loneliness and social isolation, which reflects the proportion of adolescents who report feeling lonely often (ONS, 2018) and aligns with previous research in this cohort (Matthews et al., Reference Matthews, Qualter, Bryan, Caspi, Danese, Moffitt, Odgers, Strange and Arseneault2023). Sensitivity analyses indicate that findings are largely consistent using a lower cutoff (25%). Nevertheless, this ‘extreme groups’ approach has statistical limitations, and the results should be interpreted in the context of the underlying continuous distributions (Preacher et al., Reference Preacher, Rucker, MacCallum and Nicewander2005).
Finally, our findings from a sample of twins may not generalize to singletons. All participants in this study had a sibling of the same age, which may shape experiences of both loneliness and social isolation in childhood and adolescence and influence estimates of the associations between loneliness, social isolation and later outcomes. However, the extent to which being a twin protects against isolation and loneliness is not well established. In fact, there may be experiences associated with being a twin that could increase isolation and loneliness, such as being treated as part of a pair rather than as an individual or being left out by peers because of assumptions that twins can rely on each other for company. Indeed, the prevalence of loneliness in our twin sample is comparable to that in other samples of singletons (ONS, 2018).
Implications
Our findings point to a need for careful consideration of whether loneliness can be considered to play a positive role in promoting social reconnection when experienced in the context of social isolation, raising questions about assumptions regarding the role of loneliness in driving social connection that are commonly referenced in the literature on loneliness and social isolation. Some refinement of dominant theories of loneliness could be needed to more comprehensively explain the discrepancy between the well-documented motivation to reconnect that loneliness can provide (Besevegis & Galanaki, Reference Besevegis and Galanaki2010; McKenna-Plumley et al., Reference McKenna-Plumley, Turner, Yang and Groarke2023; Qualter et al., Reference Qualter, Verity, Walibhai, Fuhrmann, Riddleston, Alam, Conway and Lau2025; Schoenmakers et al., Reference Schoenmakers, van Tilburg and Fokkema2012) and our findings that this does not translate into reconnection in early life. Research utilizing longitudinal data with repeated, age-appropriate assessment of social isolation and loneliness will be essential to inform such theoretical developments and improve our understanding of how loneliness and social isolation are related across time and across the life course.
Our findings also highlight the potential for interventions to prevent and address loneliness and social isolation early in life to benefit individuals’ later health, wellbeing and life chances. The longitudinal associations between loneliness, social isolation and a range of health, wellbeing and socioeconomic difficulties point to these social deficits as markers of increased risk for poor outcomes rather than adaptive responses that could promote social reconnection. In particular, the interconnection between loneliness and isolation and their non-additive effect on outcomes suggest that holistic strategies that address isolation and loneliness together will be necessary to prevent and disrupt cycles of loneliness and social isolation and limit their consequences for health and functioning. Interventions that target the potential barriers to reconnection, such as difficulties utilizing social skills (Knowles et al., Reference Knowles, Lucas, Baumeister and Gardner2015) or social anxiety and hypervigilance (Cacioppo & Hawkley, Reference Cacioppo and Hawkley2009; Maes et al., Reference Maes, Nelemans, Danneel, Fernández-Castilla, Van den Noortgate, Goossens and Vanhalst2019) may most effectively support lonely and isolated young people to build supportive and satisfying relationships with others. Additionally, integrating long-term assessment of mental health and socioeconomic outcomes in trials of social connection interventions could further clarify whether reducing loneliness and isolation leads to improvements in later health, wellbeing, and socioeconomic outcomes.
Further, our findings also underline the economic imperative for combatting loneliness and isolation for policymakers. Experiences of loneliness and social isolation in early adolescence were independently and robustly associated with reduced socioeconomic outcomes in young adulthood, with social isolation associated with later unemployment in a magnitude similar to established risk factors including childhood socioeconomic disadvantage and mental health difficulties (Rahmani et al., Reference Rahmani, Groot and Rahmani2024; Veldman, van Zon & Bültmann, Reference Veldman, van Zon and Bültmann2024). Within this context, interventions that target social disconnection in adolescence may have economic benefits stemming from increased work engagement and productivity, in addition to improving individuals’ wellbeing and life chances.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S0954579426101758.
Data availability statement
The dataset analyzed is not publicly available due to lack of informed consent and ethical approval but is available on request to qualified scientists. Requests require a concept paper describing the purpose of data access, ethical approval at the applicant’s institution, and provision for secure data access. More information is available at https://eriskstudy.com/data-access/. Analysis code is available at https://github.com/bridgetbryan/loneliness-isolation-interplay. All data analysis scripts are available for review.
Acknowledgments
The authors are grateful to the study members, their families and their teachers for their participation. Our thanks to Professors Terrie Moffitt and Avshalom Caspi, the founders of the E-Risk Study, CACI Inc., and to members of the E-Risk team for their dedication, hard work, and insights. For the purposes of open access, the author has applied a Creative Commons Attribution (CC BY) license to any Accepted Author Manuscript version arising from this submission.
Funding statement
The E-Risk Study received funding from the Medical Research Council (MRC grants G1002190 and MR/X010791). Additional support was provided by the National Institute of Child Health and Human Development (grant HD077482) and by the Jacobs Foundation. Bridget T. Bryan is supported by a Colt Foundation Postdoctoral Training Fellowship. Helen L. Fisher was part-supported by the Economic and Social Research Council (ESRC) Centre for Society and Mental Health at King’s College London (grant ES/S012567/1). The views expressed are those of the authors and not necessarily those of the funders or King’s College London. The funders had no role in the study design, data collection, analysis, interpretation or writing of the report.
Competing interests
The authors have no interests to declare.
Pre-registration statement
The research questions, hypotheses and analysis plan was pre-registered at https://sites.duke.edu/moffittcaspiprojects/projects_2025/ on 8 April 2025. The research questions, hypotheses and analyses presented in this manuscript do not deviate from that described in the pre-registration.


 Open access

