To save content items to your account,
please confirm that you agree to abide by our usage policies.
If this is the first time you use this feature, you will be asked to authorise Cambridge Core to connect with your account.
Find out more about saving content to .
To save content items to your Kindle, first ensure no-reply@cambridge.org
is added to your Approved Personal Document E-mail List under your Personal Document Settings
on the Manage Your Content and Devices page of your Amazon account. Then enter the ‘name’ part
of your Kindle email address below.
Find out more about saving to your Kindle.
Note you can select to save to either the @free.kindle.com or @kindle.com variations.
‘@free.kindle.com’ emails are free but can only be saved to your device when it is connected to wi-fi.
‘@kindle.com’ emails can be delivered even when you are not connected to wi-fi, but note that service fees apply.
Assessing the size of twins at birth using charts developed for singletons may over diagnose small for gestational age in this sub-population. The study aimed to produce international, twin-specific, newborn size normative charts by gestational age and sex. This longitudinal observational study in eight geographically diverse settings prospectively collected data between May 2009 and August 2013 from healthy pregnant women and their newborn twins. The participants were enrolled as part of the INTERGROWTH-21st study, and recruited based on World Health Organization recommendations for evaluation of anthropometric measures. All the women met, in addition to the underlying population characteristics of low perinatal risk, strict individual criteria for a population at low risk of impaired fetal growth. Newborn weight, length and head circumference measures were collected independently in duplicate by two trained anthropometrists within 12 hours of birth using identical equipment and protocols at all sites. From 1034 multiple pregnancies, after exclusions of condition such as smoking, high maternal BMI, and congenital malformations, the final sample was 864 twin newborns. Most of the twins were below the 50th centile of the INTERGROWTH-21st standards for singletons. We present international newborn size normative charts for twins using the same methodological approach adopted to construct the singleton standards.
Aggression and violence are common in psychiatric in-patient wards. Preventive measures such as de-escalation, increased observations, extra medication, restraint and seclusion are utilised by nurses and authorised by doctors in a highly skilled way that should be proportionate to the risks posed. There is limited empirical data on the proportionality of the use of restrictive practices within Irish forensic psychiatric units.
Objectives
The aim of this study was to rate the severity of incidents and proportionality of response to incidents in the high secure unit within the National Forensic Mental Health Service.
Methods
This is a prospective cohort study set in the Central Mental Hospital. Patients were assessed each day using the Dynamic Assessment of Situational Aggression (DASA) scale and incidents were rated each day using the DUNDRUM Restriction-Intrusion of Liberty Ladders Scales (DRILL), which includes the assessment of adverse incidents, violence and self-harm, interventions including restrictive practices and consequences. In this study we used episodes of restriction as an outcome measure. Data were gathered as part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST). Generalised Estimating Equations were used to analyse repeated measures in the same subjects.
Results
There were 384 patient days in scope, 411 lines of data including 326 patient-days, 85 incidents and 63 incidents of seclusion. The DRILL scales had good internal consistency (DRILL behaviours scale Cronbach’s alpha=0.789; DRILL interventions scale Alpha=0.866). The DASA on the day before an incident predicted the score on the DRILL behaviours scale (severity of behaviours) Wald X2=39565.2, p<0.001, with DUNDRUM-1 triage security scale also contributing significantly to the model Wald X2=884.3, p<0.001. The best model to predict the DRILL interventions scale included DASA on the day before (Wald X2=14.6, p=0.012) DRILL-behaviours scale (Wald X2=728.7, p<0.001) and DUNDRUM-1 (Wald X2=10,819.4, p<0.001). This was also the best model to predict whether or not a patient was secluded (DASA day before Wald X2=46.4, p<0.001; DRILL-behaviours scale Wald X2=173.2, p<0.001; DUNDRUM-1 Wald X2=6153.5, p<0.001).
Conclusions
Harmful behaviours and preventive and restrictive interventions can be described by rating items (‘ladders’) with good internal consistency, demonstrating that behaviour escalates in a meaningful sequence of increasingly serious harmful occurrences. The more serious the incident, the higher the level of restrictive practice used, demonstrating proportionality. This model of short term risk assessment and preventative interventions can be used to develop more effective and less restrictive interventions. Future research will explore moderating and mediating factors.
The Council of Europe’s Model Mental Health Act places emphasis on the need for a ‘debriefing’ discussion with patients after incidents of restrictive practices to arrive at a common understanding concerning what happened and to consider future prevention strategies. For the patient, issues may arise that may be subjectively reinforcing or subjectively aversive and staff may feel that the incident has, or does not have, alienating consequences.
Objectives
The aim of this study was to evaluate the consequences for the patient and for staff of incidents and use of subsequent restrictive practices, as a basis for future understanding of what debriefing might usefully include.
Methods
A prospective cohort study was completed whereby incidents were rated using the Dynamic Assessment of Situational Aggression (DASA) and DRILL tool ‘consequences’ scales in the Central Mental Hospital (CMH). The DRILL consequences scale consists of three ladders, ‘re-enforcing’, ‘aversive’ (both rated from the point of view of the patient) and ‘alienating’ (rated from the point of view of ward based staff). Data were gathered as part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST). An omnibus General Estimating Equations model (GEE) was tested with the DRILL ‘consequences’ as dependent prior to dismantling studies.
Results
In this study, the 384 patient-days were in scope, 411 lines of data including 326 patient-days, 85 harmful incidents and 63 incidents of seclusion. In an omnibus GEE with the three-item DRILL consequences scale as dependent variable, DASA on the day before Wald X2=3065.9, p<0.001; DRILL behaviours scale Wald X2=970.7, p<0.001; DRILL interventions Wald X2=140,159.1, p<0.001; DUNDRUM-1 Wald X2=1638.9, p<0.001. The three items of the DRILL consequences scale were individually tested as dependent variables in GEE models with DASA the day before, DRILL behaviour scale, DUNDRUM-1 and each of the eight items of the DRILL interventions scale. Only increasing observation levels were not re-enforcing, with searches and seclusion strongly re-enforcing.
Conclusions
We have shown that consequences of harmful behaviours and preventive, restrictive interventions are measurable and proportionate for patients and for staff. Short-term risk on the day prior to an incident was able to predict the re-enforcing and aversive consequences for the patient, but not the alienating consequences – or lack of them – for staff. Future research will examine the way in which the baseline need for security mediates or moderates the relationship between incidents and patients and staff views of the consequences of incidents and restrictive practices.
Multicenter clinical trials are essential for evaluating interventions but often face significant challenges in study design, site coordination, participant recruitment, and regulatory compliance. To address these issues, the National Institutes of Health’s National Center for Advancing Translational Sciences established the Trial Innovation Network (TIN). The TIN offers a scientific consultation process, providing access to clinical trial and disease experts who provide input and recommendations throughout the trial’s duration, at no cost to investigators. This approach aims to improve trial design, accelerate implementation, foster interdisciplinary teamwork, and spur innovations that enhance multicenter trial quality and efficiency. The TIN leverages resources of the Clinical and Translational Science Awards (CTSA) program, complementing local capabilities at the investigator’s institution. The Initial Consultation process focuses on the study’s scientific premise, design, site development, recruitment and retention strategies, funding feasibility, and other support areas. As of 6/1/2024, the TIN has provided 431 Initial Consultations to increase efficiency and accelerate trial implementation by delivering customized support and tailored recommendations. Across a range of clinical trials, the TIN has developed standardized, streamlined, and adaptable processes. We describe these processes, provide operational metrics, and include a set of lessons learned for consideration by other trial support and innovation networks.
Forensic psychiatric services address the therapeutic needs of mentally disordered offenders in a secure setting. Clinical, ethical, and legal considerations underpinning treatment emphasize that the Quality of Life (QOL) of patients admitted to forensic hospitals should be optimised.
Objectives
This study aims to examine changes in the QOL in Ireland’s National Forensic Mental Health Service following its relocation from the historic 1850 site in Dundrum to a new campus in Portrane, Dublin.
Methods
This multisite prospective longitudinal study is part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST). Repeated measures were taken for all inpatients in the service at regular six-monthly intervals. The WHOQOL-BREF questionnaire was offered to all inpatients and an anonymised EssenCES questionnaire was simultaneously used to measure atmosphere in the wards. Data were obtained at five time points for each individual patient and ward. WHOQOL-BREF ratings were obtained across five time points with comparisons for four time intervals, including immediately before and after relocation. For 101 subjects across the four time intervals, 215 sets of data were obtained; 140 before and 65 after relocation with 10 community patients who did not move. Using Generalised Estimating Equations (GEE) to correct for multiple comparisons over time, the effect of relocation, with community patients as a control, was analysed by ward cluster and whether patients moved between wards. Observations were categorised according to security level — high dependency, medium secure, rehabilitation, or community — and trichotomised based on positive moves to less secure wards, more secure wards (negative moves), or no moves.
Results
The hospital’s relocation was associated with a significant increase in environmental QOL (Wald X2=15.9, df=1, p<0.001), even when controlling for cluster location, positive and negative moves. When controlling for ward atmosphere, environmental QOL remained significantly increased after relocation (Wald X2=10.0, df=1, p=0.002). EssenCES scores were obtained within the hospital for three time points before relocation and two time points afterward. No significant differences were found in the three subscales before and after the relocation. All three EssenCES subscales progressively improved with decreasing security level (Patient’s Cohesion: Wald X2=958.3, df=1, p<0.001; Experienced Safety: Wald X2=152.9, df=5, p<0.001; Therapeutic Hold: Wald X2=33.6, df=3, p<0.001).
Conclusions
The GEE model showed that the hospital’s relocation improved self-reported environmental QOL. The cluster location made significant differences, as expected for a system of stratified therapeutic security, with a steady improvement in scores on all three atmosphere subscales.
Forensic psychiatric services serve a dual purpose: treatment of mental disorders and prevention of associated violent reoffending. Progression along the secure care pathway is often impeded by impaired insight, mainly as a result of treatment-resistant psychoses.
Objectives
We assessed levels of insight among patients in Ireland’s National Forensic Mental Health Service before and after its relocation from the historic 1850 campus in Dundrum to a modern facility in Portrane, Dublin.
Methods
The VAGUS insight scale was used in this repeated measures study before and after the relocation at two time points 42 months apart. All inpatients were invited to participate in completing the self-report (VAGUS-SR) and clinician-rated (VAGUS-CR) versions on both occasions. Total scores of both versions were averaged to obtain a combined VAGUS insight score. Corresponding Positive and Negative Syndrome Scale (PANSS) scores were used to ascertain correlations between the insight and symptomatology scales. This study is part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST)
Results
40 pairs of observations were available for legal capacity to consent to medication, combined VAGUS-CR and VAGUS-SR assessments of insight (Cronbach’s alpha=0.927), and PANSS. VAGUS-CR insight and PANSS scores were progressively better from admission and high dependency wards through medium-term medium secure wards to rehabilitation and pre-discharge wards. Mean scores did not change significantly over this time interval. Those legally certified fit to give or withhold consent by their treating consultant psychiatrists scored significantly better on the VAGUS combined insight scale: 8.3 (SD 1.7) v 5.3 (2.2) at baseline, paired t=25.9, p<0.001; and also 42 months later: 8.2 (1.4) v 5.7 (3.9), paired t=5.2, p=0.022. PANSS subscales were all significantly better for those assessed as being capacitous. Change in combined VAGUS score correlated with change in all PANSS subscales. Binary logistic regression with legal capacity as the dependent variable yielded a model in which combined VAGUS score and PANSS positive symptom score were independent determinants of assessed capacity status. Receiver operating characteristic area under the curve was 0.873, 95% CI 0.760-0.986, at baseline and 0.856, 95% CI 0.720-0.991, at 42 months. A score of 7.3 yielded a sensitivity of 0.8 and a specificity of 0.8.
Conclusions
The combined VAGUS score is a reliable and valid measure of insight relevant to functional mental capacity to consent to treatment with sensitivity and specificity sufficient to guide but not bind clinical decision-making. It measures a quality that varies with symptom severity but is also partly independent of symptom severity; the constructive inclusion of self-reported insight is notable.
The Central Mental Hospital Dundrum, is Irelands only secure forensic hospital. It is unclear if there were changes in the need for security or urgency of need for admission prior to admission; before, during and after the covid-19 pandemic.
Objectives
We examined any changes in need for security and urgency of need for admission among those admitted to the CMH Dundrum from 2018 to 2022. We also examined the need for seclusion due to immediate risk to others at the time of admission. Covid precautions were not managed with seclusion.
Methods
This is a retrospective cohort study of all patients admitted from 1st January 2018 to 31st August 2022. Demographic data and diagnosis, capacity to consent to medication and hours in seclusion during day 1, week 1 and month 1 were collated. Need for therapeutic security (Dundrum-1) and urgency of need for admission (Dundrum-2) were rated prior to admission and collated by the research team. Data were gathered as part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST). (Davoren et al., BMJ Open (2022) 12(7): e058581)
Results
During the 68-months there were 76 admissions. Mean age was 35.9 years, SD 9.9, males (80.3%). The most common diagnoses were schizophrenia (57.9%), schizoaffective disorder (15.8%), intellectual disabilty or autistic spectrum disorder (3.9%). 53.9% required seclusion on admission. There was no overall change in security need over the study period, but scores on triage urgency item 2 ‘mental health’ increased. Time on the waiting list correlated with increasingly urgent mental health needs. On logistic regression, higher (worse) scores on ‘mental health’ need predicted hours of seclusion on day 1 (B=6.3, p<0.001) and week 1 (B= 25.5, p<0.001) but not month 1. Prolonged seclusion in prison prior to admission predicted hours of seclusion on day 1 (B=3.1, p<0.001) week 1 (B=16.7, p=0.003) and month 1 (B=51.5, p=0.003). Higher scores on life time institutional behaviour (DUNDRUM-1 item 10) (B=53.2, p<0.001) also predicted hours of seclusion in month 1.
Conclusions
We found increasing severity of mental health needs during the period studied. Seclusion early in the course of admission to the forensic service was closely linked to mental health needs. Continuing to require seclusion later in the admission was more closely linked to institutional behaviour such as having a history of coordinating disturbances or challenging behaviour whilst in prison services.
Treatment resistant schizophrenia and other treatment resistant psychotic disorders are believed to be over-represented in forensic patient clusters. The true rates of treatment resistant psychoses in secure forensic hospitals remain unexplored.
Objectives
This study aimed to ascertain the prevalence of treatment resistant psychoses within a complete national forensic mental health service. In addition, the study sought to examine the relationships between treatment resistance for psychotic symptoms and treatment resistance in other domains, such as offending behaviour.
Methods
This is a cross-sectional study of a complete cohort of patients admitted to the National Forensic Mental Health Service in Ireland during the period 01/11/2021 to 31/01/2022. All inpatients at the time of the study were included. Demographic details, data appertaining to diagnosis, medication, measures of risk (HCR-20), recovery (DUNDRUM toolkit), functioning (GAF), and symptoms (PANSS) were collated. Data were gathered as part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST).
Results
The sample consisted of 170 patients. Majority (n=162) 95.3% were male. The majority (n=116), 68.2%, were admitted from prisons, while a smaller number (n=35), 20.6%, were admitted from other psychiatric facilities. The insanity defense (n=94) 55.3% was the most common legal status, followed by unfit to plead (n=16) 9.4%. The commonest diagnosis was schizophrenia (n=97) 57.1%, followed by schizoaffective disorder (n=27) 15.9% and autism spectrum disorder (n=5) 2.9%. The mean age at admission was 35.52 years and the median age was 34.37 ± 9.43 SD.
Of the total sample, 25.9% of patients were on more than 1000 mg per day chlorpromazine equivalent (CPZE) doses. Those whose psychotic symptoms required treatment with CPZE doses over 1000 mg per day scored poorly on DUNDRUM-3 programme completion, DUNDRUM-4 recovery scale, HCR-20 historical, HCR-20 clinical, HCR-20 risk, HCR-20 dynamic, and had poorer overall functioning (all P<0.001) than those who required lower antipsychotic doses. On binary logistic regression, correcting for age and gender, the only variable that remained significant was GAF (adjusted odds ratio = 0.979, 95% CI 0.962-0.996, P=0.014). In forward entry model regression, only the DUNDRUM-4 recovery scale (odds ratio = 1.13, 95% CI 1.07-1.19, P<0.001) and GAF (adjusted odds ratio = 0.979, 95% CI 0.962-0.996, P<0.001) were significant. This model had a robust forward and backward likelihood ratio.
Conclusions
Rates of treatment resistant psychoses in forensic hospital groups are indeed elevated. Overall functioning on GAF and recovery across a wide range of components in the DUNDRUM-4 scale are the best predictors of treatment resistant psychosis.
Secure forensic hospital settings provide care and treatment to mentally disordered offenders with a history of serious violence. Most modern forensic hospitals operate a system of stratified therapeutic security, where patients are placed on the internal care pathway according to individual risks and needs. Unfortunately, at times patients move ‘backwards’ from a unit of lower to a unit with higher therapeutic security. This is a challenge to manage from an individual patient and service perspective.
Objectives
The aim of this study was to analyse backwards moves along the care-pathway within a complete national cohort of forensic in-patients in Ireland over a five-year period. We aimed to clarify the reasons for these moves and ascertain if they were linked to mental illness, security or other issues.
Methods
A naturalistic retrospective five-year observational cohort study was completed. All in-patients in the Central Mental Hospital, Dundrum, Ireland or associated high support hostels between January 2016 and January 2021 were included (60 months). Demographic data, data pertaining to diagnosis, data pertaining to backwards moves and reasons for those moves were gathered. Data was gathered as part of the Dundrum Forensic Redevelopment Evaluation study (D-FOREST study).
Results
A total of n=231 patients were included; the majority (n= 203; 87.9%) were male. The most common diagnosis was schizophrenia (64.1%), followed by schizoaffective disorder (12.6%), bipolar affective disorder (4.8%) and autistic spectrum disorder (3.5%). Mean age at admission was 35.9 years, SD 9.5.
Over the 60-month period, a total of 93 backwards moves relating to 50 patients occurred. Reasons for backward moves included deteriorating mental state (8.7%), assaults (4.3%), challenging behaviour (4.3%), security (1%) and others. Binary logistic regression demonstrated that lacking capacity to consent to medication (Odds ratio 0.352, 95%CI 0.198-0.627, p<0.001) and higher (worse) scores on HCR-20 Historical scale (Odds ratio 1.13, 95%CI 1.01-1.27, p=0.035) were associated with backwards moves, when adjusting for age and Dundrum-1 need for therapeutic security scores.
Conclusions
Backwards care pathway moves are a major issue in forensic hospitals both nationally and internationally. We were surprised at the strength of association between lacking capacity to consent and backwards moves. Understanding backwards moves will assist in supporting patients and minimising length of stay.
Disclosure of Interest
L. Jordan Grant / Research support from: This study was funded by the Health Service Executive for the Republic of Ireland as part of the Dundrum Forensic Redevelopment Evaluation (D-FOREST) study, G. Crudden: None Declared, D. Mohan: None Declared, H. Kennedy: None Declared, M. Davoren: None Declared
There are high rates of treatment resistant psychoses and medical complexity among patients in secure forensic hospitals (Basrak et al., BJPsych Open (2021) 7, e31,1-7). Patients with schizophrenia in secure settings have a lower life expectancy compared to community peers of approximately 16 years. Evidence suggests patients in secure settings often gain significant amounts of body weight during their in-patient stays, many of whom develop complex obesity presentations.
Objectives
To ascertain changes in Body Mass Index (BMI) among patients in a secure forensic hospital setting over a 3.5 year period.
Methods
A prospective longitudinal study of repeated measures of BMI for all (n=91) patients in a National Forensic Mental Health Service (CMH Dundrum, Dublin, Ireland). BMI was measured six-monthly, giving up to seven time points for each patient. Generalized Estimating Equations (GEE) analysis was conducted to ascertain changes in BMI over time. This study formed part of the DUNDRUM Forensic Redevelopment Evaluation Study (D-FOREST) (Davoren et al., BMJ Open (2022) 12(7): e058581).
Results
A total of 91 patients were included in the study, mean age 33.46 years (SD 9.23). Mean length of stay was 8.09 years (SD 9.23). The most common diagnosis was schizophrenia (67%), followed by schizoaffective disorder (17.5%) and Autistic spectrum disorder (6.2%). Using GEE with BMI as the dependent variable, for the complete patient cohort, BMI changed significantly with diagnosis (Wald X2=5817.58, df=7, p<0.001). Those with severe mental illnesses (psychoses) had the highest BMI of the group, and BMI tended to increase over time (p=0.109). Among patients who were in the secure hospital for four years or less, their weight gain was significant over time (Wald X2 =10.0, df=1, p=0.002).
Conclusions
We have shown high rates of obesity particularly in patients with psychoses and we have shown weight gain is significant during the first four years after admission to a national forensic service. This is a significant health concern and an area of unmet treatment need which is likely generalizable across secure hospitals in the EU.
Despite replicated cross-sectional evidence of aberrant levels of peripheral inflammatory markers in individuals with major depressive disorder (MDD), there is limited literature on associations between inflammatory tone and response to sequential pharmacotherapies.
Objectives
To assess associations between plasma levels of pro-inflammatory markers and treatment response to escitalopram and adjunctive aripiprazole in adults with MDD.
Methods
In a 16-week open-label clinical trial, 211 participants with MDD were treated with escitalopram 10– 20 mg daily for 8 weeks. Responders continued on escitalopram while non-responders received adjunctive aripiprazole 2–10 mg daily for 8 weeks. Plasma levels of pro-inflammatory markers – C-reactive protein, Interleukin (IL)-1β, IL-6, IL-17, Interferon gamma (IFN)-Γ, Tumour Necrosis Factor (TNF)-α, and Chemokine C–C motif ligand-2 (CCL-2) - measured at baseline, and after 2, 8 and 16 weeks were included in logistic regression analyses to assess associations between inflammatory markers and treatment response.
Results
Pre-treatment levels of IFN-Γ and CCL-2 were significantly higher in escitalopram non-responders compared to responders. Pre-treatment IFN-Γ and CCL-2 levels were significantly associated with a lower of odds of response to escitalopram at 8 weeks. Increases in CCL-2 levels from weeks 8 to 16 in escitalopram non-responders were significantly associated with higher odds of non-response to adjunctive aripiprazole at week 16.
Conclusions
Pre-treatment levels of IFN-Γ and CCL-2 were predictive of response to escitalopram. Increasing levels of these pro-inflammatory markers may predict non-response to adjunctive aripiprazole. These findings require validation in independent clinical populations.
Secure forensic mental health services have a dual role, to treat mental disorder and reduce violent recidivism. Quality of life is a method of assessing an individual patients’ perception of their own life and is linked to personal recovery. Placement in secure forensic hospital settings should not be a barrier to achieving meaningful quality of life. The WHO-QuOL measure is a self-rated tool, internationally validated used to measure patients own perception of their quality of life.
Objectives
This aim of this study was to assess self-reported quality of life in a complete National cohort of forensic in-patients, and ascertain the associations between quality of life and measures of violence risk, recovery and functioning.
Methods
This is a cross sectional study, set in Dundrum Hospital, the site of Ireland’s National Forensic Mental Health Service. It therefore includes a complete national cohort of forensic in-patients. The WHO-QuOL was offered to all 95 in-patients in Dundrum Hospital during December 2020 – January 2021, as was PANSS (Positive and Negative Symptoms for Schizophrenia Scale). During the study period the researchers collated the scores from HCR-20 (violence risk), therapeutic programme completion (DUNDRUM-3) and recovery (DUNDRUM-4). Data was gathered as part of the Dundrum Forensic Redevelopment Evaluation Study (D-FOREST).
Results
Lower scores on dynamic violence risk, better recovery and functioning scores were associated with higher self-rated quality of life.
Conclusions
The quality of life scale was meaningful in a secure forensic hospital setting. Further analysis will test relationships between symptoms, risk and protective factors and global function.
In this era of spatially resolved observations of planet-forming disks with Atacama Large Millimeter Array (ALMA) and large ground-based telescopes such as the Very Large Telescope (VLT), Keck, and Subaru, we still lack statistically relevant information on the quantity and composition of the material that is building the planets, such as the total disk gas mass, the ice content of dust, and the state of water in planetesimals. SPace Infrared telescope for Cosmology and Astrophysics (SPICA) is an infrared space mission concept developed jointly by Japan Aerospace Exploration Agency (JAXA) and European Space Agency (ESA) to address these questions. The key unique capabilities of SPICA that enable this research are (1) the wide spectral coverage $10{-}220\,\mu\mathrm{m}$, (2) the high line detection sensitivity of $(1{-}2) \times 10^{-19}\,\mathrm{W\,m}^{-2}$ with $R \sim 2\,000{-}5\,000$ in the far-IR (SAFARI), and $10^{-20}\,\mathrm{W\,m}^{-2}$ with $R \sim 29\,000$ in the mid-IR (SPICA Mid-infrared Instrument (SMI), spectrally resolving line profiles), (3) the high far-IR continuum sensitivity of 0.45 mJy (SAFARI), and (4) the observing efficiency for point source surveys. This paper details how mid- to far-IR infrared spectra will be unique in measuring the gas masses and water/ice content of disks and how these quantities evolve during the planet-forming period. These observations will clarify the crucial transition when disks exhaust their primordial gas and further planet formation requires secondary gas produced from planetesimals. The high spectral resolution mid-IR is also unique for determining the location of the snowline dividing the rocky and icy mass reservoirs within the disk and how the divide evolves during the build-up of planetary systems. Infrared spectroscopy (mid- to far-IR) of key solid-state bands is crucial for assessing whether extensive radial mixing, which is part of our Solar System history, is a general process occurring in most planetary systems and whether extrasolar planetesimals are similar to our Solar System comets/asteroids. We demonstrate that the SPICA mission concept would allow us to achieve the above ambitious science goals through large surveys of several hundred disks within $\sim\!2.5$ months of observing time.
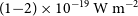
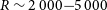

Studying phenotypic and genetic characteristics of age at onset (AAO) and polarity at onset (PAO) in bipolar disorder can provide new insights into disease pathology and facilitate the development of screening tools.
Aims
To examine the genetic architecture of AAO and PAO and their association with bipolar disorder disease characteristics.
Method
Genome-wide association studies (GWASs) and polygenic score (PGS) analyses of AAO (n = 12 977) and PAO (n = 6773) were conducted in patients with bipolar disorder from 34 cohorts and a replication sample (n = 2237). The association of onset with disease characteristics was investigated in two of these cohorts.
Results
Earlier AAO was associated with a higher probability of psychotic symptoms, suicidality, lower educational attainment, not living together and fewer episodes. Depressive onset correlated with suicidality and manic onset correlated with delusions and manic episodes. Systematic differences in AAO between cohorts and continents of origin were observed. This was also reflected in single-nucleotide variant-based heritability estimates, with higher heritabilities for stricter onset definitions. Increased PGS for autism spectrum disorder (β = −0.34 years, s.e. = 0.08), major depression (β = −0.34 years, s.e. = 0.08), schizophrenia (β = −0.39 years, s.e. = 0.08), and educational attainment (β = −0.31 years, s.e. = 0.08) were associated with an earlier AAO. The AAO GWAS identified one significant locus, but this finding did not replicate. Neither GWAS nor PGS analyses yielded significant associations with PAO.
Conclusions
AAO and PAO are associated with indicators of bipolar disorder severity. Individuals with an earlier onset show an increased polygenic liability for a broad spectrum of psychiatric traits. Systematic differences in AAO across cohorts, continents and phenotype definitions introduce significant heterogeneity, affecting analyses.
Clinical trials continue to face significant challenges in participant recruitment and retention. The Recruitment Innovation Center (RIC), part of the Trial Innovation Network (TIN), has been funded by the National Center for Advancing Translational Sciences of the National Institutes of Health to develop innovative strategies and technologies to enhance participant engagement in all stages of multicenter clinical trials. In collaboration with investigator teams and liaisons at Clinical and Translational Science Award institutions, the RIC is charged with the mission to design, field-test, and refine novel resources in the context of individual clinical trials. These innovations are disseminated via newsletters, publications, a virtual toolbox on the TIN website, and RIC-hosted collaboration webinars. The RIC has designed, implemented, and promised customized recruitment support for 173 studies across many diverse disease areas. This support has incorporated site feasibility assessments, community input sessions, recruitment materials recommendations, social media campaigns, and an array of study-specific suggestions. The RIC’s goal is to evaluate the efficacy of these resources and provide access to all investigating teams, so that more trials can be completed on time, within budget, with diverse participation, and with enough accrual to power statistical analyses and make substantive contributions to the advancement of healthcare.
We describe here efforts to create and study magnetized electron–positron pair plasmas, the existence of which in astrophysical environments is well-established. Laboratory incarnations of such systems are becoming ever more possible due to novel approaches and techniques in plasma, beam and laser physics. Traditional magnetized plasmas studied to date, both in nature and in the laboratory, exhibit a host of different wave types, many of which are generically unstable and evolve into turbulence or violent instabilities. This complexity and the instability of these waves stem to a large degree from the difference in mass between the positively and the negatively charged species: the ions and the electrons. The mass symmetry of pair plasmas, on the other hand, results in unique behaviour, a topic that has been intensively studied theoretically and numerically for decades, but experimental studies are still in the early stages of development. A levitated dipole device is now under construction to study magnetized low-energy, short-Debye-length electron–positron plasmas; this experiment, as well as a stellarator device that is in the planning stage, will be fuelled by a reactor-based positron source and make use of state-of-the-art positron cooling and storage techniques. Relativistic pair plasmas with very different parameters will be created using pair production resulting from intense laser–matter interactions and will be confined in a high-field mirror configuration. We highlight the differences between and similarities among these approaches, and discuss the unique physics insights that can be gained by these studies.
Swift medically led scientifically informed responses to the Covid-19 epidemic nationally have been demonstrably superior to other, non-scientific approaches. In forensic psychiatry and across all psychiatric services, urgent and clinically led responses have underlined redundancies and confusions in the governance of mental health services and a vacuum in policy makers. For the future, a greater emphasis on services for patients with schizophrenia and other severe, enduring mental disorders must aim at reducing standardised mortality ratios, managing risk of violence and improving hard outcomes such as symptomatic remission, functional recovery and forensic recovery of autonomy. This will require more use of information technology at service level and at national level where Scandinavian-style population-based data linkage research must now become legally sanctioned and necessary. A national research and development centre for medical excellence in forensic psychiatry is urgently required and is complimentary to and different from quality management.
There is renewed interest in the inverse association between psychiatric hospital and prison places, with reciprocal time trends shown in more than one country. We hypothesised that the numbers of admissions to psychiatric hospitals and committals to prisons in Ireland would also correlate inversely over time (i.e. dynamic measures of admission and committal rather than static, cross-sectional numbers of places).
Method
Publicly available activity statistics for psychiatric hospitals and prisons in Ireland were collated from 1986 to 2010.
Results
There was a reciprocal association between psychiatric admissions and prison committals (Pearson r=−0.788, p<0.001), an increase of 91 prison committals for every 100 psychiatric hospital admissions foregone.
Conclusion
Penrose’s hypothesis applies to admissions to psychiatric hospitals and prisons in Ireland over time (dynamic measures), just as it does to the numbers of places in psychiatric hospitals and prisons in Ireland and elsewhere (static, cross-sectional measures). Although no causal connection can be definitively established yet, mentally disordered prisoners are usually known to community mental health services. Psychiatric services for prisons and the community should be linked to ensure that the needs of those currently accessing care through prisons can also be met in the community.