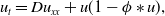To save content items to your account,
please confirm that you agree to abide by our usage policies.
If this is the first time you use this feature, you will be asked to authorise Cambridge Core to connect with your account.
Find out more about saving content to .
To save content items to your Kindle, first ensure no-reply@cambridge.org
is added to your Approved Personal Document E-mail List under your Personal Document Settings
on the Manage Your Content and Devices page of your Amazon account. Then enter the ‘name’ part
of your Kindle email address below.
Find out more about saving to your Kindle.
Note you can select to save to either the @free.kindle.com or @kindle.com variations.
‘@free.kindle.com’ emails are free but can only be saved to your device when it is connected to wi-fi.
‘@kindle.com’ emails can be delivered even when you are not connected to wi-fi, but note that service fees apply.
To evaluate the validity and correlates of inaccurate clinically diagnosed moderate/severe ICD-10 major depressive disorder (MDD) and psychiatric comorbidities in adult inpatients.
Methods
The multicenter Patient Characteristics, Validity of Clinical Diagnoses and Outcomes Associated with Suicidality in Inpatients with Symptoms of Depression (OASIS-D) study enrolled 18- to 75-year-old inpatients with MDD who underwent assessments for clinical, illness, and treatment characteristics, including the Mini-International-Neuropsychiatric-Interview (MINI). False-positive clinically MDD diagnoses were characterized via MINI. Diagnostic agreement between clinical and MINI-based psychiatric comorbidities was assessed with kappa-statistic.
Results
Among 401 patients (median age = 33.0 years; female = 57.1%), 42 (10.5%) were false positive for MDD (i.e., different primary diagnosis). Reasons for misdiagnosing MDD exclusive to false-positive cases included bipolar disorder (45.2%), subsyndromal depression (16.7%), and physical illness-related/substance use disorder (SUD)-related depression (4.8%), whereas missed diagnoses that could also occur in true-positive, MINI-based MDD patients included primary SUDs (23.8%) and primary anxiety disorders (9.5%). Among comorbidities, greatest disagreement between clinical and MINI-based research diagnoses existed for antisocial personality disorder (0% vs. 5.2%, κ =0), followed by anxiety disorders (7.5% vs. 45.1%, κ =0.17), obsessive-compulsive disorder (3.0% vs. 8.7%, κ =0.27), SUDs (11.0% vs. 28.4%, κ =0.29), eating disorders (3.5% vs. 7.2%, κ =0.39), and posttraumatic stress disorder (10.7% vs. 23.7%, κ =0.40).
Conclusions
Bipolar depression and SUDs contributed to two thirds of misdiagnosed MDD. Missed comorbidities included mostly anxiety disorders, SUDs, and PTSD. Accurate diagnostic assessment, including longitudinal history, is essential to reduce misdiagnosis and ensure guideline-based treatment for psychiatric disorders in MDD inpatients.
We prove the existence of solitary waves in a lattice where all particles interact with each other by pairwise repulsive forces that decay with distance. The variational existence proof is based on constrained optimization and provides a one-parameter family of unimodal solutions. We also describe the asymptotic behaviour of large, fast, high-energy waves.
The Mediterranean Diet (MedDiet) and physical activity (PA) can enhance mood and support psychological wellbeing in adults. However, the combined effect is relatively unknown. MedWalk aimed to determine the combined effect on wellbeing, psychological health and quality of life (QoL), compared to a control group.
Design:
This is an analysis of secondary outcomes from the MedWalk 12-month cluster-randomised controlled trial. Participants completed the Total and Secure Flourishing Index (FI), the four domain General Health Questionnaire (GHQ-28) and the 8-domain Assessment of Quality of Life (AQoL-8D). Data were analysed using general linear models using change scores (FI and AQoL-8D) or generalised linear mixed models with a time × group interaction effect (GHQ-28).
Setting:
Independent living facilities across South Australia and Victoria in 2021–2022.
Participants:
One hundred and sixty-one older men and women.
Results:
Participants were 74·9 ± 5·9 years of age and predominantly female (74 %). A greater improvement was found for the MedWalk group (marginal means (MM) = 1·65, se = 1·36) than the control group (MM = –2·50, se = 1·32) for the Total Flourish score (P = 0·003) and Secure Flourish score (P = 0·009) ((MM = 1·06, se = 1·65) v. (MM = –3·34, se = 1·61)) from baseline to 6 months. The MedWalk group (MM = 0·021, se = 0·014) had more positive changes (P = 0·048) to the Mental Health AQoL-8D domain than the control group (MM = –0·007, se = 0·014). No significant group × time interactions were identified for the GHQ-28.
Conclusions:
Combined MedDiet and walking interventions can modify psychological health, wellbeing and QoL in relatively healthy populations.
Volunteering in civil society organizations (CSOs) is sometimes idealized as welcoming arena for everybody. Prior research, however, has shown that participation in volunteer work depends on gender, wealth, education, and social networks, suggesting that CSOs are not in fact open to everyone. Inequality within different fields of volunteering combined with the factors that put actors into more powerful positions has rarely been scrutinized. Besides identifying the characteristics and resources relevant for promotion, we primarily investigate how these patterns differ between four subfields: politics, social services, religion, and sports. We analyzed a large database created from the Austrian micro-census. The findings reveal significant relations between the actors’ gender, their occupational and educational status, and their hierarchical positions in CSOs within each of the subfields. Our results indicate that the extent to which social inequality spills over to volunteering depends on field characteristics: In the fields of sports and politics, occupational status plays a major role, while in the fields of religion and social services, educational status is more important. We explain these differences through organizational and individual factors that characterize these social fields.
In this article, we investigate the changes in the legitimating accounts used by Civil Society Organizations (CSOs), in the context of spreading managerialism—one of the most powerful institutional practices of our time—in the Third Sector. We first introduce the concepts of legitimacy and legitimating account, before showing how managerialism manifests itself in CSOs and presenting three managerialist accounts used to legitimate such organizations: efficiency and effectiveness (E&E), stakeholder’s needs, and innovation. We then examine empirically how the use of these accounts changed between 1995 and 2008. In order to do so, we analyze quantitatively the contents of a sample of annual reports produced by Austrian CSOs over the stated period, and apply discourse analysis to a smaller group of reports to reveal more fine-grained developments. Our results show significant changes: of our chosen accounts, the one most tightly linked with managerialism, E&E, had come to be taken-for-granted by 2008, whereas the more generic and subtle concepts of stakeholder’s needs and innovation featured more strongly than in 1995.
We investigate how nonprofit organizations (NPOs) construct imaginaries of their premises, their local environment, and beyond. Based on a qualitative analysis of the websites of 209 randomly sampled NPOs in a metropolitan region in Central Europe, we find four distinct spatial imaginaries: (1) The world polity imaginary constructs NPOs as a part of a spatial environment that is neatly divided into nation states, supranational structures, and subnational units. (2) In the world society imaginary, NPOs are active in blurred, fluid, and overlapping spaces such as networks, commercialized spaces, or natural habitats. (3) In a religious imaginary, the material world is complemented by a transcendental realm and categorized into spaces of the sacred and the evil. (4) Finally, in a lococentric imaginary, NPOs construct a dichotomy between "home" and the alien rest of the world. Each of these spatial imaginaries conveys distinctive ways of situating the organization in their spatial environment and implies specific organizational practices and emotional enchantments of space.
The capability of organizations to respond to unexpected events has been investigated from different theoretical angles: organizational learning, improvisation, ambidexterity, resilience, to name but a few. These concepts, however, hardly ever refer to structural characteristics. Against this backdrop, the aim of this paper is twofold. First, based on systems and organizational learning theory, it will theoretically link the characteristics of organizational structure with organizational responses to unexpected external jolts, thus contributing to better understand the reactions of organizations to the unexpected. Second, it will empirically illustrate the relation of organizational structure with organizational responses by investigating how Civil Society Organizations (CSOs) in Austria reacted to the unexpected inflow of refugees from Central Europe. In 2015, CSOs accepted a wide range of responsibilities and worked together with government entities to provide shelter, catering, and transport for almost one million refugees. Based on participant observations during operation, in-depth interviews (2015 and 2016) and focus groups with decision-makers (2017), we will sketch three longitudinal case studies of organizations with very different structures, concentrating on the processes and operations they developed during the crisis. Our findings show that their responses are closely related to their structure, specifically to the flexibility and the stability of structural elements. Remarkable changes took place in all organizations investigated. Initial responses and first structural changes occurred mainly where the structure already allowed for flexibility. Yet in the long run, the adaptations also impacted the stable structural elements.
Transparency means being honest and open about one’s practices. Transparency is considered a gold standard in the nonprofit sector and associated with a range of positive outcomes. We propose that transparency should also become a guiding principle and documented practice for nonprofit scholars. In this article, we articulate the context for discussing transparency in social science research and the potential risks of not being transparent. Acknowledging the epistemic and methodological diversity of our field—and therefore, the need for flexibility in how transparency will be practiced by different scholars—we encourage nonprofit researchers to consider how they can enhance their research transparency. To this end, we outline the benefits of transparency and offer concrete suggestions for different ways to demonstrate transparency in nonprofit research.
Different disciplinary, theoretical, and empirical lenses have contributed to a kaleidoscopic picture of the governance of civil society organizations (CSOs). Most of the time, CSO governance is contrasted with corporate governance in business organizations; only rarely is the broad variety of CSOs taken into account. To widen this perspective, we develop an empirically grounded typology of five discourses of organization in CSOs: managerialist, domestic, professionalist, grassroots, and civic discourse. We argue that each of these discourses gives specific answers to the three core questions of governance: To whom is the CSO accountable, i.e., who are the key actors who need to be protected by governance mechanisms? For what kind of performance is the CSO accountable? And which structures and processes are appropriate to ensure accountability? The way in which different discourses answer these questions provides us with a deeper understanding of the reasons behind the manifold notions of governance in CSOs.
Although civil societies in Central and Eastern Europe are often portrayed as similar, united by a shared communist past, they have developed along increasingly divergent trajectories over the past three decades. This article investigates the current state of civil society in the region and the role the institutional context plays in it. Drawing on historical institutionalism and the process of European integration, we classify the 14 countries under investigation into three distinct groups and analyze data from a survey of more than 350 local civil society experts. We find that, together with domestic governments, international donors and the EU are perceived as the most influential institutional actors for civil society organizations. Their respective influences, however, depend largely on a country’s stage in the EU accession process. Overall, the study provides a differentiated mapping of civil society in this region and a better understanding of how the institutional context relates to a country’s civil society.
Why did some individuals react to the Covid-19 crisis in a prosocial manner, whereas others withdrew from society? To shed light onto this question, we investigate changing patterns of charitable giving during the pandemic. The study analyzes survey data of 2000 individuals, representative of the populations of Germany and Austria. Logistic regressions reveal that personal affectedness by Covid-19 seems to play a crucial role: those who were personally affected either mentally, financially, or health-wise during the first 12 months of Covid-19 were most likely to have changed their giving behavior. The observed patterns fit psychological explanations of how human beings process existential threats. Our findings indicate that a profound societal crisis in itself mainly leads to changes in charitable giving if individuals are severely affected on a personal level. Thereby, we contribute to a better understanding of the mechanisms underlying individuals’ charitable giving behavior in times of crisis.
Nonprofit organizations (NPOs) contribute to vital neighborhoods by building communities of citizens and acting as intermediaries between citizens and organizations. We investigate how NPOs’ engagement in social and systemic integration is shaped by neighborhood characteristics, and how it relates to the organizational practices of managerialism and organizational democracy. We combine survey data with administrative data from a representative sample of NPOs in a major European city. To measure the effect of neighborhood on organizational integration, we separated the city into 7,840 grid cells characterized by population, per capita income, share of immigrant population, and density of organizations. Findings indicate that managerialism positively relates with systemic integration, as organizational democracy relates with social integration. Neighborhood characteristics, however, are not related with NPOs’ engagement in integration. Our findings contribute to research on urban social cohesion by illuminating the interplay between NPOs’ organizing practices, local neighborhoods, and contributions to both forms of integration.
There is growing evidence that optimising dietary quality and engaging in physical activity (PA) can reduce dementia and cognitive decline risk and improve psychosocial health and quality of life (QoL). Multimodal interventions focusing on diet and PA are recognised as significant strategies to tackle these behavioural risk factors; however, the cost-effectiveness of such interventions is seldom reported. A limited cost consequence based on a 12-month cluster-randomised Mediterranean diet (MedDiet) and walking controlled trial (MedWalk) was undertaken. In addition, QoL data were analysed. Programme costs ($AUD2024) covered staff to deliver the MedWalk programme and foods to support dietary behaviour change. The primary outcome measure of this study was change in QoL utility score, measured using the Assessment of Quality of Life (AQoL-8D). Change scores were compared for the groups using general linear models while controlling for demographic factors associated with baseline group differences and attrition. Change in QoL (decreased, maintained or improved) was determined using a cross-tabulation test. MedWalk programme costs were estimated at $2695 AUD per participant and control group cost at $165 per person – a differential cost of $2530. Mean change in utility scores from baseline to 12 months was not statistically significant between groups. Nevertheless, the MedWalk group was significantly less likely to experience a reduction in their QoL (20·3 % MedWalk v. 42·6 % control group) (P = 0·020). A MedDiet and walking intervention may have a role in preventing decline in QoL of older Australians; however, longer-term follow-up would be beneficial to see if this is maintained.
The authors offer reflections and lessons learned in a single pediatric tertiary center’s experience during a pediatric mass casualty incident (MCI). The MCI occurred at a holiday parade and the patients were brought to multiple community emergency departments for initial resuscitation prior to transfer to the Pediatric level 1 trauma center. In total, 18 children presented with severe blunt force trauma after a motor vehicle entered the parade route. Following initial triage in emergency departments, 10 of 18 children injured during the incident were admitted to the Pediatric Intensive Care Unit, collectively representing a system-wide stressor of emergency medicine, critical care, and surgical services. Institutional characteristics, activation of personnel and supplies, and psychosocial support for families during an MCI are important to consider in children’s hospitals’ disaster preparedness planning.
Dropout from healthcare interventions can negatively affect patients and healthcare providers through impaired trust in the healthcare system and ineffective use of resources. Research on this topic is still largely missing on refugees and asylum seekers. The current study aimed to characterize predictors for dropout in the Mental Health in Refugees and Asylum Seekers (MEHIRA) study, one of the largest multicentered controlled trials investigating the effectiveness and cost-effectiveness of a nationwide stepped and collaborative care model.
Methods
Predictors were multiply imputed and selected for descriptive modelling using backward elimination. The final variable set was entered into logistic regression.
Results
The overall dropout rate was 41,7%. Dropout was higher in participants in group therapy (p = 0.001; OR = 10.7), with larger satisfaction with social relationships (p = 0.017; OR = 1.87), with difficulties in maintaining personal relationships (p = 0.005; OR = 4.27), and with higher depressive symptoms (p = 0.029; OR = 1.05). Participants living in refugee accommodation (p = 0.040; OR = 0.45), with a change in social status (p = 0.008; OR = 0.67) and with conduct (p = 0.020; OR = 0.24) and emotional problems (p = 0.013; OR = 0.31) were significantly less likely to drop out of treatment.
Conclusion
Overall, the outcomes of this study suggest that predictors assessing social relationships, social status, and living conditions should be considered as topics of psychological treatment to increase adherence and as predictors for future research studies (including treatment type).
We study the Cauchy problem on the real line for the nonlocal Fisher-KPP equation in one spatial dimension,
\begin{equation*} u_t = D u_{xx} + u(1-\phi *u), \end{equation*}
where $\phi *u$ is a spatial convolution with the top hat kernel, $\phi (y) \equiv H\left (\frac{1}{4}-y^2\right )$. After observing that the problem is globally well-posed, we demonstrate that positive, spatially periodic solutions bifurcate from the spatially uniform steady state solution $u=1$ as the diffusivity, $D$, decreases through $\Delta _1 \approx 0.00297$ (the exact value is determined in Section 3). We explicitly construct these spatially periodic solutions as uniformly valid asymptotic approximations for $D \ll 1$, over one wavelength, via the method of matched asymptotic expansions. These consist, at leading order, of regularly spaced, compactly supported regions with width of $O(1)$ where $u=O(1)$, separated by regions where $u$ is exponentially small at leading order as $D \to 0^+$. From numerical solutions, we find that for $D \geq \Delta _1$, permanent form travelling waves, with minimum wavespeed, $2 \sqrt{D}$, are generated, whilst for $0 \lt D \lt \Delta _1$, the wavefronts generated separate the regions where $u=0$ from a region where a steady periodic solution is created via a distinct periodic shedding mechanism acting immediately to the rear of the advancing front, with this mechanism becoming more pronounced with decreasing $D$. The structure of these transitional travelling wave forms is examined in some detail.
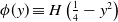
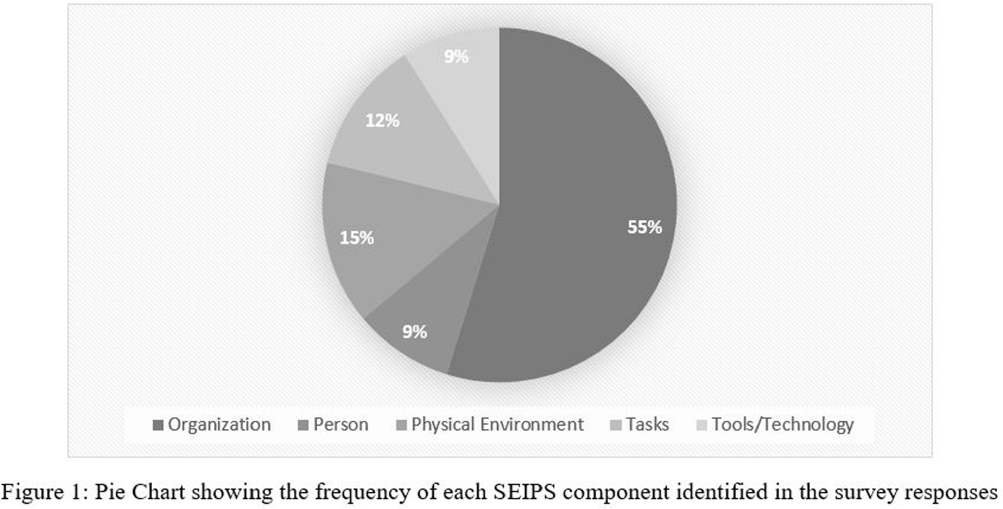
Background: Presenteeism when ill in healthcare personnel (HCP) can contribute to the spread of respiratory illness among HCP and patients. However, during the COVID-19 pandemic and now, there are substantial challenges preventing HCP from staying home when ill. We examined these challenges using the Systems Engineering Initiative for Patient Safety (SEIPS) framework. Method: As part of a larger anonymous electronic survey between 3/11/2022 and 4/12/2022 at an academic tertiary referral center, in inpatient and ambulatory settings where respondents were asked to describe factors impacting presenteeism when ill, we analyzed free-text responses using the SEIPS categories of tasks, tools/technology, person, organization, and physical environment. Result: 522 comments were received in response to the open-ended survey question asking individuals to describe any factors that would assist them in remaining home and/or help them get tested for COVID-19 when they have symptoms of a respiratory illness; 21 were excluded due to absent or incomplete response. Of the remaining responses (N = 501, Figure 1), 82% were associated with a single SEIPS component such as organization (N = 409), while other responses discussed factors that involved two SEIPS components, in no particular order (N = 92). A majority of the responses (N = 324, 55%) reported organizational barriers, frequently citing a strict sick call-in policy as well as a lack of protected time-off for COVID-19 testing or related absences. The next two most commonly identified components were physical environment (N= 88, 15%) and tasks (N = 72, 12%), mentioning barriers such as far distances to testing centers and prolonged waiting periods for testing Results: The person and tools/technology components were less commonly identified, with a frequency of 9% each. Conclusion: A number of systems level factors were identified that may impact the ability of HCP to stay home when ill. Interventions to help overcome HCP perceived barriers to staying home when experiencing respiratory symptoms should focus on the policies and practices within an organization. Communication from leadership should support staying home with respiratory symptoms by creating plans for coverage and back up consistently across all employee types in direct care.
Although the link between alcohol involvement and behavioral phenotypes (e.g. impulsivity, negative affect, executive function [EF]) is well-established, the directionality of these associations, specificity to stages of alcohol involvement, and extent of shared genetic liability remain unclear. We estimate longitudinal associations between transitions among alcohol milestones, behavioral phenotypes, and indices of genetic risk.
Methods
Data came from the Collaborative Study on the Genetics of Alcoholism (n = 3681; ages 11–36). Alcohol transitions (first: drink, intoxication, alcohol use disorder [AUD] symptom, AUD diagnosis), internalizing, and externalizing phenotypes came from the Semi-Structured Assessment for the Genetics of Alcoholism. EF was measured with the Tower of London and Visual Span Tasks. Polygenic scores (PGS) were computed for alcohol-related and behavioral phenotypes. Cox models estimated associations among PGS, behavior, and alcohol milestones.
Results
Externalizing phenotypes (e.g. conduct disorder symptoms) were associated with future initiation and drinking problems (hazard ratio (HR)⩾1.16). Internalizing (e.g. social anxiety) was associated with hazards for progression from first drink to severe AUD (HR⩾1.55). Initiation and AUD were associated with increased hazards for later depressive symptoms and suicidal ideation (HR⩾1.38), and initiation was associated with increased hazards for future conduct symptoms (HR = 1.60). EF was not associated with alcohol transitions. Drinks per week PGS was linked with increased hazards for alcohol transitions (HR⩾1.06). Problematic alcohol use PGS increased hazards for suicidal ideation (HR = 1.20).
Conclusions
Behavioral markers of addiction vulnerability precede and follow alcohol transitions, highlighting dynamic, bidirectional relationships between behavior and emerging addiction.
Cardiometabolic disease risk factors are disproportionately prevalent in bipolar disorder (BD) and are associated with cognitive impairment. It is, however, unknown which health risk factors for cardiometabolic disease are relevant to cognition in BD. This study aimed to identify the cardiometabolic disease risk factors that are the most important correlates of cognitive impairment in BD; and to examine whether the nature of the relationships vary between mid and later life.
Methods
Data from the UK Biobank were available for 966 participants with BD, aged between 40 and 69 years. Individual cardiometabolic disease risk factors were initially regressed onto a global cognition score in separate models for the following risk factor domains; (1) health risk behaviors (physical activity, sedentary behavior, smoking, and sleep) and (2) physiological risk factors, stratified into (2a) anthropometric and clinical risk (handgrip strength, body composition, and blood pressure), and (2b) cardiometabolic disease risk biomarkers (CRP, lipid profile, and HbA1c). A final combined multivariate regression model for global cognition was then fitted, including only the predictor variables that were significantly associated with cognition in the previous models.
Results
In the final combined model, lower mentally active and higher passive sedentary behavior, higher levels of physical activity, inadequate sleep duration, higher systolic and lower diastolic blood pressure, and lower handgrip strength were associated with worse global cognition.
Conclusions
Health risk behaviors, as well as blood pressure and muscular strength, are associated with cognitive function in BD, whereas other traditional physiological cardiometabolic disease risk factors are not.